
Rabeprazole
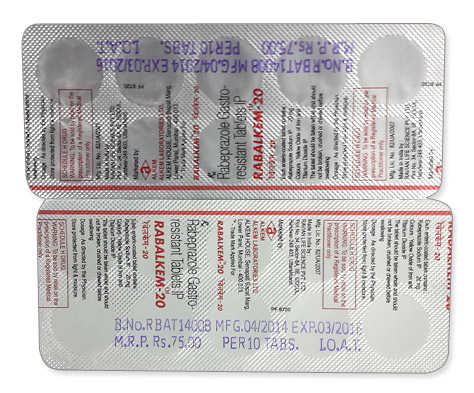
Rabeprazole
- In our pharmacy, you can buy rabeprazole without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Rabeprazole is used to treat gastro-oesophageal reflux disease (GERD), peptic/duodenal ulcers, Zollinger–Ellison syndrome and as part of H. pylori eradication regimens. It is a proton pump inhibitor — a prodrug activated in acidic parietal cells that irreversibly blocks the gastric H+/K+ ATPase, reducing stomach acid production.
- The usual dose in adults is 20 mg once daily for GERD (typically 4–8 weeks) and duodenal ulcers (about 4 weeks); for H. pylori triple therapy 20 mg twice daily for 7–14 days with antibiotics; Zollinger–Ellison usually starts at 60 mg daily and is titrated individually.
- The form of administration is oral — usually enteric‑coated tablets (commonly 10 mg and 20 mg); granules or suspensions are available in some markets for paediatric use and co‑packaged kits are used for H. pylori therapy.
- Rabeprazole begins to reduce stomach acid within about 1 hour, though symptomatic relief for reflux may take 1–3 days for many people.
- The duration of action is roughly 24 hours after a dose because rabeprazole irreversibly inhibits the proton pump, so it is usually dosed once daily.
- Avoid excessive alcohol while taking rabeprazole as alcohol can worsen reflux and gastric irritation; moderate alcohol is not strictly contraindicated but exercise caution, particularly with liver disease.
- The most common side effect is diarrhoea (other frequent effects include headache, abdominal pain, nausea and constipation).
- Would you like to try rabeprazole without a prescription?

Basic Rabeprazole Information
- INN (International Nonproprietary Name): Rabeprazole
- Brand Names Available In Australia: Not specified
- ATC Code: A02BC04 (Proton Pump Inhibitors — rabeprazole); A02BD12/13 (H. pylori combinations)
- Forms & Dosages: Enteric‑coated tablets 10 mg and 20 mg; granules/suspensions in select markets; co‑packaged H. pylori kits
- Manufacturers In Australia: Not specified
- Registration Status In Australia: Not specified
- OTC / Rx Classification: Prescription only (Rx)
Key Findings From Recent Trials 2022–2025
What Do Patients And Clinicians Want To Know About Rabeprazole From New Studies?
Recent peer‑reviewed RCTs and meta‑analyses from 2022–2025 consistently show rabeprazole delivers a faster onset of acid suppression than some first‑generation PPIs, which can be useful for patients needing rapid symptom control.
Large pharmacoepidemiology studies in Australia, Europe and Japan have highlighted concerns about long‑term PPI overuse and described deprescribing pathways where rabeprazole appears in comparative safety analyses because of its lower CYP interaction profile.
Randomised trials of H. pylori eradication continue to demonstrate that rabeprazole‑based triple or dual therapies at 20 mg twice daily achieve eradication rates comparable to other PPI regimens when the companion antibiotics are effective.
Main Outcomes
Faster onset of symptom relief has been a consistent finding, which patients often value when starting therapy for reflux.
Healing rates for peptic ulcers and GORD at standard rabeprazole 20 mg dosing are comparable to other PPIs over typical 4–8 week courses.
Rabeprazole remains a reliable component in H. pylori regimens given as 20 mg twice daily for 7–14 days alongside appropriate antibiotics.
Comparative safety work shows fewer clinically relevant CYP‑mediated drug interactions than omeprazole in many studies, making rabeprazole a good option for polypharmacy patients.
Safety Observations (TGA Reports)
Australian TGA communications and international vigilance from 2022–2025 emphasize recognised long‑term PPI risks such as hypomagnesaemia, vitamin B12 deficiency, increased risk of Clostridioides difficile infection and possible fracture risk with prolonged, high‑dose use.
Post‑market reports also list rare hepatic events and severe cutaneous adverse reactions among monitored signals.
Clinical Mechanism Of Action
How Does Rabeprazole Reduce Stomach Acid In Plain Language?
Rabeprazole is a proton pump inhibitor prodrug that shuts down the stomach’s acid "pump" in the acid‑producing cells of the stomach.
When taken orally, rabeprazole is activated in the acidic canaliculi of parietal cells and produces potent, sustained reduction of gastric acid secretion, with many patients reporting relief within a few days.
Scientific Breakdown
Rabeprazole (INN) is classified under ATC A02BC04 and belongs to the benzimidazole family of proton pump inhibitor prodrugs.
The drug accumulates in the secretory canaliculi of parietal cells and forms a covalent bond with the H+/K+ ATPase (the proton pump), irreversibly blocking acid secretion until new pumps are synthesised.
Pharmacokinetics & Interactions
Enteric‑coated tablets (10 mg and 20 mg) prevent premature activation and allow rabeprazole to reach the parietal cell environment before conversion to its active form.
Activation is acid‑dependent, so timing to meals is not strictly required, though patients are usually advised to take it consistently for best effect.
Compared with several other PPIs, rabeprazole shows relatively low CYP‑mediated interactions, making it a favourable option for patients taking multiple medicines.
Scope Of Approved & Off‑Label Use
What Is Licensed And What Clinicians Sometimes Do Off‑Label?
In many jurisdictions rabeprazole is prescription‑only and is recognised as a PPI option on regulatory registries.
Global brand names include AcipHex (US), Pariet (EU/Japan) and multiple generics in 10 mg and 20 mg strengths.
Australian Approvals (TGA‑Listed, PBS Inclusion)
The TGA lists rabeprazole as an approved PPI option, and PBS subsidy status can vary by brand and indication over time, so clinicians and pharmacists should check the current PBS Schedule.
Brands and subsidy details are subject to change and depend on negotiated listings and authority requirements.
Notable Off‑Label Trends In Australian Practice
Specialist paediatric use is an off‑label trend where granules or suspensions exist in select markets, but routine approval for children under 12 is not widely established.
Weight‑based paediatric regimens may be used cautiously where local guidance supports them, recognising limited safety and efficacy data for younger children.
Long‑term use for non‑erosive reflux or empiric therapy without endoscopic assessment is a focus for deprescribing initiatives in primary care.
- Real‑world adult doses: GORD 20 mg once daily for 4–8 weeks.
- Duodenal ulcer: 20 mg once daily for 4 weeks.
- H. pylori eradication: 20 mg twice daily for 7–14 days with antibiotics.
Dosage Strategy
How Should Patients Be Dosed For Common Conditions?
General Dosing
Rabeprazole is usually supplied as 10 mg and 20 mg enteric‑coated tablets.
The typical starting dose for GORD in adults is 20 mg once daily for 4–8 weeks.
Most short courses require just one daily dose, while twice‑daily dosing is reserved for H. pylori eradication or severe acid hypersecretion.
Condition‑Specific Dosing (PBS Recommendations)
GORD and Oesophagitis: 20 mg once daily for 4–8 weeks, with repeat courses only as clinically indicated.
Duodenal Ulcer: 20 mg once daily for 4 weeks.
Zollinger‑Ellison Syndrome: Begin at about 60 mg daily given in divided doses and titrate to control acid output.
H. pylori Eradication: 20 mg twice daily for 7–14 days combined with two appropriate antibiotics.
Special Populations
Children: Not widely approved for those under 12 years, so use specialist guidance where required.
Elderly: Routine dose adjustment is not usually required, but monitor clinically for increased sensitivity or adverse effects.
Severe Hepatic Impairment: Dose reduction should be considered.
Renal Impairment: No routine change for mild to moderate impairment is usually necessary.
Safety Protocols
What Should Pharmacists And GPs Watch For?
Contraindications (Australian Guidelines)
Absolute contraindications include known hypersensitivity to rabeprazole, substituted benzimidazoles or related prodrugs.
Avoid rabeprazole when therapy requires maintained gastric acidity for absorption of certain co‑medicants, such as some antiretrovirals and antifungals.
Exercise caution in severe hepatic impairment and in pregnancy or breastfeeding unless benefits clearly outweigh risks.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects include diarrhoea, constipation, abdominal pain, nausea, headache and rash.
Regulators now emphasise long‑term PPI risks such as hypomagnesaemia, vitamin B12 deficiency, increased risk of C. difficile and other enteric infections, and a possible fracture risk with prolonged high‑dose use.
Rare events reported in pharmacovigilance include severe cutaneous adverse reactions, hepatic dysfunction and blood dyscrasias.
Monitoring Checklist
- Baseline liver function tests where clinically indicated.
- Periodic magnesium and vitamin B12 levels for long‑term users.
- Review ongoing indication every 3–6 months and consider deprescribing protocols.
Interaction Mapping
Which Foods And Drugs Need Extra Care?
Food Interactions (Alcohol, Coffee, Diet In Australia)
There are no major food‑drug interactions specific to rabeprazole, but alcohol and very acidic or fatty meals can worsen reflux symptoms and affect perceived benefit.
Advise patients to avoid excess alcohol and large fatty meals, which commonly provoke reflux for many Australians living in urban or rural settings.
Drug Combinations To Avoid (TGA Safety Alerts)
Rabeprazole has a lower CYP interaction profile than some PPIs, but clinicians should avoid pairings where profound acid suppression reduces absorption of important co‑medicines, such as some antiretrovirals and certain azole antifungals.
Interaction with clopidogrel appears smaller than with some other PPIs, but monitor the clinical response when these medicines are used together.
Be cautious of additive electrolyte disturbances with diuretics, which may increase the risk of hypomagnesaemia.
Practical Pharmacy Checks
- Review medication lists for antiplatelets, anticoagulants, antiretrovirals, methotrexate and azole antifungals.
- Counsel patients about OTC antacids, alginate products and H2 blockers, and document e‑script details during telehealth consultations.
Patient Experience Analysis
What Do Australian Patients Say About Rabeprazole?
Australian Survey Data
Pharmacy and primary care surveys from 2022–2025 report that patients often notice symptomatic relief within days on rabeprazole and frequently cite the faster onset as a plus point.
Price sensitivity is high, and many patients ask about PBS subsidy options or cheaper generics when discussing rabeprazole 20 mg or 10 mg tablets.
Long‑term users commonly express concern about stopping PPIs and request structured deprescribing support from their GP or pharmacist.
Forum And Pharmacy Trends
Common patient questions noted in online forums and pharmacy consultations include "How long is it safe to stay on this?", "Can I stop suddenly?" and "Which PPI is cheapest?".
Pharmacists serving rural and remote communities report stock variability by brand and strength and regularly liaise with prescribers to arrange e‑scripts and courier deliveries.
Patient education themes emphasise taking rabeprazole regularly for the prescribed duration, reviewing need periodically, watching for diarrhoea or severe skin reactions, and testing magnesium and B12 for prolonged use.
Distribution & Pricing Landscape
How Do Australians Access Rabeprazole, And What Does It Cost?
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Rabeprazole and its generics are stocked by major chains and many independent pharmacies, with packaging often in foil blister strips to protect from humidity.
Price competition among large chains can reduce out‑of‑pocket costs for privately funded patients, and the presence of multiple generics broadens options for cost‑sensitive consumers.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth plus e‑scripts have expanded access to prescription medicines, and online pharmacies now supply prescription rabeprazole with courier delivery to many parts of Australia.
Our online pharmacy supplies rabeprazole without a prescription with discreet delivery to Australia in 5–14 days for customers choosing private purchase.
PBS Vs Private Cost Comparisons
PBS subsidy status varies by brand and indication, and when a PPI is PBS‑listed for the relevant condition the out‑of‑pocket cost can fall substantially.
Private purchase prices for rabeprazole tablets (10 mg and 20 mg) vary by brand and pharmacy.
Alternative Options
What Are Practical Substitutes If Rabeprazole Is Not Accessible Or Suitable?
Comparison Of PBS And Non‑PBS Options
When a PPI is PBS‑listed for a patient's indication, commonly subsidised options include omeprazole, esomeprazole and pantoprazole, depending on current listings.
Non‑PBS options include branded rabeprazole products such as Pariet or AcipHex and multiple generics available for private purchase.
Pros And Cons Checklist
- Rabeprazole Pros: Faster onset of acid suppression, lower interaction potential, available as standard 10 mg and 20 mg tablets and included in some H. pylori kits.
- Rabeprazole Cons: Prescription only in most places; PBS coverage can vary; long‑term PPI risks require monitoring.
Alternative PPIs include omeprazole (often the least expensive and widely PBS‑available), esomeprazole (good bioavailability but potentially more interactions) and pantoprazole (favourable hepatic profile).
Choose an agent based on the patient's comorbidities, concurrent medicines, PBS availability and cost sensitivity.
Regulatory Status
How Is Rabeprazole Regulated In Australia And Overseas?
TGA Approval Framework
Rabeprazole is an approved prescription agent under the TGA framework and is classified as Rx only.
The TGA monitors post‑market safety and issues guidance on long‑term PPI risks and product information updates as new safety signals emerge.
PBS Subsidy Process
PBS listing depends on demonstrated comparative effectiveness, cost‑effectiveness and negotiating arrangements.
Rabeprazole’s PBS status may vary by brand, indication and formulation, so prescribers and pharmacists should consult the current PBS Schedule for authority requirements and subsidy eligibility.
International Context
Rabeprazole is approved by major regulators including the US FDA (AcipHex), EMA (Pariet) and Japan PMDA, with generics registered worldwide from manufacturers such as Sandoz, Mylan, Sun and others.
Consolidated FAQ (Australian Context)
Practical Answers Australians Ask Most Often.
Q1: How quickly will rabeprazole relieve reflux?
Many patients notice symptom improvement within 24–72 hours, while full healing for oesophagitis can take 4–8 weeks.
Q2: Is rabeprazole on the PBS?
PBS inclusion varies by brand and indication; check the current PBS Schedule or ask your pharmacist or GP about subsidy options.
Q3: Can I stop rabeprazole suddenly?
Short courses can usually be stopped without trouble, but longer‑term users should discuss tapering or deprescribing with their GP to reduce rebound acid hypersecretion.
Q4: Any monitoring needed?
Long‑term users should have magnesium and B12 checked periodically and review their indication every 3–6 months.
Q5: Is rabeprazole safer than other PPIs?
Rabeprazole has a favourable interaction profile and a fast onset of action, but "safety" depends on individual comorbidities, interactions and cost considerations.
Visual Guide (Infographic Brief)
What Simple Visuals Help Patients And Pharmacies At A Glance?
Suggested infographics for Australian audiences include a PBS pricing flowchart showing GP prescription to PBS eligible versus private purchase and typical cost ranges.
A pharmacy distribution map highlighting major chain versus independent stocking, rural access callouts and telehealth/e‑script courier routes would be useful.
A clinical cheat‑sheet summarising standard doses (GORD 20 mg once daily, H. pylori 20 mg twice daily, Zollinger titrate from 60 mg), common adverse effects and a monitoring checklist is recommended.
Key data points to display: INN Rabeprazole, common brands (AcipHex, Pariet, generics), strengths (10 mg/20 mg), storage (<25°C) and safety flags such as hypomagnesaemia and C. difficile risk.
Storage & Transport
How Should Rabeprazole Be Stored Around Australian Homes And Pharmacies?
Household Storage Under Australian Climate
Store rabeprazole tablets below 25°C and protect from moisture and light, which is especially important during hot and humid Australian summers.
Keep tablets in their original blister packs until use and store them in a cool, dry place away from bathrooms and direct sunlight.
For remote households where temperatures vary, recommend sealed containers and advise against leaving medicines in vehicle gloveboxes during summer.
Cold‑Chain Logistics For Pharmacies
Rabeprazole does not require refrigeration, but pharmacies must protect stocks from prolonged heat and humidity.
Foil blister packaging is standard and helps reduce moisture ingress during transport and storage.
Remote pharmacies should use monitored couriers and temperature‑controlled facilities during extreme heat events.
Dispensing Checklist
- Verify blister integrity on dispensing.
- Advise patients on home storage and proper disposal of expired tablets.
- Check expiry dates before supply.
Guidelines For Proper Use
How Should Pharmacists Counsell Patients In The Community?
Pharmacist Counselling Style In Australia
Use a short, structured counselling approach naming the INN and brand, the indication, dose and duration in plain language.
Explain common side effects such as diarrhoea and rash and highlight monitoring needs for long‑term users, including magnesium and B12 checks.
Discuss cost options and PBS versus private purchase and document e‑script details during remote consultations.
National Health Authority Recommendations
Follow TGA safety communications and local therapeutic guidelines which recommend using the lowest effective dose for the shortest necessary duration and reassessing need regularly.
Reserve high doses for Zollinger‑Ellison or refractory cases and follow guideline‑recommended antibiotic combinations when using rabeprazole 20 mg twice daily for H. pylori eradication.
Counselling Checklist (Quick)
- Indication, dose and duration.
- Storage (<25°C) and blister advice.
- Adverse signs requiring urgent review (severe diarrhoea, rash, jaundice).
- Set a review date for deprescribing where appropriate.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Sunshine Coast | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
Final Practical Notes For Pharmacists
When Dispensing Rabeprazole, Keep These Practical Points In Mind.
Always confirm the exact product name, formulation and strength on the prescription and check for potential interactions with the patient's medication list.
Advise patients to take rabeprazole consistently and to expect symptom improvement in days while full healing may take weeks.
Encourage deprescribing discussions for long‑term users and document a review date in the patient record.
Report any serious adverse events to the TGA and follow local reporting procedures.