
Efavirenz
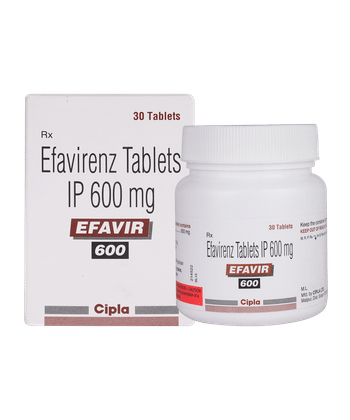
Efavirenz
- Efavirenz is a prescription-only antiretroviral in Australia and most countries and is supplied via hospital and community pharmacies (also available in fixed-dose combos such as Atripla). Some online or informal vendors may offer it without a prescription, but purchasing or using it without a valid prescription is not recommended and may be unsafe.
- Efavirenz is used for the treatment and prevention of HIV‑1 infection as part of combination antiretroviral therapy; it is a non‑nucleoside reverse transcriptase inhibitor (NNRTI) that blocks HIV reverse transcriptase, preventing viral replication.
- The usual adult dose is 600 mg orally once daily (WHO DDD 0.6 g/day); paediatric dosing is weight‑based (e.g. ≥35 kg: 600 mg once daily) and PEP regimens typically include 600 mg daily as part of a combination for 28 days.
- Administered orally as tablets (commonly 600 mg and 200 mg) or capsules (paediatric strengths), and in fixed‑dose combination tablets (eg, with emtricitabine and tenofovir in Atripla); take with or after food to improve absorption.
- Plasma concentrations peak in about 3–5 hours and CNS effects (dizziness, vivid dreams) can begin within hours; measurable antiviral effects on viral load typically emerge over days to weeks of therapy.
- Efavirenz has a long elimination half‑life (around 40–55 hours), allowing once‑daily dosing; therapeutic antiviral effect is maintained with continuous daily dosing as part of combination ART.
- Avoid excessive alcohol while taking efavirenz — alcohol can worsen CNS side effects (drowsiness, dizziness, mood changes) and may increase risk of liver toxicity; exercise caution and discuss alcohol use with your clinician.
- The most common side effects are central nervous system symptoms such as vivid dreams, insomnia, dizziness and impaired concentration; other common effects include nausea, rash and liver enzyme elevations.
- Would you like to try efavirenz without a prescription?

Basic Efavirenz Information
- INN (International Nonproprietary Name): Efavirenz.
- Brand Names Available In Australia: Stocrin and Atripla (marketed by MSD Australia and Gilead).
- ATC Code: J05AG03 for efavirenz monotherapy; combination code J05AR06 for emtricitabine/tenofovir disoproxil/efavirenz.
- Forms & Dosages: Tablets 600 mg and 200 mg; capsules 50 mg (paediatric) and 200 mg; fixed‑dose combination tablet containing efavirenz 600 mg + emtricitabine 200 mg + tenofovir disoproxil 300 mg (Atripla).
- Manufacturers In Australia: Originator and combination suppliers include Bristol‑Myers Squibb (brand history), Gilead and MSD Australia; generics supplied globally by Teva, Mylan, Sandoz and others.
- Registration Status In Australia: Registered with national regulatory approval and historically PBS‑listed in fixed‑dose combinations; WHO lists efavirenz on the Model List of Essential Medicines and multiple generics are WHO prequalified.
- OTC / Rx Classification: Prescription only (Rx) in Australia.
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Clinicians ask whether efavirenz still has a role now that dolutegravir is common.
Recent evidence from 2022–2024 compares efavirenz‑containing regimens with integrase inhibitors in both randomised trials and cohort data.
Australian cohort analyses and international meta‑analyses show virological suppression is comparable at 48–96 weeks when adherence is excellent.
Trials have continued to examine efavirenz as part of fixed‑dose combinations such as Atripla and in PEP regimens in resource‑limited settings.
Generics and WHO prequalified fixed‑dose combinations support ongoing availability and low cost in many markets.
Efavirenz remains included on the WHO Model List of Essential Medicines and has a WHO DDD of 0.6 g per day.
Main Outcomes
High adherence delivers similar suppression rates between efavirenz 600 mg regimens and integrase inhibitor regimens at standard follow‑up points.
Efavirenz retains utility in specific clinical scenarios, especially where cost, prior resistance patterns or drug–drug interactions favour an NNRTI.
Atripla fixed‑dose convenience continues to be valued by patients for once‑daily dosing and reduced pill burden.
Safety Observations (TGA Reports)
TGA and international pharmacovigilance from 2022–2024 reinforce known CNS adverse events including insomnia, vivid dreams and depression.
Post‑market reports continue to record rare severe dermatological reactions such as Stevens–Johnson syndrome and toxic epidermal necrolysis.
Australian regulators have not identified novel safety signals beyond the established efavirenz profile during that period.
Clinical Mechanism Of Action
Layman’s Explanation
People worry how efavirenz actually stops HIV replication.
Efavirenz is a non‑nucleoside reverse transcriptase inhibitor that blocks HIV‑1’s reverse transcriptase so the virus cannot copy its RNA into DNA and spread in the body.
It is taken once daily, usually as a single 600 mg tablet, and is always used in combination with other antiretrovirals.
Scientific Breakdown
Efavirenz binds a hydrophobic pocket adjacent to the active site of HIV‑1 reverse transcriptase causing conformational change and impaired DNA polymerisation.
The drug is inactive against HIV‑2 and so is not used for that infection.
Pharmacokinetics And Metabolism
Efavirenz has a long elimination half‑life that supports once‑daily dosing and steady exposure overnight.
Absorption increases when taken with food, especially high‑fat meals, which can raise plasma concentrations.
Metabolism is predominantly hepatic via CYP2B6 and to a lesser extent CYP3A4.
Genetic polymorphisms in CYP2B6 that produce slow metabolisers can increase plasma efavirenz levels and the likelihood of CNS adverse effects.
Resistance Mechanism
Resistance can arise from single‑step mutations in the reverse transcriptase gene such as K103N that confer high‑level resistance to efavirenz and many first‑generation NNRTIs.
That low genetic barrier to resistance is why efavirenz is never used as monotherapy and must be given in combination ART.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Pharmacists and prescribers need to know TGA and PBS status when advising patients about cost and supply.
Efavirenz is TGA‑registered in Australia under brand names including Stocrin and in combination as Atripla.
Historically, Atripla and some efavirenz generics have been PBS‑subsidised, improving access through community pharmacies.
Indications in Australia include treatment of HIV‑1 in adults and weight‑banded paediatric dosing when used as part of combination ART.
Notable Off‑Label Trends In Australian Practice
In rural and remote settings clinicians have continued to prescribe efavirenz where access to dolutegravir or interaction concerns with tuberculosis therapies complicate choices.
Some specialists have trialled dose‑reduction or split dosing in CYP2B6 slow metabolisers to manage CNS toxicity, but these are specialist strategies rather than standard PBS substitutions.
Pregnancy counselling is important because efavirenz carries teratogenicity concerns and women of child‑bearing potential should discuss contraception and alternatives with their prescriber.
Dosage Strategy
General Dosing
People often ask what dose to take and how to time it for sleep and side effects.
Standard adult dosing is efavirenz 600 mg taken orally once daily with or after a light meal to improve absorption.
The WHO defined daily dose is 0.6 g per day, matching the common 600 mg adult dose.
Condition‑Specific Dosing (PBS Recommendations)
Paediatric dosing is weight‑based with 50 mg capsules and 200 mg or 300 mg tablets used for lower weight bands and 600 mg for children ≥35 kg.
For post‑exposure prophylaxis efavirenz has been used historically at 600 mg daily as part of a 28‑day triple therapy regimen.
Dose adjustment is advised for moderate‑to‑severe hepatic impairment and caution is recommended in the elderly; renal impairment rarely requires adjustment because renal clearance is minor.
Pharmacists should verify indication and weight for paediatric dispensings and ensure PBS authority codes and prescriber instructions are followed.
Safety Protocols
Contraindications (Australian Guidelines)
Patients commonly want to know who must not take efavirenz.
Absolute contraindications include known hypersensitivity to efavirenz or excipients and severe hepatic impairment.
Co‑administration with certain agents such as voriconazole, elbasvir/grazoprevir and St John’s Wort is contraindicated.
Women of child‑bearing potential require effective contraception or alternative agents because of teratogenicity concerns and AU pregnancy category D guidance.
Adverse Effects (Post‑Market Pharmacovigilance)
TGA and international surveillance continue to report central nervous system effects such as insomnia, vivid dreams, dizziness and mood disturbances.
Psychiatric symptoms including depression and suicidal ideation are noted as important precautions, and a history of psychiatric disease is a relative contraindication.
Severe rash including Stevens–Johnson syndrome is a rare but serious dermatological effect and requires immediate medical attention.
Baseline and periodic liver function tests and lipid monitoring are standard practice to detect hepatic enzyme elevations and lipid disturbances.
Pharmacists must counsel patients to report new mood changes or severe rashes immediately and to document adverse events for TGA reporting.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Patients often ask whether diet or alcohol affect efavirenz action or side effects.
Taking efavirenz with a substantial meal increases absorption and may increase CNS adverse effects, so Australian advice commonly recommends a light snack rather than a high‑fat meal.
Excessive alcohol should be avoided when initiating therapy because of additive CNS depression and the potential for decreased judgement around adherence.
Caffeine such as coffee is acceptable but counsel about sleep disruption if taken late in the day.
Drug Combinations To Avoid (TGA Safety Alerts)
Efavirenz is a CYP2B6 substrate and induces CYP3A4, producing clinically significant interactions.
St John’s Wort is contraindicated because it induces metabolism and can lower efavirenz levels leading to potential loss of efficacy.
Concomitant use may reduce levels of some antifungals and hormonal contraceptives, so pharmacists should advise on alternative contraception or regimen adjustments.
TGA safety notices list specific contraindicated and cautionary combinations that should be checked at each supply.
Patient Experience Analysis
Australian Survey Data
Patients commonly want to know how others tolerate efavirenz compared with newer drugs.
Surveys and clinic reports in Australia from 2020–2024 show many patients value once‑daily convenience and the fixed‑dose Atripla tablet for adherence.
A solid minority report persistent CNS symptoms such as vivid dreams and insomnia that prompt switching to alternatives like dolutegravir.
Community pharmacists report longer counselling times for efavirenz versus integrase inhibitors due to side‑effect management and contraception discussions.
Forum And Pharmacy Trends
Online forums can amplify rare events, so pharmacists should provide balanced, evidence‑based counselling and direct patients to support services.
Rural and remote patients emphasise price sensitivity and PBS reliance, and they report practical issues such as stockouts or limited local supply.
Telehealth and postal delivery have become important tools to maintain continuity of antiretroviral therapy for patients outside major urban centres.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Large community chains source efavirenz products through national wholesalers and manage PBS authority processes for subsidised supplies.
Branded products and generics such as Stocrin, Atripla and efavirenz generics from Teva or Mylan are distributed to both community and hospital pharmacies.
Availability in a given store can depend on supplier contracts and PBS listings that affect price and stock rotation.
Online Pharmacy Growth And Telehealth E‑Scripts
Online pharmacy services and telehealth e‑scripts have improved access for remote patients and enabled repeat dispensing and discreet postal delivery.
In our online pharmacy, efavirenz is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Pharmacists must still verify PBS entitlements and authority approvals when arranging subsidised shipment.
PBS Vs Private Cost Comparisons
PBS subsidy historically reduces out‑of‑pocket costs significantly for concession and general patients, while private purchase without authority can be expensive for branded tablets.
Generics reduce private cost for those paying out of pocket, and pharmacists should check for available generics from manufacturers such as Teva, Mylan and Sandoz.
Price sensitivity is common and influences patient choices and continuity of therapy in some regions.
Alternative Options
Comparison Of PBS And Non‑PBS Options
Dolutegravir and bictegravir‑based regimens are now preferred first‑line in many Australian guidelines because of better tolerability and higher resistance barrier.
Rilpivirine, etravirine and other NNRTIs may be options in selected patients but have their own suitability constraints such as food or PPI interactions for rilpivirine.
Many dolutegravir formulations are PBS‑listed and may be fully subsidised, while efavirenz generics remain a low‑cost option for some patients.
Pros And Cons Checklist
- Pros: Once‑daily dosing, fixed‑dose Atripla convenience, well‑known efficacy and low‑cost generics.
- Cons: Higher rates of CNS adverse events, teratogenicity concerns, and a low genetic barrier to resistance (single‑mutation risk).
Individual therapy choice should balance efficacy, tolerability, drug–drug interactions such as tuberculosis therapy, and PBS access.
Regulatory Status
TGA Approval Framework
The Therapeutic Goods Administration assesses safety, efficacy and manufacturing quality for registration in Australia.
Efavirenz products including Stocrin and combination tablets such as Atripla are prescription‑only and TGA‑registered.
Post‑market surveillance by the TGA informs safety communications and potential label updates.
PBS Subsidy Process
Medications gain PBS subsidy following PBAC recommendation and listing with specified authority requirements and item codes.
Fixed‑dose combinations like Atripla have been PBS‑listed historically, permitting subsidised patient access subject to authority rules.
Pharmacists should check current PBS schedules and authority forms before dispensing subsidised efavirenz formulations.
Consolidated FAQ
Patients frequently ask practical questions about efavirenz in the Australian context.
-
Is Efavirenz Still Recommended In Australia?
Efavirenz remains approved and used in Australia, but many clinicians now favour dolutegravir‑based regimens for first‑line therapy.
Efavirenz is still relevant for some patients and clinical situations, including where drug interactions or cost considerations apply.
-
Can I Take Efavirenz With Alcohol Or Coffee?
Avoid excessive alcohol when starting efavirenz because of additive CNS depression.
Coffee is acceptable but counsel about sleep disruption and timing to reduce insomnia and vivid dreams.
-
What If I Miss A Dose?
Take the missed dose as soon as remembered unless it is close to the next scheduled dose; do not double the dose.
-
Is It Covered By PBS?
Many efavirenz formulations including Atripla and some generics have been PBS‑listed historically, but pharmacists should confirm current PBS schedules and authority requirements.
-
Pregnancy Concerns?
Efavirenz has teratogenicity warnings; women of child‑bearing potential should discuss contraception and alternative regimens with their prescriber.
Visual Guide
Design assets help patients and clinics quickly understand supply, dosing and safety.
A suggested PBS pricing flowchart should show patient pathways for concession, general and private purchasing and highlight how generics lower typical out‑of‑pocket ranges.
A pharmacy distribution map should contrast national chains with rural and remote supply lines, and include telehealth and postal delivery icons for continuity.
A safety infographic should display a quick checklist for CNS symptoms, rash and pregnancy warnings with clear action steps and TGA reporting guidance.
A dosage pocket card should list adult dosing of 600 mg once daily, paediatric weight bands and the WHO DDD of 0.6 g.
Storage & Transport
Household Storage Under Australian Climate
Patients frequently ask how to store tablets during hot Australian summers.
Store efavirenz below 30°C and protect it from moisture and light, avoiding bathrooms and cars on hot days.
If tablets appear discoloured or degraded after heat exposure, advise patients to consult their pharmacist before taking them.
Cold‑Chain Logistics For Pharmacies
Efavirenz does not require cold‑chain storage, but pharmacies should monitor ambient storage areas and rotate stock to avoid expiry.
For rural deliveries use insulated packaging if transit exposes stock to prolonged high temperatures, and always ship in original packaging with patient information leaflets.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Good counselling is patient‑centred, structured and practical.
Check indication, weight for paediatric patients, pregnancy status, concomitant medicines and mental health history before supply.
Advise to take efavirenz 600 mg once daily with a light snack, warn about vivid dreams and sleep changes and instruct to report severe mood changes or rash immediately.
Offer adherence tools such as dose alarms, blister packs or multi‑dose dispensing and arrange follow‑up for LFTs and clinical review with the prescriber.
National Health Authority Recommendations
TGA and ASHM‑influenced guidance affirm that efavirenz should be used as part of combination ART and that resistance testing is important before changing regimens.
Report adverse events to the TGA and liaise with specialist services for complex cases, particularly in rural settings where telehealth can improve specialist access.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5‑7 days |
| Melbourne | Victoria | 5‑7 days |
| Brisbane | Queensland | 5‑7 days |
| Perth | Western Australia | 5‑7 days |
| Adelaide | South Australia | 5‑7 days |
| Canberra | Australian Capital Territory | 5‑7 days |
| Hobart | Tasmania | 5‑7 days |
| Gold Coast | Queensland | 5‑9 days |
| Newcastle | New South Wales | 5‑9 days |
| Wollongong | New South Wales | 5‑9 days |
| Geelong | Victoria | 5‑9 days |
| Cairns | Queensland | 5‑9 days |
| Townsville | Queensland | 5‑9 days |
Storage And Transport Practical Tips
For multi‑dose dispensing provide clear written instructions on storage below 30°C and protection from moisture and light.
Advise patients to keep medicines in original packaging during travel and to contact the pharmacy before extended trips or heatwaves.
Document supply details for PBS dispensing and provide contingency advice if stockouts occur in rural areas.
Guidelines For Proper Use — Final Notes
Use a collaborative counselling approach: confirm the regimen, check interactions such as St John’s Wort and TB therapy, and screen for psychiatric history.
Reinforce that efavirenz must always be used in combination ART and never alone.
Encourage adherence strategies and regular monitoring including viral load checks organised by the prescriber and LFTs as clinically indicated.
If CNS symptoms or severe rash occur, instruct patients to seek urgent medical review and report the event to the TGA through the prescriber or pharmacist.