
Lanoxin
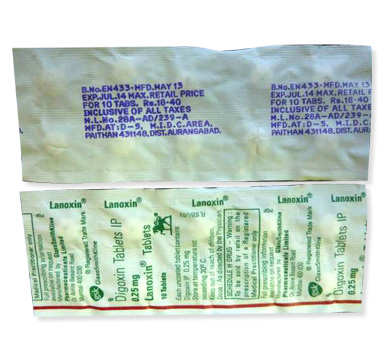
Lanoxin
- In our pharmacy, you can buy lanoxin without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Lanoxin (digoxin) is used for chronic heart failure and for rate control in atrial fibrillation; it is a cardiac glycoside that inhibits the Na+/K+ ATPase, increasing intracellular calcium to produce a positive inotropic effect and increasing vagal tone to slow AV nodal conduction.
- The usual dose in adults is 0.125–0.25 mg once daily (individualised to response and serum levels); in children the usual dose is about 5–10 mcg/kg/day (weight‑based, may require loading in some cases).
- Administered orally (tablets 0.0625 mg, 0.125 mg, 0.25 mg; oral solution/elixir) or intravenously (ampoules/vials for injection).
- Onset of action: oral effects generally begin within 30–120 minutes; intravenous effects often begin within 5–30 minutes; rate control and full clinical response may take longer as levels are titrated.
- Duration of action: digoxin has a long half‑life (around 36–48 hours in adults), with clinical effects persisting for 1–3 days; dosing is usually once daily.
- Alcohol warning: avoid excessive alcohol—alcohol can worsen heart failure and may increase the risk of adverse effects and arrhythmias when taking digoxin.
- The most common side effect is nausea (other frequent effects include vomiting, diarrhoea, dizziness and visual disturbances such as blurred or yellow vision).
- Would you like to try lanoxin without a prescription?
Basic Lanoxin Information
- INN (International Nonproprietary Name): Digoxin
- Brand Names Available In Australia: not specified
- ATC Code: C01AA05 (Cardiac Glycosides, Digoxin)
- Forms & Dosages: Tablets 0.0625 mg, 0.125 mg, 0.25 mg; Oral elixir 0.05 mg/mL; Injection 0.25 mg/mL (2 mL ampoule)
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only (Rx) in all major markets
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Main Outcomes
Recent observational cohorts and meta-analyses from 2022 to 2024 have emphasised digoxin's narrow therapeutic window rather than any new mortality benefit.
Large registry analyses in Europe and North America consistently associated serum digoxin concentrations above 1.0 ng/mL with higher all‑cause mortality.
Lower therapeutic ranges, typically 0.5–0.9 ng/mL, were linked to symptomatic improvement in heart failure and effective rate control in atrial fibrillation.
Australian clinicians have not reported large new randomised controlled trials to 2024, with guidance shaped by pharmaco‑epidemiology and registry data.
Clinical practice has trended toward precision dosing and routine serum monitoring instead of liberal chronic prescribing.
Safety Observations (TGA Reports)
TGA communications have reflected international safety signals focusing on overdose risk, drug–drug interactions and the impact of renal impairment.
Post‑market TGA reports and periodic safety updates highlight interacting medicines and falling renal function as common contributors to hospital presentations with digoxin toxicity.
Regulators recommend careful monitoring of levels and renal function and caution when starting P‑glycoprotein inhibitors or drugs that alter electrolytes.
Clinical Mechanism Of Action
Layman’s Explanation
Many patients ask how lanoxin helps their heart work better.
Digoxin strengthens heart contractions and slows a fast heartbeat, which helps people with heart failure and atrial fibrillation feel less breathless and improves rate control.
That symptomatic benefit often makes daily activities easier for frail or low‑blood‑pressure patients who cannot tolerate higher doses of other heart medicines.
Scientific Breakdown
Digoxin inhibits the Na+/K+‑ATPase pump in cardiomyocytes, increasing intracellular sodium.
Higher intracellular sodium reduces the driving force for the Na+/Ca2+ exchanger and indirectly increases intracellular calcium, producing positive inotropy.
Digoxin also augments vagal tone at the atrioventricular node, slowing conduction velocity and prolonging the refractory period, which helps control ventricular rate in atrial fibrillation.
Pharmacokinetics
Oral bioavailability varies by formulation, with tablets and elixir showing reliable absorption when taken consistently.
Elimination is predominantly renal, and the plasma half‑life is prolonged in renal impairment.
Therapeutic Window
Target trough concentrations for chronic therapy are generally 0.5–0.9 ng/mL.
Toxicity risk increases when serum digoxin approaches or exceeds approximately 1.0 ng/mL.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Digoxin, often known under the brand Lanoxin and as generics, is registered internationally for heart failure and atrial fibrillation rate control.
Raw product data state indications include heart failure in adults and children from age five and atrial fibrillation rate control in adults.
Generic digoxin is commonly dispensed under PBS subsidy for eligible patients, subject to standard concession or general patient co‑payment rules.
Notable Off‑Label Trends In Australian Practice
Where symptoms persist despite guideline therapy, Australian cardiologists and GPs may use low‑dose digoxin adjunctively in chronic heart failure with reduced ejection fraction.
Clinicians also consider digoxin for frail elderly patients whose blood pressure limits uptitration of beta‑blockers or ACE inhibitors/ARNIs.
Specialist‑led use continues for refractory tachyarrhythmias and paediatric weight‑based regimens, always with emphasis on serum monitoring and renal adjustment.
Dosage Strategy
General Dosing
Digoxin is supplied in tablets of 0.0625 mg, 0.125 mg and 0.25 mg, an oral elixir 0.05 mg/mL and injectable ampoules 0.25 mg/mL.
Adult maintenance doses are commonly 0.125–0.25 mg once daily, and doses must be individualised to weight, renal function and concomitant drugs.
Condition‑Specific Dosing (PBS Recommendations)
For heart failure, clinicians typically start low—often 0.125 mg once daily—and titrate to clinical response and serum troughs of 0.5–0.9 ng/mL.
Atrial fibrillation dose strategies are similar, with the goal of adequate rate control while staying within the lower therapeutic range.
Paediatric dosing is weight‑based, generally 5–10 mcg/kg/day given orally, using the paediatric elixir or divided tablet dosing under specialist supervision.
Neonates and infants require specialist dosing and close monitoring.
In the elderly and in renal impairment, doses should be substantially reduced or dosing intervals extended because of reduced clearance.
Loading doses are uncommon in chronic therapy and are reserved for supervised inpatient initiation when rapid control is needed and monitoring is available.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include ventricular fibrillation, known hypersensitivity to digoxin or other digitalis glycosides, acute myocarditis and severe atrioventricular block or sick sinus syndrome unless a pacemaker is in place.
Relative contraindications that require monitoring include electrolyte imbalances, renal impairment and thyroid disorders.
Before initiating therapy, clinicians should check an ECG and baseline electrolytes, thyroid and renal function.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects reported in post‑marketing surveillance include nausea, vomiting, diarrhoea, dizziness, headache and fatigue.
Neuro‑visual disturbances—such as blurred or yellow vision and halo phenomena—are classical signs suggestive of digoxin toxicity.
Arrhythmias or palpitations can indicate serious toxicity and require urgent assessment.
TGA and other regulatory reports often list interacting drugs and declining renal function as precipitating causes of hospitalisation with digoxin toxicity.
Local practice protocols favour regular serum trough testing and renal monitoring every three to six months, or sooner if clinical risk factors change.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
No major food classes directly change digoxin absorption substantially, but high‑fibre meals may modestly reduce absorption.
Alcohol does not directly alter digoxin pharmacokinetics but can worsen heart failure symptoms and arrhythmia risk and therefore should be used cautiously.
Because electrolyte disturbances increase toxicity risk, diets or conditions that cause hypokalaemia should be managed aggressively.
Drug Combinations To Avoid (TGA Safety Alerts)
Major interacting drugs include amiodarone, verapamil, macrolide antibiotics such as clarithromycin, azole antifungals like itraconazole, and other P‑glycoprotein inhibitors or inducers.
Loop and thiazide diuretics may predispose to hypokalaemia and thus enhance digoxin toxicity risk.
TGA and international safety alerts stress careful review when starting medicines such as amiodarone or macrolides and recommend level checks after initiation.
Pharmacists should flag potential interactions at discharge and during dispensing, particularly in regional settings where specialist review may be delayed.
Patient Experience Analysis
Australian Survey Data
Surveys and community pharmacy feedback show patients appreciate the symptom relief digoxin can provide but express anxiety about toxicity and managing multiple medicines.
Many patients rely on their pharmacist for dosing clarification, monitoring schedules and identification of adverse effects.
Community pharmacists report frequent queries about visual changes, nausea and what to do about missed doses.
Forum And Pharmacy Trends
Online forums reflect price sensitivity and reliance on PBS subsidy, with rural patients particularly concerned about travel for blood testing.
Pharmacists increasingly use MedsCheck and Home Medicines Review services to support adherence and identify interacting medicines.
Telehealth scripts and community nursing blood draws are practical measures helping rural patients access monitoring more easily.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Major chains and independent chemists stock Lanoxin and generic digoxin formulations in tablets and elixir form.
Community pharmacists commonly recommend generic digoxin to reduce patient out‑of‑pocket expense while ensuring equivalent dosing strengths are used.
Online Pharmacy Growth And Telehealth E‑Scripts
Online pharmacies and telehealth e‑scripts have expanded access, allowing patients to order maintenance supplies by e‑prescription for home delivery or local pick‑up.
In our online pharmacy, lanoxin is available without a prescription, with discreet delivery to Australia in 5-14 days.
Patients should remember that local dispensing rules and PBS eligibility still apply for subsidised supplies.
PBS Vs Private Cost Comparisons
Generic digoxin is commonly available under the PBS, and concession cardholders usually pay the lower PBS co‑payment while general patients meet the standard copay.
Private scripts are inexpensive compared with many other cardiac medicines but remain costlier than PBS‑subsidised supplies.
Price sensitivity often drives generic substitution when formulations and pack sizes are equivalent.
Supply disruptions are uncommon but can occur; pharmacists will substitute an equivalent strength or formulation and counsel patients on any changes.
Alternative Options
Comparison Of PBS And Non‑PBS Options
Alternatives to digoxin include digitoxin, beta‑blockers such as bisoprolol and metoprolol, and antiarrhythmics like amiodarone for rate or rhythm control.
Many of these alternatives are PBS‑listed for heart failure or atrial fibrillation but have different indications, side‑effect profiles and monitoring needs.
Pros And Cons Checklist
- Digoxin — Pro: useful in elderly patients with low blood pressure and available as an oral elixir for paediatrics.
- Digoxin — Con: narrow therapeutic window, renal clearance dependent and numerous drug interactions.
- Beta‑Blockers — Pro: mortality benefit in heart failure with reduced ejection fraction.
- Beta‑Blockers — Con: may worsen fatigue or obstructive lung disease symptoms in some patients.
- Amiodarone — Pro: effective antiarrhythmic for rhythm control.
- Amiodarone — Con: risk of long‑term organ toxicities requiring regular monitoring.
Regulatory Status
TGA Approval Framework
Digoxin products such as Lanoxin and generics are registered in many jurisdictions, and TGA evaluations mirror international standards for quality, safety and efficacy.
Post‑marketing obligations include periodic safety update reports and ongoing pharmacovigilance, with safety advisories published if new risks are identified.
PBS Subsidy Process
PBS subsidy requires demonstration of clinical need, cost‑effectiveness and alignment with accepted clinical practice for listing.
Many digoxin formulations are available as PBS‑listed generics, and pharmacists ensure substitution and PBS eligibility rules are followed at dispensing.
Consolidated FAQ
Q1: Is Lanoxin on the PBS?
A: Generic digoxin formulations are commonly PBS‑listed; check your script and concession status at your pharmacy.
Q2: How often do I need blood tests?
A: Baseline renal function and electrolytes, plus a digoxin trough after steady state (usually 5–7 days after a dose change), then every three to six months or sooner with renal change or interacting medicines.
Q3: Can I drink alcohol or coffee?
A: Moderate alcohol may worsen heart failure and should be used cautiously; coffee does not directly interact with digoxin, but maintain a stable diet and report new symptoms.
Q4: What if I miss a dose?
A: Take the dose when you remember unless it is close to the next dose; do not double the dose to make up for a missed one.
Q5: What are the signs of overdose?
A: Symptoms include nausea, vomiting, visual changes (blurring or yellow vision), confusion and palpitations — seek emergency care if these occur.
Visual Guide
Designers should prepare three clear infographics to support patient understanding and pharmacy workflows.
Infographic 1: PBS Pricing Flowchart — show concession versus general patient copays and example per‑script costs for generic digoxin tablets in common pack sizes 0.125 mg and 0.25 mg.
Infographic 2: Pharmacy Distribution Map — urban versus rural coverage showing prevalence of Chemist Warehouse, Priceline and TerryWhite, and mail‑order coverage with telehealth e‑script pathways.
Infographic 3: Monitoring Timeline — baseline labs, trough timing at steady state and routine checks every three to six months, plus icons for renal function checks and visual symptom alerts.
Each infographic should use Australian colours, include accessible alt text and use TGA/PBS logos only where permitted by branding rules.
Storage & Transport
Household Storage Under Australian Climate
Store tablets, elixir and ampoules at room temperature, ideally 20–25°C, and avoid humidity and direct heat sources such as bathrooms.
Protect medicines from the extreme heat common in some Australian summers and never leave them in an uncooled car or on a hot beach towel.
Keep all preparations out of reach of children and in their original packaging to reduce dosing errors.
Cold‑Chain Logistics For Pharmacies
Injectable ampoules typically do not require refrigeration but must be protected from prolonged high heat during transport.
Pharmacies and online dispensers should use insulated packaging and avoid delivery during the hottest part of the day for rural deliveries in summer.
Pharmacists should advise patients about safe carriage during travel, such as weekend trips or long drives.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Begin counselling by confirming the indication and explaining the expected benefits for symptom control and rate management.
Ask about all prescription and non‑prescription medicines, and highlight common interacting drugs and the need for electrolyte and renal monitoring.
Explain once‑daily timing, what to do about missed doses, and the classical toxicity signs such as visual disturbances, nausea and palpitations.
Use MedsCheck or Home Medicines Review for patients on multiple medicines, and document follow‑up arrangements for blood tests and level checks.
National Health Authority Recommendations
Australian and international guidance stresses targeting lower trough concentrations (~0.5–0.9 ng/mL), renal dose adjustment and multidisciplinary care when initiating or changing therapy.
Special attention should be given to Aboriginal and Torres Strait Islander patients and culturally diverse communities, using culturally safe communication and local outreach testing where needed.
Concluding Notes For Clinicians And Patients
Digoxin remains a useful option for symptom control in selected patients when used with careful dosing and monitoring.
Regular serum digoxin checks, electrolyte monitoring and medication reconciliation are the cornerstones of safe therapy.
Pharmacists play a valuable role in counselling, preventing interactions and arranging practical monitoring options for rural patients.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
Quick Reference And Practical Tips
Keep a record of digoxin dose, last blood test date and current serum digoxin concentration in the patient’s medicine list.
When a new medicine is started, particularly amiodarone, verapamil, macrolides or azole antifungals, arrange digoxin level checks and consider dose adjustment.
In renal impairment, reduce doses or lengthen dosing intervals and increase monitoring frequency.
Always advise patients to report visual changes, persistent gastrointestinal upset or palpitations promptly.
Useful Dispensing Checklist For Pharmacists
- Confirm indication and dose strength on the prescription.
- Review renal function, electrolytes and recent digoxin level where available.
- Check for interacting medicines and counsel on signs of toxicity.
- Arrange or remind patients about timing for trough level testing after any dose change.
- Document counselling and follow‑up plan in the pharmacy record.
Where To Get Help
For urgent concerns about possible overdose or severe adverse effects, advise patients to attend the nearest emergency department.
For dosing and interaction questions, contact the dispensing pharmacist, the prescribing doctor or a cardiologist as appropriate.
Community pharmacists can arrange MedsCheck or Home Medicines Review referrals for complex cases and support rural patients with telehealth follow‑up and local blood‑draw arrangements.