
Clopidogrel
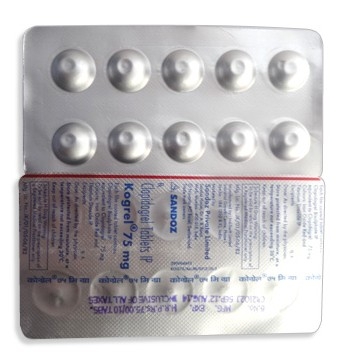
Clopidogrel
- Clopidogrel is a prescription-only medicine and should be dispensed by a pharmacy with a valid prescription; it is not available over the counter in Australia or most countries due to bleeding risk and the need for clinical monitoring.
- Clopidogrel is used to prevent blood clots in conditions such as acute coronary syndromes, after percutaneous coronary intervention (PCI), and for secondary prevention of stroke, myocardial infarction and peripheral arterial disease; it is a thienopyridine antiplatelet that irreversibly blocks the P2Y12 (ADP) receptor on platelets, reducing platelet aggregation.
- Typical dosing: a loading dose of 300–600 mg once for urgent antiplatelet effect (e.g. ACS/PCI), then maintenance dosing of 75 mg once daily for long‑term prevention.
- Administered orally as film‑coated tablets (commonly 75 mg; 300 mg tablets used for loading doses); fixed‑dose combinations with aspirin exist in some markets.
- Onset: platelet inhibition begins within a few hours after a loading dose (effects often detectable within ~2 hours, with more pronounced effect by about 6 hours); onset is slower with a single 75 mg maintenance dose.
- Duration: clopidogrel causes irreversible platelet inhibition—individual platelets are affected for their lifespan (around 7–10 days); daily dosing maintains steady antiplatelet effect.
- Alcohol warning: avoid excessive alcohol while taking clopidogrel as alcohol can increase the risk of gastrointestinal bleeding and bruising; limit alcohol intake and discuss concerns with your prescriber.
- The most common side effects are bruising and minor bleeding (such as nosebleeds or gum bleeding); other common effects include diarrhoea, abdominal pain and dyspepsia; rare but serious risks include major gastrointestinal or intracranial bleeding and thrombotic thrombocytopenic purpura.
- Would you like to try clopidogrel without a prescription?
Basic Clopidogrel Information
- INN (International Nonproprietary Name): Clopidogrel
- Brand Names Available In Australia: not specified
- ATC Code: B01AC04
- Forms & Dosages: Tablets 75 mg (maintenance) and 300 mg (loading); fixed-dose combinations such as clopidogrel 75 mg + aspirin 75 mg available in some markets
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only medicine (Rx)
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Worried which antiplatelet will protect you best after a heart attack or stent?
Recent systematic reviews and multicentre randomised controlled trials from 2022 to 2024 show a consistent pattern for acute coronary syndrome treated with PCI.
Newer P2Y12 agents such as ticagrelor and prasugrel were associated with fewer ischaemic events compared with clopidogrel in ACS populations.
Those same trials reported higher rates of major bleeding with ticagrelor and prasugrel than with clopidogrel in comparable patients.
Registry analyses from Australia and international cohorts through 2022–24 support clopidogrel’s ongoing role for long-term secondary prevention in stroke, peripheral arterial disease and stable coronary disease.
Where bleeding risk is high or cost is a limiting factor, clopidogrel remains a pragmatic choice according to real-world data.
Genotype-guided de‑escalation trials and studies of short dual‑antiplatelet therapy showed non-inferiority for selected groups, reducing bleeding without a major increase in ischaemic events.
These de‑escalation and short-DAPT trends are influencing prescribing patterns in Australia, particularly when clinicians balance ischaemic benefit with bleeding risk and budget considerations.
Main Outcomes
- Reduced myocardial infarction and stent thrombosis seen with ticagrelor or prasugrel versus clopidogrel in ACS settings.
- Improved bleeding profiles when switching or de‑escalating to clopidogrel after an early period of potent therapy.
Safety Observations (TGA Reports)
Concerned about safety reports from regulators?
TGA pharmacovigilance reflects global safety signals, with the most frequent adverse-event reports involving bleeding and rare haematological events.
Thrombotic thrombocytopenic purpura and other rare blood dyscrasias are recognised but uncommon.
Clopidogrel remains prescription-only in all jurisdictions and requires clinician oversight for changes in therapy.
Clinical Mechanism Of Action
Layman’s Explanation
Worried about how clopidogrel actually works in the body?
Clopidogrel is an antiplatelet prodrug that reduces the chance of dangerous clots by preventing platelets from sticking together.
The usual maintenance dose is 75 mg taken once daily to keep platelet activity lowered over time.
A single loading dose of 300–600 mg is used to achieve rapid protection in emergencies such as heart attack or during PCI.
Scientific Breakdown
Want the technical details behind the lay explanation?
Clopidogrel (INN; ATC B01AC04) irreversibly inhibits the platelet P2Y12 ADP receptor, decreasing platelet aggregation.
Pharmacokinetics & Activation
- Clopidogrel is a prodrug and requires hepatic cytochrome P450-mediated bioactivation to an active thiol metabolite.
- CYP2C19 is a major enzyme in the activation pathway, and variability in this enzyme affects drug activation.
- Genetic polymorphisms that reduce CYP2C19 function result in lower active metabolite formation and reduced antiplatelet effect.
Pharmacodynamics
- The active metabolite irreversibly inhibits P2Y12 receptors on platelets, so the antiplatelet effect lasts for the lifespan of affected platelets — about 7–10 days.
- Clinical antiplatelet effect diminishes as new platelets are produced after stopping therapy.
- Genetic variability underpins the rationale for genotype‑guided strategies and can affect choice of subsidised therapy on the PBS.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Unsure when clopidogrel is used in Australia?
Clopidogrel is registered worldwide as a prescription antiplatelet agent and is routinely prescribed in Australia for secondary prevention after myocardial infarction.
It is also used after ischaemic stroke or TIA, for peripheral arterial disease and in post‑PCI contexts depending on the clinical scenario.
Many formulations are available globally — the originator Plavix and multiple generics in 75 mg maintenance and 300 mg loading strengths are widely distributed.
PBS listing covers approved indications and provides subsidised access for eligible patients, which influences prescribing choices in the community.
Notable Off‑Label Trends In Australian Practice
Wondering about common workarounds clinicians use?
Australian clinicians sometimes use clopidogrel off‑label as part of combination or sequencing strategies, starting with a potent agent and de‑escalating to clopidogrel later to reduce bleeding risk.
Clopidogrel is also favoured in frail or older patients where a lower potency antiplatelet may be safer.
Fixed‑dose clopidogrel plus aspirin tablets exist in some international markets but are uncommon on the PBS in Australia.
Dosage Strategy
General Dosing
Not sure what to take and when?
The standard maintenance dose is 75 mg once daily for most adults.
Loading doses of 300–600 mg are used when immediate platelet inhibition is needed, such as in ACS or before PCI.
Tablets are commonly sold as 75 mg, with some brands offering a 300 mg film‑coated tablet for loading.
If a dose is missed, take it as soon as you remember but do not double up the next day.
There is no specific antidote for clopidogrel overdose; supportive measures and platelet transfusion may be required in major bleeding.
Condition‑Specific Dosing (PBS Recommendations)
- ACS/PCI: Loading dose 300–600 mg then 75 mg daily for at least 12 months depending on stent type and individual risk profile.
- Secondary Prevention (ischaemic stroke, MI, PAD): 75 mg daily long term unless bleeding risk requires stopping.
- Elderly: Routine dose reduction is not required but monitor closely for bleeding.
- Severe hepatic impairment: Use with caution due to increased bleeding risk and limited data.
- Children: Not approved; safety and efficacy not established.
Safety Protocols
Contraindications (Australian Guidelines)
Worried clopidogrel might be unsafe for you?
Absolute contraindications include active pathological bleeding such as peptic ulcer or intracranial haemorrhage and known hypersensitivity to clopidogrel or its excipients.
Use with caution in patients with bleeding disorders, recent major surgery, severe liver impairment, or when combined with anticoagulant therapy.
Adverse Effects (Post‑Market Pharmacovigilance)
Want to know what side effects to watch for?
Common adverse effects are bruising and minor bleeding such as nosebleeds or gum bleeding, plus dyspepsia or diarrhoea.
Less common effects include rash, headache and dizziness.
Serious but rare events include major gastrointestinal or intracranial haemorrhage, neutropenia and thrombotic thrombocytopenic purpura.
TGA and international pharmacovigilance continue to emphasise bleeding risk and rare haematological reactions, so clinicians balance ischaemic benefit against bleeding propensity when prescribing.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Wondering if your diet affects clopidogrel?
There are no major food‑drug interactions requiring specific dietary restrictions for clopidogrel.
Alcohol can increase bleeding risk and should be limited while taking antiplatelet medication.
No strong grapefruit interaction has been documented for clopidogrel activation, though caution is reasonable with herbal supplements such as St John’s wort that can induce CYP enzymes.
Drug Combinations To Avoid (TGA Safety Alerts)
Curious which medicines clash with clopidogrel?
Certain proton pump inhibitors, notably omeprazole, may reduce clopidogrel activation via CYP2C19 inhibition and should be avoided where possible.
Pantoprazole is generally preferred if a PPI is required.
Concomitant use of anticoagulants, non‑steroidal anti‑inflammatory drugs and some antidepressants (SSRIs/SNRIs) increases bleeding risk and needs careful assessment.
Strong CYP2C19 inhibitors or inducers can alter clopidogrel efficacy and should prompt review of therapy and counselling on bleeding signs.
Patient Experience Analysis
Australian Survey Data
Are patients actually taking clopidogrel as prescribed?
Australian survey and adherence studies indicate common barriers to ongoing therapy include bleeding concerns, complex post‑ACS medication regimens and out‑of‑pocket costs where PBS co‑payments apply.
When pharmacists explain that generics are therapeutically equivalent, many patients accept switching from branded Plavix to clopidogrel generics and adherence improves.
Medication reviews such as Home Medicines Review help identify adherence problems and reduce confusion, especially for older patients on multiple drugs.
Forum And Pharmacy Trends
What do people ask community pharmacists about?
Community pharmacies report frequent questions about bruising, when to stop clopidogrel before surgery and about switching from branded Plavix to generics like Clopidogrel Mylan or Clopidogrel Teva.
Rural patients often face longer travel times for cardiology follow‑up and rely heavily on community pharmacists for counselling and continuity of care.
Telehealth e‑scripts and online pharmacies have increased convenience, but continuity and proper counselling remain essential to avoid interruptions in therapy.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Wondering where to buy clopidogrel in Australia?
Clopidogrel, both branded and generic, is widely stocked by major chains and independent community pharmacies across Australia.
Chains may offer competitive private prices, and pharmacists can often switch patients to cost‑effective generic clopidogrel where appropriate.
Online Pharmacy Growth And Telehealth E‑Scripts
Can you get clopidogrel without leaving home?
Growth in telehealth has made e‑scripts and online dispensing more common, improving access for many patients, especially in regional areas.
In our online pharmacy, clopidogrel is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
Worried about the cost of ongoing therapy?
The PBS subsidises clopidogrel for eligible indications, reducing out‑of‑pocket costs for concession cardholders and general patients once Safety Net thresholds are reached.
Private purchase of clopidogrel generics is more expensive and cost sensitivity can affect adherence when patients face ongoing co‑payments.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
| Medicine | PBS Status | Key Features |
|---|---|---|
| Clopidogrel 75 mg | PBS‑listed for approved indications | Once‑daily, cost‑effective, variable response in CYP2C19 poor metabolisers |
| Ticagrelor (Brilinta) | PBS‑subsidised in specific ACS indications | More potent, reversible inhibition, higher bleeding risk, twice‑daily dosing |
| Prasugrel (Efient) | PBS in selected PCI populations | Potent irreversible inhibitor; contraindicated after prior stroke/TIA; caution in elderly |
| Aspirin | Widely available | Low cost, often part of dual antiplatelet therapy or alone for some indications |
Pros And Cons Checklist
- Clopidogrel Pros: Cost‑effective, once‑daily dosing, well‑established for long‑term secondary prevention.
- Clopidogrel Cons: Variable response in CYP2C19 poor metabolisers, less effective in high‑risk ACS populations versus newer agents.
- Choice depends on ischaemic versus bleeding risk, genetic profile, cost and PBS eligibility.
Regulatory Status
TGA Approval Framework
Curious how clopidogrel is regulated in Australia?
Clopidogrel is approved under standard regulatory pathways requiring sponsors to submit clinical data on quality, safety and efficacy.
Risk minimisation measures include approved product information and ongoing pharmacovigilance obligations for sponsors.
PBS Subsidy Process
How does PBS decide which drugs to subsidise?
PBS listing requires clinical and economic evidence submitted to the Pharmaceutical Benefits Advisory Committee for comparative effectiveness and cost‑effectiveness review.
Once listed, PBS subsidy determines patient access nationally and strongly influences prescribing patterns.
Consolidated FAQ
Have a quick question? These are the ones patients ask most.
- Q1: Can I stop clopidogrel before surgery? Don’t stop clopidogrel without clinician advice because stopping increases thrombotic risk.
- Q2: What if I miss a dose? Take it as soon as you remember unless it is almost time for the next dose; do not double up.
- Q3: Is genetic testing needed? Genetic testing for CYP2C19 is not routinely funded; consider it if treatment failure or high risk is suspected and genotype‑guided strategies are available.
- Q4: Can I drink alcohol? Limit alcohol while taking antiplatelet therapy because it increases bleeding risk.
- Q5: Can I switch from ticagrelor to clopidogrel? Switching is commonly done under clinician guidance as part of de‑escalation protocols after the initial high‑risk period, or for cost or bleeding concerns.
Visual Guide
Would an infographic help you decide?
- Infographic 1: PBS Pricing & Access Flowchart showing concession versus general patient costs and Safety Net thresholds for clopidogrel 75 mg.
- Infographic 2: Pharmacy Distribution Map highlighting urban versus rural density of major chains and the role of telehealth and online pharmacy growth.
- Infographic 3: DAPT Timeline from loading to potent agent to possible de‑escalation, with icons for bleeding and ischaemic risk and colour coding for PBS versus private options.
Storage & Transport
Household Storage Under Australian Climate
Worried about heat and humidity affecting your tablets?
Store clopidogrel tablets at room temperature between 15–30°C and keep them dry and protected from light.
Avoid bathroom storage in hot or humid Australian homes and keep medicines in original blister packs or airtight pill bottles away from children and pets.
Always check expiry dates and discard any degraded or discoloured tablets.
Cold‑Chain Logistics For Pharmacies
How should pharmacies handle stock in summer?
Clopidogrel is a stable oral solid and does not require cold‑chain logistics.
Pharmacies should store stock at controlled ambient conditions, rotate stock regularly and protect packaging integrity during transport.
Rural deliveries should account for transit time and heat exposure, bearing in mind temperature control needs of other co‑dispensed medicines.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
What should you expect from your pharmacist?
Pharmacists should proactively counsel patients on indication, dosing (including when a loading dose is used), bleeding signs and interactions with PPIs, NSAIDs and anticoagulants.
Use teach‑back techniques for surgical planning and provide written action plans for bleeding or emergency contacts.
Offer Home Medicines Reviews for complex patients and additional follow up for those in rural areas to maintain continuity of care.
National Health Authority Recommendations
Which guidelines guide prescribers?
Follow national cardiology and stroke guidelines for DAPT duration and secondary prevention and incorporate TGA product information and PBS criteria when prescribing.
Consider genotype‑guided approaches where available and cost‑effective, and review therapy at follow‑up to balance ischaemic protection against bleeding risk.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
Concluding Notes For Patients And Clinicians
Still unsure whether clopidogrel is right for you?
Discuss individual ischaemic and bleeding risks with your cardiologist or GP when choosing between clopidogrel and alternatives such as ticagrelor or prasugrel.
Genetic testing for CYP2C19 is an emerging tool to guide therapy but is not yet routine or universally funded.
Pharmacists play a key role in counselling about dosing, interactions and when to contact a clinician about bleeding or planned surgery.
When cost is a concern, the PBS can reduce out‑of‑pocket expenses for eligible patients, and generic clopidogrel options are widely available and suitable when clinically appropriate.