
Marevan
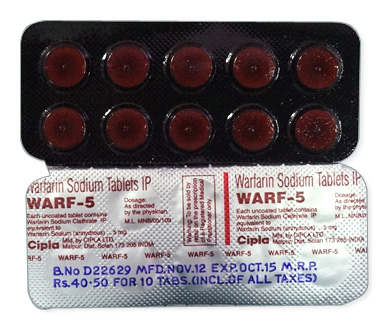
Marevan
- In our pharmacy, you can buy marevan without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Marevan (warfarin) is used to prevent and treat venous thromboembolism, reduce stroke risk in atrial fibrillation and prevent thromboembolism with prosthetic heart valves; it is a vitamin K antagonist that inhibits vitamin K epoxide reductase, reducing activation of clotting factors II, VII, IX and X.
- The usual dose is an initial 2–5 mg per day, with maintenance typically 2–10 mg per day individualised by INR monitoring; usual INR target is 2.0–3.0 (2.5–3.5 for mechanical valves).
- The form of administration is oral tablet (commonly 1 mg, 2 mg, 2.5 mg, 3 mg, 5 mg and 10 mg tablets); no standard injectable or liquid oral forms for human use.
- The onset of anticoagulant effect is delayed: reduction in clotting begins within 24–72 hours and full effect is usually seen after about 3–5 days.
- The duration of action is prolonged—anticoagulant effects can persist for 2–5 days after stopping therapy (half-life is variable), so dosing is generally once daily and effects are sustained.
- Avoid excessive alcohol: alcohol can unpredictably increase or decrease INR and bleeding risk, so limit intake and inform your clinician about drinking habits.
- The most common side effect is minor bleeding (for example, nosebleeds, gum bleeding) and easy bruising; serious bleeding is less common but possible.
- Would you like to try marevan without a prescription?
Basic Marevan Information
- INN (International Nonproprietary Name): Warfarin
- Brand Names Available In Australia: Marevan (GlaxoSmithKline, Aspen Pharmacare) and Coumadin are marketed in Australia, with Marevan commonly supplied as blister packs or bottles in 1 mg, 3 mg and 5 mg strengths.
- ATC Code: B01AA03
- Forms & Dosages: Tablets in multiple strengths are sold internationally; most common strengths include 1 mg, 2 mg, 3 mg, 5 mg and 10 mg, with Marevan in Australia typically available as 1 mg, 3 mg and 5 mg tablets.
- Manufacturers In Australia: Aspen Pharmacare (previously Boots Healthcare/Mylan distribution links) and other global suppliers such as Bristol‑Myers Squibb may supply warfarin products; Marevan is associated with GlaxoSmithKline and Aspen Pharmacare.
- Registration Status In Australia: Registered with the Therapeutic Goods Administration (TGA) as a prescription medicine.
- OTC / Rx Classification: Prescription only (Rx) — warfarin is classified as a prescription medicine worldwide.
Key Findings From Recent Trials
What do recent studies tell us about warfarin use compared with newer options?
Recent meta‑analyses and registries from 2022–24 continue to show direct oral anticoagulants generally outperform warfarin for non‑valvular atrial fibrillation, particularly for lower intracranial haemorrhage rates.
Australian observational anticoagulation clinic data from 2022–24 report declining warfarin use for atrial fibrillation and venous thromboembolism in favour of DOACs, while warfarin remains the standard for mechanical prosthetic valves.
Randomised data since 2022 reinforce the need for individualised INR targets and note greater variability in INR control among older patients on warfarin.
TGA post‑market pharmacovigilance (2022–24) lists bleeding as the predominant serious adverse event, with interactions and monitoring lapses common contributors.
Emerging 2024–25 surveillance focuses on telehealth‑driven INR management and rural access inequities in Australia.
The strongest recent signal for Australian practice is that warfarin retains a clear niche in valvular disease and remains safe when INR monitoring is consistent.
When gaps in monitoring occur the risk of harm rises, according to TGA reports and local anticoagulation services.
Main Outcomes
Which clinical outcomes stood out across trials and registries?
DOACs show similar or lower stroke rates with fewer intracranial bleeds compared with warfarin in non‑valvular AF studies from 2022 onwards.
Australian registry updates reflect reduced warfarin prescribing for AF and VTE, matched by increased DOAC uptake where PBS criteria allow.
For mechanical valves and some high‑risk antiphospholipid syndrome cases, warfarin remains the treatment with established outcome data.
Safety Observations (TGA Reports)
What safety patterns does the TGA highlight for warfarin?
TGA pharmacovigilance from 2022–24 identifies bleeding as the main serious adverse event linked to warfarin, often associated with drug interactions or missed INR monitoring.
Reports draw attention to anticoagulant management issues in telehealth settings and to rural areas where point‑of‑care INR access is variable.
Clinical Mechanism Of Action
How does warfarin work in plain terms?
Warfarin is an oral anticoagulant that reduces the blood’s ability to clot by blocking vitamin K‑dependent clotting factors.
Patients take daily tablets such as Marevan 1 mg, 3 mg or 5 mg and have INR blood tests to find the correct dose.
Scientific Breakdown
What is happening at the biochemical level?
Warfarin inhibits the vitamin K epoxide reductase complex (VKORC1), preventing the regeneration of reduced vitamin K needed for gamma‑carboxylation of clotting factors II, VII, IX and X and proteins C and S.
Onset and offset are delayed because clotting factors have half‑lives up to about 72 hours, so full anticoagulant effect requires days and dose changes are guided by INR trends.
Genetic variations (VKORC1, CYP2C9), diet and interacting medicines cause large interpatient variability, which is why routine INR monitoring is essential.
Scope Of Approved & Off‑Label Use
Which conditions is warfarin approved for in Australia and where is it still favoured?
Warfarin is TGA‑registered and typically PBS‑subsidised for stroke prevention in atrial fibrillation, treatment and prevention of venous thromboembolism, and prevention of thromboembolism in mechanical heart valves.
Clinicians continue to favour warfarin for mechanical prosthetic valves and certain high‑risk antiphospholipid syndrome cases where DOACs are contraindicated.
Rural prescribers sometimes continue warfarin where DOAC access or PBS criteria limit options, or where local INR monitoring infrastructure is strong.
Emerging practice in Australia includes hybrid models where DOACs are first‑line for many patients, with warfarin reserved for indications needing dose titration or specific monitoring.
Dosage Strategy
How is warfarin dosing typically started and adjusted?
Initial dosing commonly starts between 2–5 mg per day and maintenance dosing is tailored to achieve the target INR, often between 2.0 and 3.0 for atrial fibrillation and VTE.
Higher INR targets (about 2.5–3.5) are used for some mechanical valves.
Dose adjustments are incremental and based on serial INR values rather than abrupt large changes.
Loading regimens are generally avoided in older or frail patients, and paediatric dosing is specialist‑led and weight‑based.
Marevan tablets in 1 mg, 3 mg and 5 mg strengths make fine titration possible in community practice.
Condition‑Specific Dosing (PBS Recommendations)
What does the PBS and clinical practice recommend for common indications?
PBS‑aligned practice keeps INR targets of 2.0–3.0 for most AF and VTE indications, with higher targets for certain prosthetic valves as clinically indicated.
Short‑term treatment is typically 3–6 months for provoked DVT or PE, while atrial fibrillation or mechanical valve therapy may be indefinite depending on risk.
Elderly patients often start at lower doses (for example, around 2 mg/day) with careful titration and monitoring.
Safety Protocols
Who should not take warfarin and what safety steps reduce risk?
Absolute contraindications include pregnancy, active major bleeding, severe uncontrolled hypertension, severe hepatic impairment and known warfarin hypersensitivity.
Relative risks include frequent falls, poor adherence and concomitant antiplatelet therapy which require careful clinical review.
Common adverse effects are minor bleeding such as nosebleeds or gum bleeding, bruising and GI upset, while serious but rare events include intracranial haemorrhage, skin necrosis and purple toe syndrome.
TGA surveillance from 2022–24 highlights drug interactions and monitoring lapses as major contributors to serious events, so clear monitoring schedules and patient education are essential.
Pharmacists play an important role in counselling, providing anticoagulation cards and facilitating access to vitamin K and hospital bleed pathways when needed.
Contraindications (Australian Guidelines)
Which conditions absolutely preclude warfarin use?
Pregnancy is an absolute contraindication because of teratogenicity and fetal bleeding risk, except in highly specialised mechanical valve scenarios under specialist care.
Active major bleeding, recent high‑bleeding‑risk surgery, severe liver impairment and severe uncontrolled hypertension are other absolute exclusions.
Adverse Effects (Post‑Market Pharmacovigilance)
What adverse events are reported to the TGA?
Mild events include minor bleeding, bruising and hair loss, while moderate effects include GI upset and rash.
Serious events reported to the TGA between 2022–24 most commonly involve major bleeding, often associated with interacting medicines or missed INR monitoring.
Interaction Mapping
Which foods and habits affect warfarin, and which medicines are risky combinations?
Vitamin K intake from green leafy vegetables such as spinach or kale can alter warfarin effect, so patients are advised to keep dietary intake consistent rather than avoid such foods entirely.
Alcohol can acutely increase bleeding risk and chronic heavy use affects liver metabolism and INR stability.
Major interacting medicines include broad‑spectrum antibiotics, amiodarone, metronidazole, trimethoprim‑sulfamethoxazole, fluconazole, SSRIs/SNRIs, and any NSAID or antiplatelet drug due to additive bleeding risk.
Herbal products such as St John’s wort may reduce warfarin activity and ginkgo may increase bleeding risk, both of which are mentioned in safety alerts.
Pharmacists should reconcile medicines, check e‑script lists and advise temporary INR checks when interacting drugs are started.
Food Interactions (Alcohol, Coffee, Diet In Australia)
What practical dietary advice helps keep INR stable?
Consistency is key: eat a steady amount of vitamin K‑containing foods rather than making sudden large changes in intake.
Coffee culture and moderate alcohol consumption are common in Australia and should be discussed with patients, with heavier alcohol intake discouraged while on warfarin.
Drug Combinations To Avoid (TGA Safety Alerts)
Which combinations have triggered TGA warnings?
TGA safety communications and pharmacovigilance tend to highlight combinations with NSAIDs and antiplatelets, and drugs that alter gut flora such as antibiotics which can reduce vitamin K production.
Any new medicine started should prompt review of the warfarin dose and consideration of more frequent INR checks.
Patient Experience Analysis
What do Australian patients say about taking warfarin?
Surveys and clinic feedback from 2022–24 show that patients who have easy access to INR testing are generally satisfied with warfarin as a reliable treatment.
Many patients report frustration with frequent blood tests, dietary considerations and numerous drug interactions, especially where telehealth or rural care limits testing access.
Community pharmacies and pharmacist‑led anticoagulation clinics improve adherence and outcomes by offering education and quick INR checks.
Online forums often describe warfarin as “old but reliable” when monitoring is consistent, while many patients prefer DOACs purely for convenience where appropriate and PBS‑eligible.
Australian Survey Data
Where do patients experience the greatest burdens with warfarin?
Rural and remote patients frequently cite travel time and scheduling burdens for INR testing, and some use point‑of‑care testing at pharmacies to reduce disruption.
Pharmacists are commonly the first point of contact for medication queries about Marevan and warfarin tablets, and many patients trust their local pharmacist for counselling.
Distribution & Pricing Landscape
Where can Australians buy Marevan and how much does it cost?
Marevan and generic warfarin tablets are widely available through national chains such as Chemist Warehouse, Priceline and TerryWhite, as well as independent pharmacies.
Under the PBS, warfarin is typically subsidised for eligible patients, making out‑of‑pocket costs low compared with non‑subsidised DOAC therapy.
Private scripts for warfarin remain inexpensive due to generic competition in Australia.
Online pharmacy growth and telehealth e‑scripts have markedly increased since 2020, allowing many patients to order repeats online with local pharmacy delivery.
When ordering from an online pharmacy, always ensure prescription verification and expect counselling from the dispensing pharmacist.
National Pharmacy Chains And Online Growth
How do chain and online pharmacies affect access?
National chains stock Marevan strengths such as 1 mg, 3 mg and 5 mg and support home delivery, while independent community pharmacies provide local INR point‑of‑care testing in many regions.
Online pharmacy ordering is convenient for repeat dispensing, but pharmacists remain responsible for patient counselling and ensuring safe supply.
PBS Vs Private Cost Comparisons
How does PBS subsidy change the cost picture?
Concession patients on the PBS typically pay a low co‑payment for warfarin, while general patients also benefit from PBS pricing when eligible.
Private purchase of generic warfarin tablets is usually cheap compared with the monthly cost of DOACs when DOACs are not PBS‑subsidised for a patient.
Alternative Options
What are the main alternatives to warfarin and how do they compare?
Direct oral anticoagulants such as apixaban, rivaroxaban, dabigatran and edoxaban are commonly used alternatives and are PBS‑listed for many AF and VTE indications.
DOACs provide predictable anticoagulation without routine INR monitoring, but are not suitable for mechanical valves and have restricted use in some thrombophilias.
Warfarin pros include low drug cost, established reversibility with vitamin K and strong evidence in valvular disease, while cons include frequent INR monitoring and many interactions.
DOAC pros are convenience and fewer interactions, while cons are cost for non‑PBS patients and renal dosing considerations.
Comparison Table Of PBS And Non‑PBS Options
- Warfarin (Marevan): PBS‑listed for standard indications, requires INR monitoring, inexpensive, reversible with vitamin K.
- DOACs (Eliquis, Xarelto, Pradaxa, Lixiana): Increasing PBS coverage for AF/VTE, fixed dosing, no routine INR checks, cost varies by PBS eligibility.
Pros And Cons Checklist
How should patients choose between warfarin and DOACs?
Choice depends on clinical indication, PBS eligibility, comorbidities, renal function, patient preference and access to INR monitoring services.
Regulatory Status
How is warfarin regulated in Australia?
Warfarin (ATC B01AA03) is registered with the TGA as a prescription‑only medicine and branded formulations in Australia include Marevan and generics.
The TGA oversees product quality, labelling and post‑market safety reporting and issues safety communications when pharmacovigilance signals arise.
The PBS listing process requires evidence of clinical and cost‑effectiveness and negotiated pricing with the Department of Health.
Community pharmacists must follow PBS dispensing rules, record keeping and verify patient entitlements at supply.
TGA Approval Framework
What does TGA registration mean for Marevan?
TGA registration confirms the product is approved as a prescription medicine and is subject to ongoing pharmacovigilance and recall processes.
PBS Subsidy Process
How does a warfarin product get subsidised?
PBS listing follows assessment of clinical effectiveness and cost‑effectiveness, and many warfarin products are PBS‑listed for specified indications to keep patient costs low.
Consolidated FAQ
What are the common questions patients ask about Marevan in Australia?
Q1: How often will I need an INR test?
A1: Initially several times a week until stable, then typically every 4–12 weeks depending on stability and clinical context.
Q2: Can I eat leafy greens?
A2: Yes — but keep your intake consistent; sudden increases or decreases in vitamin K foods can change INR.
Q3: What if I miss a dose?
A3: Take the missed dose as soon as remembered the same day and do not double the next day; contact your pharmacist or clinic for tailored advice.
Q4: Is Marevan on the PBS?
A4: Yes — warfarin products are generally PBS‑subsidised for approved indications; check with your pharmacy for current listing details.
Q5: Can I switch to a DOAC?
A5: Possibly — switching depends on the indication, renal function and PBS eligibility and should be discussed with your GP or specialist.
Visual Guide
What should be included in helpful infographics for patients and pharmacists?
- PBS Versus Private Cost Bar Chart Showing Concession And General Patient Costs For Marevan 1 mg/3 mg/5 mg.
- Pharmacy Distribution Map That Highlights Urban Coverage By National Chains Versus Rural Gaps And Point‑Of‑Care INR Locations.
- INR Monitoring Flowchart From Initiation To Stable Maintenance Frequency, With Common INR Targets (2.0–3.0 And 2.5–3.5).
- Interaction Wheel Showing Foods, Common Interacting Medicines And Herbs With Clear Action Steps.
Captions and data points for designers should include Marevan strengths (1 mg, 3 mg, 5 mg), TGA registration, emergency steps for major bleed (vitamin K, PCC) and pharmacist roles in counselling.
Storage & Transport
How should Marevan tablets be stored at home in Australia?
Store warfarin tablets at room temperature between 15–30°C, protected from moisture and light, and keep them in their original packaging.
Avoid leaving medication in cars or in direct sunlight, particularly in Australia's hot climate, and keep all medicines out of reach of children.
Cold‑Chain Logistics For Pharmacies
Does Marevan require cold‑chain during transport?
Warfarin tablets are shelf‑stable and do not require a cold chain, but pharmacies must monitor stock rotation and packaging integrity and plan deliveries around extreme weather in rural areas.
Guidelines For Proper Use
How should Australian pharmacists counsel patients taking Marevan?
Use a collaborative, evidence‑based counselling style that assesses indication, medication list, diet, alcohol and adherence while coordinating INR monitoring.
Provide clear plain‑language advice about bleeding signs, missed doses, interactions and when to seek urgent care, and use teach‑back to confirm understanding.
Give patients an anticoagulation card and document counselling and follow up, especially after dose changes or when new medicines are started.
For rural patients, arrange point‑of‑care INR testing at community pharmacies or coordinate with local health services to maintain safe monitoring.
Pharmacist Counselling Style In Australia
What communication techniques work best?
Be practical, patient‑centred and specific, offering examples such as how to split Marevan 1 mg tablets or when to bring a dose history to an INR check.
National Health Authority Recommendations
Which guidelines should pharmacists follow?
Align counselling and monitoring with TGA guidance, PBS recommendations and specialist society guidance on INR targets, monitoring intervals and indications like mechanical valves.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-9 days |
| Hobart | Tasmania | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Geelong | Victoria | 5-9 days |
Consolidated FAQ Recap
What practical reminders should patients keep with them?
Carry your anticoagulation card, keep a consistent diet, make arrangements for INR testing when travelling and tell any treating clinician you are on Marevan or warfarin tablets.
Emergency And Missed Dose Advice
What should patients do in urgent situations?
For major bleeding or suspected overdose, seek urgent hospital care where vitamin K and prothrombin complex concentrate may be given.
For a missed dose take it the same day if remembered and do not double up the next day; contact your pharmacist for tailored advice if uncertain.
Practical Pharmacy Notes
How do pharmacies support safe use?
Pharmacists provide medication reconciliation, check for interacting medicines such as antibiotics or amiodarone, and advise on frequency of INR monitoring after any change.
Community pharmacies often offer point‑of‑care INR testing or can direct patients to local anticoagulation clinics for titration of Marevan tablets.
Final Safety Reminders
What are the key takeaways for safe use of Marevan?
Maintain regular INR testing, tell clinicians about all medicines and supplements, keep diet reasonably consistent, and contact your pharmacist or clinic if you experience unusual bleeding or bruising.
Discuss any desire to switch to a DOAC with your GP or specialist, particularly if you have mechanical valves or specific thrombophilia where warfarin remains the preferred choice.
In our online pharmacy, marevan is available on prescription with discreet delivery to Australia in 5-14 days.