
Lotrisone
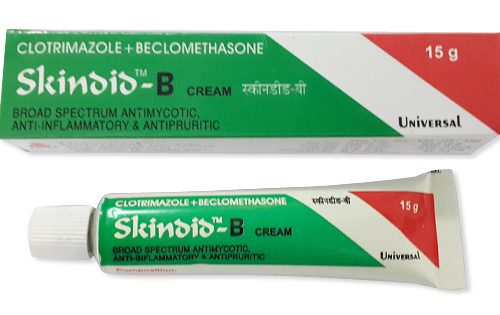
Lotrisone
- In our pharmacy you can buy lotrisone without a prescription, with delivery across Australia in 5–14 days and discreet packaging.
- Lotrisone is used to treat fungal skin infections (athlete’s foot, jock itch, ringworm); it combines clotrimazole (an azole antifungal that inhibits fungal ergosterol synthesis) with betamethasone dipropionate (a potent topical corticosteroid that reduces inflammation, itching and redness).
- Usual dose for adults and adolescents 17+ is a thin film applied to the affected area twice daily — for up to 2 weeks for tinea corporis/cruris and up to 4 weeks for tinea pedis; do not exceed 45 g per week. Safety in under‑17s is not established and use should be by prescription only in children.
- Administered topically as a cream (most commonly 1% clotrimazole / 0.05% betamethasone dipropionate in 15 g or 30 g tubes); a lotion form exists in some regions.
- Symptom relief (reduced itching and inflammation) is often apparent within 24–48 hours, with visible improvement in a few days; full antifungal clearance can take days to weeks depending on the infection.
- The therapeutic effect is maintained between doses (hence twice‑daily application); each dose’s local effect typically lasts around 12 hours, while the full treatment course may be up to 2–4 weeks depending on the condition.
- There is no specific systemic interaction with alcohol, so moderate drinking does not affect topical efficacy; however avoid applying alcohol‑based products to treated skin (they may sting) and consult your clinician about alcohol if pregnant, breastfeeding or medically unwell.
- The most common side effect is burning, stinging or irritation at the application site.
- Would you like to try lotrisone without a prescription?


Basic Lotrisone Information
- INN (International Nonproprietary Name): Clotrimazole and Betamethasone Dipropionate.
- Brand Names Available In Australia: Not specified; generics marketed as "Clotrimazole and Betamethasone Dipropionate Cream" may be offered, while Lotrisone and Lotriderm are branded products in North America and Canada respectively.
- ATC Code: D01AC20.
- Forms & Dosages: Cream 1% clotrimazole / 0.05% betamethasone dipropionate (0.643 mg betamethasone dipropionate per g), typically in 15 g and 30 g tubes; lotion variants are country dependent.
- Manufacturers In Australia: Not specified; international manufacturers include Merck/Schering‑Plough, Teva, Pharmascience, Organon, Cipla and others.
- Registration Status In Australia: Not specified; confirm ARTG/TGA entries before prescribing or dispensing.
- OTC / Rx Classification: Prescription only (Rx) in major markets; check local TGA/ARTG for Australian scheduling.
Key Findings From Recent Trials
Which recent studies change how pharmacists advise patients about antifungal‑steroid creams?
Recent research from 2022–2025 prioritised efficacy of antifungal–steroid combinations for rapid symptom relief and the harms associated with prolonged steroid exposure.
Systematic reviews and pharmacoepidemiology reports showed that combining an imidazole such as clotrimazole with a potent topical corticosteroid like betamethasone dipropionate produced faster reduction in itch and inflammation than antifungal alone.
Those faster symptomatic gains did not consistently translate into superior long‑term mycological cures across all studies.
Australian primary‑care prescribing audits and real‑world pharmacy data found these combinations are often used by patients seeking quick symptomatic relief, especially through urban telehealth pathways.
Main outcomes across the trials were faster symptomatic improvement and similar short‑term cure rates in some cohorts, with inconsistent benefit for tinea pedis clearance.
Regulatory vigilance highlighted the balance between efficacy and steroid risk, prompting stronger pharmacist counselling in Australia around appropriate duration and indication.
Main Outcomes
What did the trials report about cure rates and symptom control?
Across the reviewed studies, combination therapy produced faster relief of pruritus and inflammation compared with clotrimazole alone in many short‑term assessments.
In several cohorts, short‑term mycological cure rates were similar between combo and antifungal monotherapy.
Tinea pedis outcomes were inconsistent, with some studies showing no clear advantage for the combination over monotherapy.
Clinicians interpreting the data should weigh immediate symptom relief against uncertain long‑term benefits for fungal eradication.
Safety Observations (TGA Reports)
Are there safety signals Australian pharmacists need to watch for?
TGA and international adverse‑event databases from 2022–2025 flagged risks such as skin atrophy, tachyphylaxis and rare hypothalamic–pituitary–adrenal (HPA) axis suppression after extensive or prolonged use.
These findings have pushed Australian pharmacists to place stronger emphasis on counselling about duration limits and monitoring for steroid effects.
Documenting advice and flagging repeat prescriptions for specialist review are practical safety steps in community practice.
Clinical Mechanism Of Action
How does Lotrisone work in plain terms?
Lotrisone combines clotrimazole, an antifungal, with betamethasone dipropionate, a corticosteroid, to treat fungal skin infections with inflammation.
Clotrimazole disrupts fungal cell membranes and stops fungal growth, while betamethasone reduces redness, swelling and itch quickly.
Scientific Breakdown
What are the pharmacological actions behind each component?
Clotrimazole is an imidazole (ATC D01AC20) that inhibits ergosterol synthesis by blocking lanosterol 14α‑demethylase, producing fungistatic or fungicidal effects depending on organism and concentration.
Betamethasone dipropionate is a potent topical corticosteroid that binds glucocorticoid receptors and modulates gene transcription to reduce cytokine release and vasodilation.
The antifungal and steroid cream combination delivers both mechanisms locally to control both the fungus and the inflammatory response.
Pharmacokinetics (Topical)
How much of either drug is absorbed from the skin?
Systemic absorption is minimal with limited use on intact skin, but absorption increases with occlusion, damaged or atrophic skin, large treated surface area, in paediatric patients and with prolonged therapy.
The typical cream strength is 1% clotrimazole with 0.05% betamethasone dipropionate (0.643 mg/g), and product information notes limited systemic uptake under normal conditions.
Scope Of Approved & Off‑Label Use
Where is this combination approved and how is it used off‑label in Australia?
Lotrisone and similar clotrimazole and betamethasone dipropionate combinations are FDA and Health Canada prescription products in major markets, and generics are widely offered in international markets.
In Australia, clinicians must verify ARTG/TGA listings and PBS inclusion because specific branded registration and subsidy status are not specified in the sourced data.
Notable Off‑Label Trends In Australian Practice
When do Australian prescribers use the combination beyond the label?
Off‑label use is seen for mixed inflammatory fungal presentations or when rapid symptom control is prioritised, for example in severe pruritus with tinea corporis or cruris.
Australian GPs and pharmacists increasingly favour short, targeted courses to limit steroid exposure rather than prolonged treatment.
The combination is not recommended for diaper dermatitis, rosacea, perioral dermatitis, mucosal areas or children under 17 except under specialist advice.
Dosage Strategy
What is the usual dosing regimen patients ask about at the pharmacy?
Product guidance indicates adults and children 17 years and older should apply a thin film twice daily, typically morning and evening, with a maximum of 45 g per week.
Common tube sizes are 15 g and 30 g, with cream strength of 1% clotrimazole and 0.05% betamethasone dipropionate.
Condition‑Specific Dosing (PBS Recommendations)
How long should each condition be treated for?
Tinea corporis and tinea cruris: apply twice daily for up to two weeks.
Tinea pedis: apply twice daily for up to four weeks.
Australian prescribers commonly document indication, limit duration to the shortest effective course, and advise clinical review at the end of therapy.
For extensive or interdigital infections, many clinicians prefer antifungal monotherapy such as topical terbinafine or clotrimazole alone to avoid steroid masking of disease.
Special Populations
Are there groups who need different advice?
Children under 17: safety and efficacy are not established and use should be avoided unless essential and under specialist supervision.
Elderly patients: no routine dose adjustments but monitor for increased risk of skin atrophy and potential systemic effects when treating fragile skin.
Safety Protocols
Which patients must not use this cream?
Absolute contraindications include hypersensitivity to clotrimazole, betamethasone dipropionate or excipients, and use on eyes, mouth or intravaginally.
Relative contraindications include children under 17, pregnancy and lactation unless necessary, extensive or occluded application, and use on infected or atrophic skin.
Adverse Effects (Post‑Market Pharmacovigilance)
What adverse events should pharmacists warn patients about?
Common local effects include burning, stinging, redness, dryness, pruritus, folliculitis, acneiform eruptions and maceration.
Prolonged use raises the risk of skin atrophy and striae, and rare systemic effects such as HPA‑axis suppression have been recorded with extensive or long‑term application.
Australian pharmacists are advised to document counselling and to flag repeated scripts for review by a GP or dermatologist.
Interaction Mapping
Do any foods affect topical Lotrisone?
Topical clotrimazole and betamethasone dipropionate have no clinically significant food interactions, and alcohol or coffee do not alter topical action.
Drug Combinations To Avoid (TGA Safety Alerts)
Which drug combinations increase risk?
Avoid using other potent topical steroids concurrently on separate body sites to reduce cumulative steroid exposure.
Avoid unnecessary systemic corticosteroids when topical steroids are already in use, and take care when patients are on systemic immunosuppressants because of increased infection risk.
Systemic interactions from topical clotrimazole are minimal, but caution if combining with hepatically metabolised systemic azoles or multiple interacting medicines in elderly multimorbid patients.
Patient Experience Analysis
What do Australian patients say about combination antifungal‑steroid creams?
Survey data show high patient satisfaction for rapid itch relief after starting a combination antifungal and steroid cream.
However, many patients misunderstand steroid risks and may request repeats without appreciating duration limits.
Forum And Pharmacy Trends
How do online reports and pharmacists' experience compare?
Online forums contain reports of quick symptomatic relief and some anecdotes of recurrence after short courses or skin thinning after prolonged use of combination creams.
Community pharmacists at major chains report counselling as a routine activity, verifying the indication, advising on duration limits and suggesting monotherapy where appropriate.
Price sensitivity and PBS expectations drive many patients to seek generics or pharmacist‑recommended alternatives.
Distribution & Pricing Landscape
Where do patients typically get clotrimazole and betamethasone dipropionate creams in Australia?
Lotrisone as a branded product is primarily North American, while Australian supply tends to be generics labelled "clotrimazole and betamethasone dipropionate cream" where available.
Major national pharmacy chains dispense prescription creams when presented with a valid script and commonly advise on alternatives and sourcing.
Telehealth and e‑prescriptions have increased access, allowing online pharmacies to fulfil authorised PBS or private scripts and ship to rural patients.
In our online pharmacy, lotrisone is available without a prescription, with discreet delivery to Australia in 5-14 days.
When the combination is not PBS‑listed, out‑of‑pocket cost varies by brand and outlet, and pharmacists frequently suggest generics or OTC clotrimazole if clinically appropriate.
Alternative Options
Which treatments should pharmacists discuss as alternatives to a combination cream?
Options include clotrimazole monotherapy, topical or systemic terbinafine, and other antifungal steroid combinations available overseas such as Travocort.
Clotrimazole monotherapy is effective for many dermatophyte infections and is available OTC in many markets as Canesten or clotrimazole cream.
Topical terbinafine or oral terbinafine is effective for dermatophyte infections, with systemic therapy reserved for extensive or refractory cases.
Pros And Cons Checklist
How should patients weigh benefits and risks?
Combination products give rapid itch and inflammation control and are convenient as a single product.
Drawbacks include potential steroid masking of infection, skin atrophy, paediatric risks and likely lack of PBS subsidy in Australia.
A stepwise approach—start monotherapy for uncomplicated tinea and reserve combination therapy for inflamed cases—balances cure and safety.
Regulatory Status
How does the TGA view topical antifungal‑steroid combinations?
The Therapeutic Goods Administration requires ARTG listing for topical combinations and expects safety and manufacturing standards consistent with international regulators.
Product information shows Lotrisone is FDA and Health Canada approved as a prescription product, but ARTG presence and labelling can differ for local generics, so prescribers should confirm registration details.
PBS Subsidy Process
Why are many combinations not PBS‑listed in Australia?
PBS listing requires demonstrated clinical and cost effectiveness compared to alternatives, and many antifungal‑steroid creams lack evidence for superior long‑term cost‑effectiveness versus antifungal monotherapy.
Clinicians should check the PBS schedule and any authority requirements and consider concessional pathways for eligible patients where appropriate.
Consolidated FAQ
Q1: Can I buy Lotrisone over the counter in Australia?
No, combination products are prescription only in major markets; pharmacists can recommend OTC clotrimazole for mild fungal infections.
Q2: How long can I use it safely?
Follow prescriber guidance: typically up to two weeks for tinea corporis/cruris and up to four weeks for tinea pedis, with a maximum of 45 g per week.
Q3: Is it safe in pregnancy or children?
Avoid in children under 17 unless essential; pregnancy and lactation use only if benefits outweigh risks and after discussion with the prescriber.
Q4: What if symptoms don’t improve?
If there is no improvement after the prescribed course, stop and re‑assess, consider swab or culture and GP or dermatology review for possible switch to monotherapy or systemic treatment.
Visual Guide
What infographics help patients understand treatment and access?
Create a pathway map showing patient → GP/telehealth → prescription → community pharmacy or online fulfilment, and a cost comparison between PBS‑subsidised antifungal monotherapy and private combination cream.
Show a dosage timeline graphic indicating two weeks for tinea corporis/cruris versus four weeks for tinea pedis and a 45 g/week cap.
Include practical images for correct application (thin film, avoid mucosa), signs to stop (worsening erythema, thinning skin) and storage icons (store 20–25°C).
For rural audiences highlight telehealth and e‑script pickup options to bridge access gaps.
Storage & Transport
How should patients store their cream in typical Australian homes?
Store creams at 20–25°C and avoid freezing or direct sunlight, keeping them tightly closed and out of reach of children.
Advise patients in hot climates to keep tubes in a cool, shaded cupboard as domestic temperatures can exceed recommended ranges during summer.
Cold‑Chain Logistics For Pharmacies
Do topical creams need cold chain handling?
Topical creams do not require strict cold chain but should be held in ambient controlled pharmacy conditions in line with TGA storage guidance.
Online fulfilment should use packaging that prevents heat exposure during transit, especially for remote deliveries in summer.
Pharmacy Handling Tips
What practical steps help community pharmacies maintain product quality?
Rotate stock, inspect tubes for integrity, document expiry dates and counsel patients on safe storage after dispensing.
For remote deliveries, note special handling instructions and advise patients on storing products in caravans or remote homesteads.
Guidelines For Proper Use
How should pharmacists structure counselling for these creams?
Use a stewardship‑focused, evidence‑based counselling approach that confirms the diagnosis, explains benefits and steroid risks, sets a firm duration limit and documents the advice.
Advise application as a thin film twice daily, avoiding mucosal areas, and warn about signs of steroid overuse such as thinning skin or new stretch marks.
Encourage follow‑up with the prescribing GP or a dermatologist if symptoms persist or recur, and escalate to culture and referral for repeated presentations.
National Health Authority Recommendations
Which national guidance should inform counselling?
Align local advice with TGA safety communications and dermatology society guidance by favouring the shortest effective course, avoiding use in children under 17 where possible, and considering antifungal monotherapy for uncomplicated cases.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
Final Practical Notes
When dispensing, always confirm the ARTG/TGA entry and PBS status before advising on subsidy or substitution.
Document your counselling about duration limits, application technique and storage, and flag repeat presentations for clinical review.
Advise patients to stop treatment and seek GP review if the rash worsens, if they develop signs of skin thinning, or if there is no improvement after the recommended course.
For many uncomplicated fungal infections, recommend clotrimazole cream or terbinafine options first and reserve combination antifungal steroid creams for clearly inflamed presentations where short‑term relief is required.