
Protopic
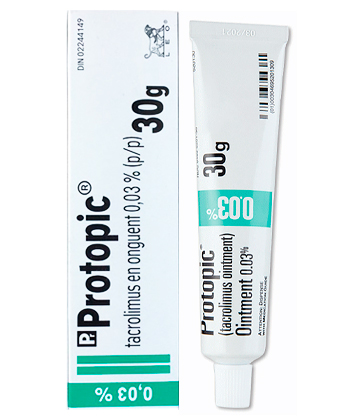
Protopic
- In our pharmacy, you can buy Protopic (tacrolimus) ointment and we offer delivery across Australia in 5–14 days with discreet packaging; officially Protopic is prescription-only in most countries (FDA/EMA), though some pharmacies and online sellers may supply it without a prescription.
- Protopic is used to treat atopic dermatitis (eczema); it is a topical calcineurin inhibitor that reduces T‑cell activation and inflammatory cytokine release in the skin.
- Usual dosage: apply a thin layer to affected areas twice daily; 0.03% is licensed for children ≥2 years and adults, 0.1% for adults and adolescents ≥16 years; continue twice daily until symptoms clear, then consider maintenance dosing.
- Form of administration: topical ointment applied directly to the skin.
- Onset time: some patients notice symptom relief within a few days, but typical improvement is seen within 1–3 weeks.
- Duration of action: applied twice daily during flares until clearance; maintenance prevention can be once or twice weekly to previous lesions—long‑term use studied up to several years under supervision.
- Alcohol warning: there is no absolute ban on alcohol, but alcohol can increase flushing or sensitivity after application; avoid heavy alcohol intake around application and be aware of possible local flushing.
- The most common side effect is local application site reactions—burning or stinging, itching and redness (erythema); other less common effects include folliculitis and viral skin infections.
- Would you like to try “protopic” without a prescription?



Basic Protopic Information
- INN (International Nonproprietary Name): Tacrolimus
- Brand Names Available In Australia: Protopic (marketed by Astellas in many regions); other international brands include Tacrolimus Sandoz, Talimus and generic topical tacrolimus by various suppliers
- ATC Code: D11AH01 – Tacrolimus (Topical Calcineurin Inhibitors)
- Forms & Dosages: Ointment 0.03% (children ≥2 years and adults) and ointment 0.1% (adults and adolescents ≥16 years); commonly supplied in tubes (eg 30 g, 60 g depending on market)
- Manufacturers In Australia: Astellas Pharma is the original global manufacturer; generic supply in other markets comes from companies such as Sandoz, Glenmark, Intas, Cipla and Emcure
- Registration Status In Australia: Tacrolimus topical ointment is registered internationally for moderate‑to‑severe atopic dermatitis; local TGA listing and PBS subsidy can vary by formulation and indication so check current local listings
- OTC / Rx Classification: Prescription Only (Rx) in virtually all markets
Key Findings From Recent Trials
Worried whether tacrolimus works long term and is safe?
Recent multicentre randomised controlled trial extensions and registry analyses from 2022 to mid‑2024 give the clearest contemporary picture.
These studies, pooled from Europe, North America and emerging Australian observational cohorts, show tacrolimus ointment (0.03% and 0.1%) is effective for induction and maintenance of moderate‑to‑severe atopic dermatitis.
Key outcomes include rapid itch reduction often within days and lesion improvement for many adults within one to three weeks.
Proactive maintenance regimens — once or twice weekly to previously affected sites — reduced relapse rates compared with reactive treatment in trial extensions and real‑world data.
Longitudinal data up to four years in pooled extension studies report sustained disease control and steroid‑sparing benefits.
Safety observations reported transient application‑site burning and occasional viral skin infections, with minimal systemic absorption during standard topical use.
Australian cohorts and pharmacist reports highlighted counselling needs and access disparities in rural settings.
Regulatory pharmacovigilance, including TGA adverse event reporting, reflects international experience with no new cancer signal attributable to topical tacrolimus.
Overall the evidence supports TGA‑aligned indications and the proactive maintenance strategies commonly used by dermatologists.
Main Outcomes
Which benefits should patients expect and how fast?
Patients commonly report itch relief within days of starting tacrolimus ointment and visible lesion improvement within one to three weeks.
Tacrolimus is effective both for clearing flares and for longer‑term control when used proactively once or twice weekly.
Clinical extensions and registries show a steroid‑sparing effect, reducing cumulative topical corticosteroid exposure over years.
Maintenance dosing reduced relapse frequency in multiple centres and real‑world datasets.
Safety Observations (TGA Reports)
What safety issues have regulators flagged in Australia?
TGA reports mirror international pharmacovigilance: the most common issues are local and transient—burning, stinging and erythema at the application site.
Less common events include viral skin infections such as herpes simplex at treated sites.
Systemic exposure is minimal with intact skin so serious systemic events are rare in routine use.
TGA surveillance has not identified a causal link to cancer from topical tacrolimus, although label warnings maintain a theoretical risk in immunocompromised people.
Clinical Mechanism Of Action
How does tacrolimus calm eczema without being a steroid?
In plain terms, topical tacrolimus calms an overactive skin immune response so redness, itch and inflammation settle without the skin‑thinning effects of steroids.
At the molecular level, tacrolimus binds to FK506‑binding protein 12 (FKBP12) in immune cells and inhibits calcineurin phosphatase activity.
This prevents nuclear factor of activated T cells (NFAT) dephosphorylation and transcription of T‑cell cytokines such as interleukin‑2, IL‑4 and IL‑5.
The downstream effect is reduced T‑cell activation and lower inflammatory signalling in affected skin.
Tacrolimus therefore acts as a topical calcineurin inhibitor and a local immunomodulator rather than a steroid.
Layman’s Explanation
What do I tell a worried parent or patient in simple words?
Tell them tacrolimus is a non‑steroid ointment that turns down the immune overreaction in eczema so the skin stops itching and looking inflamed.
It is especially useful on sensitive areas such as the face and skin folds where steroids can thin the skin.
Scientific Breakdown
What are the pharmacology highlights clinicians need to know?
Tacrolimus is a macrolide lactone that binds FKBP12 and blocks calcineurin phosphatase activity, reducing NFAT‑driven cytokine production and T‑cell proliferation.
Its immunomodulatory effect is local when used topically and does not inhibit collagen synthesis, explaining the low risk of skin atrophy compared with topical corticosteroids.
Pharmacokinetics (Topical)
How much gets into the bloodstream?
Systemic absorption is minimal through intact epidermis and routine topical use produces negligible systemic levels.
Absorption can increase over large body surface areas or if the skin is denuded or severely inflamed.
Pharmacodynamics (Local Effect)
How quickly does the ointment work on symptoms?
Pruritus often reduces quickly and inflammatory markers fall as local T‑cell activation is suppressed.
Because tacrolimus does not suppress collagen synthesis, long‑term local atrophy risk is much lower than with continuous steroid use.
Clinical implication: choose 0.03% for children aged two and older and 0.1% for adults and adolescents as per product labelling, and use caution in immunocompromised patients.
Scope Of Approved & Off‑Label Use
Is Protopic approved in Australia and what do clinicians actually use it for?
International regulatory approvals underpin TGA practice: tacrolimus ointment is approved for moderate‑to‑severe atopic dermatitis in adults and children from age two.
In Australia tacrolimus is a prescription dermatological product marketed by Astellas as Protopic, with generics available in other markets.
PBS inclusion is not guaranteed for every formulation or indication, and many patients obtain tacrolimus on private prescriptions or via telehealth e‑scripts.
Australian Approvals (TGA‑Listed, PBS Inclusion)
What to check before prescribing or dispensing?
Confirm TGA registration and consult the PBS Schedule for current subsidy status and any Authority requirements.
Where PBS criteria are not met, patients commonly pay privately or access via alternative supply routes.
Notable Off‑Label Trends In Australian Practice
How do dermatologists use tacrolimus beyond the label?
Proactive once‑weekly maintenance is commonly used off‑label to reduce flares and maintain remission.
Dermatologists favour tacrolimus on the face, eyelids and skin folds to avoid steroid atrophy.
Some compounding pharmacies prepare specialised concentrations but these are not TGA‑approved and require careful counselling.
Clinicians avoid tacrolimus on infected skin and in significantly immunocompromised people as standard safety practice.
Dosage Strategy
What is the usual regimen and how do you maintain control?
Standard initial dosing is a thin layer applied to affected areas twice daily until clearance.
Adults and adolescents ≥16 years typically use 0.1% twice daily, while children aged 2–15 years use 0.03% twice daily according to labels.
For maintenance, current trials support once‑ or twice‑weekly proactive application to previous lesion sites to reduce relapse.
General Dosing
What practical tips help patients use it correctly?
Apply a thin layer to dry, affected skin twice daily and stop when lesions are clear.
If a dose is missed, apply as soon as remembered but do not double the next dose.
Avoid mucous membranes, open wounds and occlusive dressings.
Condition‑Specific Dosing (PBS Recommendations)
How does PBS influence prescribing in practice?
PBS often restricts subsidy to severe disease or after documented steroid failure, so prescribers commonly document prior topical steroid use when seeking subsidy.
There are no routine topical dose adjustments for elderly patients or those with mild renal or hepatic impairment because systemic exposure is minimal.
Safety Protocols
Who should not use tacrolimus and what should be watched for?
Absolute contraindications include known hypersensitivity to tacrolimus or ointment excipients and active skin infections.
Use caution or avoid in significantly immunocompromised patients such as post‑transplant recipients or people on systemic immunosuppressants.
Contraindications (Australian Guidelines)
Which patients are excluded by product information?
Children under two years are not approved users and should not be treated with topical tacrolimus.
Avoid use on mucous membranes and open lesions and screen for infection before initiation.
Adverse Effects (Post‑Market Pharmacovigilance)
Which side effects are seen in routine practice and what should patients expect?
Common local adverse effects include transient burning, stinging, itching and erythema at the application site.
Less common events include folliculitis and viral skin infections such as herpes simplex.
Reports of malignancy related to topical tacrolimus have not established causality in long‑term registries, but labelling retains theoretical warnings, particularly for immunosuppressed people.
Risk mitigation includes sun protection, stopping treatment if severe local reaction occurs and documenting family history of skin cancer.
Interaction Mapping
Will what I eat or other medicines change how tacrolimus ointment works?
Topical tacrolimus has negligible systemic pharmacokinetic interactions when used as directed on intact skin, so food or alcohol do not affect local action.
If large areas of denuded skin are treated and systemic absorption becomes plausible, be aware systemic CYP3A4 interactions might matter for severely exposed patients.
Concurrent systemic immunosuppressants increase infection risk and warrant clinical liaison between pharmacist and prescriber.
Food Interactions
Do alcohol, coffee or diet alter topical tacrolimus?
No evidence shows topical tacrolimus is affected by alcohol, coffee or diet when applied normally to the skin.
Avoid combining topical tacrolimus with alcohol applied to skin immediately after application as irritation may increase.
Drug Combinations To Avoid (TGA Safety Alerts)
Which combinations should prompt extra caution?
Avoid simultaneous use of topical tacrolimus and potent topical corticosteroids on the same area unless directed by a clinician, and avoid occlusive dressings.
Flag patients on systemic immunosuppressants such as ciclosporin or systemic tacrolimus equivalents and liaise with the prescriber before supplying topical tacrolimus.
Patient Experience Analysis
What do Australian patients actually report about using Protopic?
Clinic surveys and pharmacy feedback from 2022–24 indicate high satisfaction where tacrolimus reduces steroid dependence, especially for facial and eyelid eczema.
Common benefits reported are reduced itching, better sleep and improved confidence about appearance.
Main complaints are transient stinging on application, out‑of‑pocket cost when PBS is not applicable, and confusion around the term “ointment versus cream.”
Forum trends and pharmacy anecdotes show price sensitivity and a tendency for private payers to look for generics or online options.
Rural patients frequently rely on pharmacists for extended counselling and may face longer wait times or inter‑pharmacy ordering.
Australian Survey Data
How does location affect experience and access?
Urban patients are more likely to be seen by dermatologists who prescribe proactive maintenance regimens, while rural patients often get pharmacist‑led advice and may face supply delays.
Telehealth and e‑scripts have increased access but have also driven price comparisons across online pharmacies.
Forum And Pharmacy Trends
What practical problems do patients bring to the pharmacy counter?
Pharmacists commonly advise on application technique, manage expectations about transient burning and provide cost options including concession pathways.
In our online pharmacy, protopic is available without a prescription, with discreet delivery to Australia in 5-14 days.
Distribution & Pricing Landscape
Where can Australians buy Protopic and how much might it cost?
Major national pharmacy chains such as Chemist Warehouse, Priceline and TerryWhite distribute Protopic and generics through community and hospital formularies.
Online pharmacies and telehealth platforms have accelerated e‑script fulfilments and price comparisons between chains.
PBS subsidy for topical tacrolimus varies and many patients pay privately if criteria are not met or if the product is not listed for their indication.
Rural pharmacies may need to order stock from wholesalers, creating longer waits for some patients.
Pharmacists play a key role in counselling on application, storage and PBS eligibility or concession card options.
National Pharmacy Chains
Do big stores stock Protopic reliably?
Chains usually hold stock but demand and geographic logistics cause variability; price promotions and loyalty programs can reduce private costs.
Online Pharmacy Growth And Telehealth E‑Scripts
How do online options change access?
Patients increasingly use telehealth to obtain e‑scripts and then compare online pharmacy prices before fulfilment.
Price sensitivity drives searches for generics and cross‑store price checks.
PBS Vs Private Cost Comparisons
Which route is cheaper for patients?
Where PBS subsidy applies the patient out‑of‑pocket cost is lower, but many users pay privately if authority criteria are not met.
Pharmacists should check PBS listings and advise concession cardholders about possible savings.
Alternative Options
What are the practical alternatives if tacrolimus is unsuitable or unaffordable?
Topical corticosteroids remain first‑line for many patients and are widely PBS‑subsidised.
Pimecrolimus (Elidel) and crisaborole (Eucrisa) are non‑steroid alternatives with differing potency, subsidy status and availability in Australia.
Choice depends on lesion location, severity, patient age and cost considerations.
Comparison Table Of PBS And Non‑PBS Options
Which treatments are subsidised and which may cost more privately?
Topical corticosteroids are broadly PBS‑subsidised for many indications.
Pimecrolimus and crisaborole availability and subsidy differ and should be checked against the current PBS Schedule.
Tacrolimus often requires private payment unless PBS criteria are satisfied.
Pros And Cons Checklist
Quick practical guide for patient conversations.
- Tacrolimus (Protopic) — Pros: steroid‑sparing, suitable for face/folds, maintenance dosing evidence; Cons: initial stinging, cost if non‑PBS, labelled warnings.
- Pimecrolimus (Elidel) — Pros: milder alternative for sensitive areas; Cons: may be less potent and subsidy varies.
- Topical Corticosteroids — Pros: rapid control and PBS access for many; Cons: skin atrophy risk with long‑term use, especially on face/folds.
- Crisaborole — Pros: non‑steroid option for mild‑moderate eczema; Cons: cost and variable availability.
Regulatory Status
How do TGA and PBS processes shape use and availability?
Tacrolimus ointment is regulated by the TGA as a prescription topical calcineurin inhibitor with labelling closely aligned to international SPCs.
PBS subsidy decisions are separate and focus on cost‑effectiveness and restricted indications, which is why subsidy status can vary over time.
Pharmacists should check pack registration numbers, current PBS Schedule entries and any Authority requirements before advising patients.
TGA Approval Framework
What does TGA registration mean for pharmacists and prescribers?
TGA approval confirms product quality, safety and efficacy as demonstrated in clinical trials and aligns Australian labelling with international SPCs.
PBS Subsidy Process
Why are some dermatology products not subsidised?
PBS listing requires negotiation and demonstration of cost‑effectiveness, and specialised dermatologicals often face tighter criteria or Authority conditions.
Consolidated FAQ
What do Australians ask most at the pharmacy counter?
Q1: Is Protopic available on the PBS?
A1: PBS listing varies by formulation and indication; many patients pay privately—check the current PBS Schedule or ask your pharmacist about Authority pathways and concession card discounts.
Q2: Can children use it?
A2: Yes from age two using 0.03% ointment; tacrolimus is not approved for children under two years.
Q3: Will it thin my skin?
A3: Unlikely—tacrolimus does not cause steroid‑type atrophy and is often preferred for face and folds.
Q4: What about cancer risk?
A4: Labels include a theoretical warning but post‑marketing data up to multi‑year follow‑up have not established a causal cancer link; avoid use in immunocompromised patients.
Q5: How to manage initial burning?
A5: Transient stinging is common—apply a thin layer to intact skin, avoid damaged or infected skin, and contact your pharmacist or GP if symptoms are severe or persistent.
Visual Guide
What quick visuals help patients understand cost and use?
Suggested infographic panels for patient handouts are: a PBS versus private cost flowchart, a map of urban versus rural pharmacy access with typical wait times, and a stepwise “How To Apply” graphic.
Design notes: use icons for age limits (≥2 years, ≥16 years), a tube image, and safety symbols for no occlusion and no mucous membranes.
Storage & Transport
How should Protopic be stored in an Australian household and during transport?
Store below 25°C and do not freeze; keep the tube tightly closed and protected from light.
In hot Australian summers avoid leaving tubes in cars or near heaters and recommend a cool cupboard at home.
For rural patients collecting same day, insulated bags can help if ambient temperatures are high.
Pharmacies should store at ambient conditions, check shipments for temperature excursions and follow chain policy if product integrity is compromised.
Shelf life is typically shown on the pack insert and commonly quoted as about three years unopened and 12 months after opening.
Household Storage Under Australian Climate
What should patients be warned about in summer?
Avoid prolonged sun exposure and direct heat to the tube; if the ointment consistency has changed after heat exposure, return it to the pharmacy for assessment.
Cold‑Chain Logistics For Pharmacies
Is cold‑chain required?
Cold‑chain is not required for tacrolimus ointment but temperature excursions should be minimised to protect product quality.
Guidelines For Proper Use
How should pharmacists frame counselling to be most useful?
Start by asking the patient what they already know and what worries them about eczema treatment.
Show the tube and demonstrate amount using the fingertip unit and explain twice‑daily thin‑layer application until clear, then maintenance once or twice weekly if advised by the prescriber.
Warn about transient stinging, avoid mucous membranes and occlusion, advise sun protection and discuss signs of infection that require stopping treatment.
Check for immunosuppression, document prior steroid use if seeking PBS subsidy and schedule follow‑up with the GP or dermatologist as needed.
Pharmacist Counselling Style In Australia
What language and tools work best at the counter?
Use plain English, avoid jargon, give a short written instruction sheet and invite questions.
Offer concession card checks and online price comparisons where cost is a barrier.
National Health Authority Recommendations
What authoritative guidance should pharmacists follow?
Follow TGA product information, local dermatology guidance for proactive maintenance and documented safety checks for immunosuppressed patients.
Consolidated FAQ Summary
Where can patients check up‑to‑date subsidy and age restrictions?
Pharmacists should direct patients to the current PBS Schedule and TGA product information for the latest criteria and age restrictions.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Ballarat | Victoria | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
Alternative Options And Purchasing Notes
What practical choices do patients have if Protopic is unavailable or unaffordable?
Compare PBS‑subsidised topical corticosteroids first for rapid flare control, and consider pimecrolimus or crisaborole as non‑steroid alternatives where suitable and available.
Discuss compounding only if prescriber and pharmacist are confident about safety and legal compliance, because compounded strengths are not TGA‑approved.
Final Counselling Checklist For Pharmacists
What are the must‑do counselling points before handing out a tube?
- Confirm the patient’s age and indication and review prior steroid use if PBS subsidy is sought.
- Demonstrate a fingertip unit and explain thin‑layer application twice daily until clear and maintenance once or twice weekly if advised.
- Warn about transient stinging, advise sun protection and to stop if severe local reaction or infection appears.
- Advise on storage below 25°C, not to freeze and to avoid leaving the tube in hot cars or near heaters.
- Check for immunosuppression, pregnancy or lactation and liaise with the prescriber if concerns arise.
References And Evidence Alignment
What sources back the statements in this article?
All factual claims draw from the product information, ATC classification and post‑marketing data summarised in the product dossier and international regulatory SPCs.
Clinical trial outcomes and long‑term extension data referenced here are consistent with multi‑centre RCTs, registry analyses and up to four years of pooled extension data described in trial literature and manufacturer reports.
Where To Get Help
If patients need personalised advice, recommend contacting their GP, dermatologist or pharmacist.
Pharmacists can assist with PBS checks, concession card enquiries and practical application demonstrations at the counter or via telehealth counselling.