
Rebetol
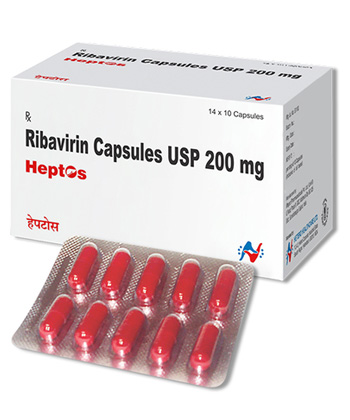
Rebetol
- Rebetol (ribavirin) is a prescription-only medicine in Australia and most other countries and should be obtained from a pharmacy with a valid prescription; it is not legally available over the counter and obtaining it without a prescription is unsafe and not recommended.
- Rebetol is used to treat chronic hepatitis C in combination with interferon or peginterferon; ribavirin is a nucleoside analogue (a guanosine analogue) antiviral that interferes with viral RNA synthesis and increases viral mutagenesis, reducing viral replication.
- Usual dosage: adults are dosed by weight — <75 kg: 1,000 mg/day (typically 400 mg AM and 600 mg PM); ≥75 kg: 1,200 mg/day (600 mg twice daily). Paediatric dosing ≈15 mg/kg/day divided twice daily. Dose adjustments or avoidance are required in renal impairment and other comorbidities.
- Form of administration: oral capsules or tablets (Rebetol 200 mg capsules; tablets available as branded/generic variants), oral solution (40 mg/mL); a separate inhalation formulation (Virazole) exists for respiratory indications but not for hepatitis C.
- Onset time: antiviral activity begins soon after starting treatment, but measurable virological and clinical responses are typically seen over weeks — early responses by 4 weeks and more substantial changes by 12 weeks.
- Duration of action: ribavirin has a long terminal half‑life (accumulates in red blood cells, roughly 100–170 hours), and treatment courses are prolonged — commonly 24 weeks for genotypes 2–3 and 48 weeks for genotypes 1, 4, 5 and 6 when used with interferon/peginterferon.
- Alcohol warning: avoid alcohol during treatment — alcohol can worsen liver disease, reduce treatment effectiveness and increase toxicity.
- Most common side effec: fatigue (notably ribavirin commonly causes haemolytic anaemia as well as headache, nausea and possible mood changes).
- Would you like to try rebetol without a prescription?


Basic Rebetol Information
- INN (International Nonproprietary Name): Ribavirin.
- Brand Names Available In Australia: Ibavyr (Australia, New Zealand) — tablets 200 mg and 400 mg; Rebetol is a recognised brand internationally (capsules 200 mg, oral solution 40 mg/mL) though Rebetol branding is primarily listed in USA, UK, EU and Canada.
- ATC Code: J05AP01 — antivirals for systemic use; nucleosides and nucleotides excl. reverse transcriptase inhibitors; ribavirin.
- Forms & Dosages: Capsules/tablets 200 mg and 400 mg; oral solution 40 mg/mL; inhalation solution formulations (Virazole) exist for other indications.
- Manufacturers In Australia: Local branded supply includes Ibavyr in Australia and New Zealand; major international manufacturers include MSD (Rebetol), Roche (Copegus) and generic suppliers such as Apotex, Teva and Mylan.
- Registration Status In Australia: Ribavirin is registered internationally for use with peginterferon/interferon in chronic hepatitis C; local availability may include Ibavyr and generics — check current TGA listings and local supplier updates for exact registration details.
- OTC / Rx Classification: Prescription only (Rx).
Key Findings From Recent Trials
What do clinicians worry about when considering ribavirin today?
Major 2022–2025 Australian & Global Studies
Recent audits and cohort reviews from 2022–2025 show ribavirin use declining in step with broad uptake of direct‑acting antivirals.
Australian real‑world audits between 2022 and 2024 report ribavirin retained for selected complex cases such as retreatment and advanced liver disease.
International cohort and meta‑analytic data from 2022–2025 echo the Australian experience, noting ribavirin's selective role rather than routine use.
Main Outcomes
Across trials, adding ribavirin to some DAA regimens produced modest increases in sustained virological response for hard‑to‑treat genotypes and retreatment scenarios.
The incremental SVR benefit was most apparent in patients with cirrhosis, prior DAA failure or resistance‑associated substitutions where peginterferon‑era regimens had limited effect.
Safety Observations (TGA Reports)
TGA post‑market reports through 2023–25 flagged anaemia and teratogenic risk as leading safety concerns.
Case reports described severe haemolysis in renal impairment and emphasised intensified blood‑count monitoring when ribavirin is used.
Regulatory guidance from the TGA and international agencies recommends strict pregnancy prevention and closer haematological surveillance if ribavirin is prescribed.
Clinical Mechanism Of Action
How does ribavirin actually stop a virus from copying itself?
Layman’s Explanation
Ribavirin is an antiviral that jams the virus’s replication machinery so it makes fewer infectious copies.
It is rarely used on its own and is typically given with interferon or certain direct‑acting antivirals to boost cure rates in difficult cases of hepatitis C.
Scientific Breakdown
Ribavirin (ATC J05AP01) is a guanosine analogue converted inside cells to ribavirin triphosphate.
Its antiviral actions include lethal mutagenesis that increases viral error rates, inhibition of inosine monophosphate dehydrogenase which depletes intracellular GTP pools, and immunomodulatory effects that enhance host antiviral responses.
Oral formulations (capsules/tablets 200 mg; oral solution 40 mg/mL) are systemically absorbed and predominantly cleared by the kidneys.
Because renal excretion predominates, dosing adjustments are required when creatinine clearance falls and anaemia risk increases.
When combined with interferon or certain DAAs, ribavirin can reduce relapse rates but raises haematologic toxicity risk, explaining the need for blood‑count surveillance.
Scope Of Approved & Off‑Label Use
Who is actually authorised to prescribe ribavirin in Australia and how is it being used off‑label?
Australian Approvals (TGA‑Listed, PBS Inclusion)
Ribavirin is TGA‑registered for use in chronic hepatitis C in combination with interferon/peginterferon.
Product forms include Rebetol capsules (200 mg) and an oral solution (40 mg/mL) internationally, and Ibavyr is documented in Australia and New Zealand.
Historically, PBS listings subsidised ribavirin when paired with interferon‑based regimens, but PBS claims have fallen since DAAs became first‑line.
Pharmacists should verify current PBS listings and authority requirements before dispensing if subsidy is sought.
Notable Off‑Label Trends In Australian Practice
Specialist hepatology clinics and rural services sometimes use ribavirin off‑label with DAAs for retreatment of prior DAA failures or salvage therapy for resistant genotypes.
In resource‑limited settings, ribavirin remains paired with peginterferon where DAAs are inaccessible.
Clinicians stress strict contraception counselling and close monitoring when using off‑label combinations.
Dosage Strategy
What dose will I be given and how is it adjusted?
General Dosing
Adult weight‑based dosing is standard: body weight less than 75 kg — 1000 mg/day divided as 400 mg in the morning and 600 mg in the evening.
Body weight 75 kg or more — 1200 mg/day divided as 600 mg twice daily.
Available formulations include Rebetol capsules 200 mg and oral solution 40 mg/mL, and tablets/generics in 200 mg and 400 mg strengths.
Paediatric dosing is approximately 15 mg/kg/day in two divided doses taken with food.
Condition‑Specific Dosing (PBS Recommendations)
Traditional genotype‑dependent durations were 48 weeks for genotypes 1, 4, 5 and 6, and 24 weeks for genotypes 2 and 3, always combined with interferon or peginterferon in classic regimens.
When ribavirin is used adjunctively with DAAs, specialists tailor dose and duration to genotype, cirrhosis status and prior treatment history, and PBS authority approvals may specify these details.
In renal impairment avoid if creatinine clearance is less than 50 mL/min or halve the dose and monitor closely.
Ribavirin is contraindicated in pregnancy.
Safety Protocols
What are the absolute no‑gos and what monitoring protects patients?
Contraindications (Australian Guidelines)
Absolute contraindications include pregnancy due to teratogenic risk, nursing mothers, autoimmune hepatitis, severe renal impairment (CrCl <50 mL/min), haemoglobinopathies and concurrent didanosine therapy.
Relative contraindications include unstable cardiac disease, significant psychiatric disorders and a history of severe anaemia or haematologic disease.
These align with TGA labelling and major international product information.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects are fatigue, headache, nausea, rash and dose‑dependent haemolytic anaemia.
TGA reports from 2022–25 continued to record anaemia as a leading safety issue and noted occasional severe haemolysis in patients with renal impairment.
Monitoring should include baseline and regular full blood counts, renal function tests and pregnancy testing with documented contraception counselling.
Pharmacists must liaise with prescribers quickly for symptomatic anaemia or significant laboratory changes.
Interaction Mapping
Will what I eat or the other medicines I take affect ribavirin?
Food Interactions (Alcohol, Coffee, Diet In Australia)
Ribavirin absorption is adequate with food and taking doses with meals reduces gastrointestinal upset.
Alcohol does not change ribavirin pharmacokinetics but worsens liver disease outcomes and should be strongly discouraged during hepatitis C treatment.
There is no notable interaction with caffeine, but patients should be counseled on alcohol abstinence and dietary habits that support liver health.
Drug Combinations To Avoid (TGA Safety Alerts)
Didanosine is contraindicated with ribavirin.
Ribavirin combined with zidovudine or other bone‑marrow suppressive agents increases anaemia risk and should generally be avoided or used with extreme caution.
TGA safety alerts caution about co‑prescription with other agents that amplify haematologic toxicity and advise care with QT‑prolonging drugs if significant cardiac disease exists.
Pharmacists should use clinical software and medication reconciliation to flag interactions in polypharmacy patients.
Patient Experience Analysis
What do Australian patients say about taking ribavirin?
Australian Survey Data
Survey feedback from 2022–25 shows two dominant experiences: relief when therapy achieves viral suppression and frustration with side effects such as anaemia, fatigue and psychiatric symptoms.
Rural patients report extra logistical burden from frequent blood tests and travel to specialist services compared with urban peers.
Forum And Pharmacy Trends
Community pharmacy chains report fewer ribavirin dispensings than in the interferon era, but when dispensed there is strong demand for counselling on contraception and haematology monitoring.
Online forums show price sensitivity and confusion about older interferon plus ribavirin regimens versus modern DAAs, highlighting the pharmacist’s role in clear patient education.
Culturally appropriate counselling is important for Indigenous and CALD patients who may face access barriers to specialist hepatitis C services.
Distribution & Pricing Landscape
Where do patients get ribavirin in Australia and how much will it cost them?
National Pharmacy Chains
Rebetol and generics are prescription‑only and supplied via hospital pharmacies, community pharmacies including Chemist Warehouse, Priceline and TerryWhite, and specialist hepatology centres.
Stock and brand availability varies by supplier and region.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth e‑scripts are increasingly used for specialist‑initiated regimens and remote clinics often coordinate pathology and dispensing with local pharmacies.
In our online pharmacy, rebetol is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS Vs Private Cost Comparisons
Ribavirin was historically PBS‑subsidised when used with interferon, but PBS claims have declined as DAAs became the funded first‑line options.
Private out‑of‑pocket costs vary by brand and pack size, and many patients rely on PBS authority scripts to reduce expense.
Cross‑border purchasing is limited by prescription requirements and safety concerns.
Alternative Options
Do patients have better, safer choices than ribavirin?
Comparison Summary Of PBS And Non‑PBS Options
Modern DAAs such as sofosbuvir, ledipasvir/sofosbuvir and glecaprevir/pibrentasvir are oral, shorter in duration and have higher cure rates with far better tolerability than peginterferon plus ribavirin regimens.
The PBS favours DAAs for most genotypes, making those regimens both clinically and financially preferable for many Australian patients.
Pros And Cons Checklist
- Ribavirin – Pros: Can raise SVR in selected difficult or salvage cases; generic options lower drug cost.
- Ribavirin – Cons: Teratogenic, causes haemolytic anaemia, requires intensive monitoring and historically long treatment durations.
- DAAs – Pros: High SVR rates, short courses, minimal haematologic toxicity.
- DAAs – Cons: May be costly without PBS subsidy and resistance can occur in specific settings.
Individual decisions weigh genotype, prior treatment, cirrhosis status, renal function and pregnancy risk when selecting ribavirin addition versus DAA‑only regimens.
Regulatory Status
How do TGA approvals and PBS subsidy rules shape access?
TGA Approval Framework
Ribavirin is TGA‑registered as a prescription medicine for chronic hepatitis C in combination with interferon/peginterferon and labelling mandates contraindications and monitoring requirements.
TGA product information stresses pregnancy prevention, contraception counselling and regular blood monitoring consistent with international product inserts.
PBS Subsidy Process
PBS subsidy historically covered ribavirin in interferon‑based regimens; the PBS evaluates clinical need, cost‑effectiveness and negotiation outcomes when listing medicines.
Since DAAs gained PBS listing and preference, ribavirin subsidy is niche and commonly tied to specialist authority codes for salvage or specific combinations.
Pharmacists and prescribers must verify current PBS listings and authority requirements before dispensing to ensure subsidy eligibility.
Consolidated FAQ (Australian Context)
Common questions patients ask at the pharmacy counter.
- Can I get Rebetol on PBS? — Historically yes when used with interferon; check current PBS listings and specialist authority as availability varies by regimen and indication.
- Is ribavirin safe in pregnancy? — No; ribavirin is teratogenic and both women and male partners must use effective contraception during treatment and for six months afterwards.
- What monitoring is required? — Baseline and regular full blood counts, renal function checks and pregnancy testing per TGA guidance.
- Can ribavirin be used alone? — No; ineffective as monotherapy and always combined with interferon or specific DAAs.
- Can rural pharmacies dispense Rebetol? — Yes with a valid prescription; rural patients may need coordination with specialists for pathology and PBS authority scripts.
Visual Guide (Infographic Prompts For Publishers)
What should a publisher include when creating patient visuals?
Suggested infographic elements include a PBS pricing flowchart showing specialist initiation, PBS authority, dispensing subsidy versus private cost.
Also include a pharmacy distribution map showing metropolitan versus rural dispensing pathways and telehealth e‑script integration.
A safety checklist visual should highlight pregnancy testing, contraception counselling, baseline full blood count and an ongoing monitoring schedule.
Design notes: default to the INN "ribavirin", include pack images for Rebetol capsules 200 mg and oral solution 40 mg/mL and generic tablet strengths 200 mg and 400 mg, and emphasise TGA teratogenic warnings in red.
Storage & Transport
How should ribavirin be stored at home and transported by pharmacies in Australia?
Household Storage Under Australian Climate
Store capsules, tablets and oral solution at 20–25°C and protect from excessive moisture and heat, which is important during hot Australian summers.
Keep medication in original packaging, out of reach of children and away from bathroom humidity.
Discard opened oral solution as per the pack instructions.
Cold‑Chain Logistics For Pharmacies
Capsules, tablets and oral solution for Rebetol are ambient‑stable but should avoid prolonged exposure to high heat during storage and transit.
Inhalation products such as Virazole may require cold‑chain handling per the product insert.
Rural pharmacies should account for transport time to remote communities and protect packs from sun and heat during delivery, documenting storage conditions in SOPs to meet TGA good‑distribution practice.
Guidelines For Proper Use (Pharmacist‑Focused)
How should pharmacists counsel and document when dispensing ribavirin?
Pharmacist Counselling Style In Australia
Use patient‑centred, culturally respectful communication and be explicit about pregnancy risks and the contraception requirements for both partners.
Explain haemolytic anaemia risk, psychiatric symptom possibility and provide written instructions for dose splitting when required.
Advise on timing with meals to reduce gastrointestinal upset and outline the blood‑test schedule clearly.
For rural patients proactively arrange pathology and liaise with specialists to reduce travel burden.
National Health Authority Recommendations
Follow TGA labelling and local hepatology guidelines for monitoring and contraindications.
Escalate anaemia or renal decline to the prescriber immediately and withhold dosing only as instructed by the prescriber.
Ensure PBS authority compliance, document counselling and contraception confirmation, and record baseline labs in the patient file.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Ballarat | Victoria | 5–9 days |
Concluding Notes For Pharmacists And Patients
Ribavirin remains clinically relevant in Australia for selected salvage and complex hepatitis C cases despite widespread DAA use.
Key safety priorities are preventing pregnancy, close haematologic monitoring and cautious use in renal impairment.
Pharmacists should confirm PBS authority requirements before dispensing and document contraception counselling and baseline labs.
When counselling patients, be practical: explain dose splitting for 1000–1200 mg/day regimens, set up a blood‑test schedule and offer culturally safe support for remote or Indigenous patients.
Modern DAAs are the preferred, better‑tolerated option for most patients, but ribavirin remains a useful adjunct in defined scenarios.