Chloroquine
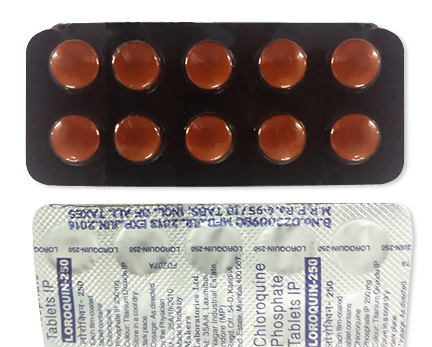
Chloroquine
- Chloroquine is generally a prescription-only medicine in nearly all countries and should be obtained from a pharmacy with a prescription; however, in some regions it may be sold over the counter or obtainable from unregulated suppliers without a receipt — purchasing or using it without medical supervision is not recommended.
- Chloroquine is used primarily as an antimalarial and antiprotozoal agent and for some rheumatic conditions (eg, rheumatoid arthritis, SLE); it works by accumulating in parasite food vacuoles to raise pH and interfere with haem detoxification, and it has immunomodulatory effects that reduce inflammation.
- Usual dosages include: acute malaria — 600 mg base initially then 300 mg base at 6, 24 and 48 hours (total 1.5 g base); adults for rheumatic disease — 250–500 mg daily; amebiasis — 600 mg base daily for 2 days then 300 mg for 2–3 weeks; paediatric dosing is weight-based (eg, 10 mg/kg then 5 mg/kg at 6, 24 and 48 hours). Dose reductions are needed in liver/kidney impairment and the elderly.
- Administration is usually oral (tablets: 100, 150, 250, 500 mg; paediatric syrup 50 mg/5 ml), with injectable formulations available only in limited settings.
- Onset of effect for acute malaria is typically within 24–48 hours (fever reduction and symptom improvement); for rheumatological conditions, clinical benefit may take several weeks to months.
- The drug has a long tissue half‑life so therapeutic concentrations persist for days to weeks after dosing; an acute malaria course is given over three days, while rheumatological therapy is maintained long term as required.
- Avoid excessive alcohol — while no specific interaction requires total abstinence, alcohol can worsen liver injury, exacerbate side effects (eg, GI upset) and increase overall risk, so alcohol should be limited.
- The most common side effect is nausea; other frequent adverse effects include headache, itching (especially in some populations), abdominal pain and blurred vision; long-term or high-dose use risks retinopathy and cardiomyopathy.
- Would you like to try chloroquine without a prescription?


Basic Chloroquine Information
- INN (International Nonproprietary Name): Chloroquine
- Brand Names Available In Australia: not specified
- ATC Code: P01BA01
- Forms & Dosages: Tablets 100 mg, 150 mg, 250 mg, 500 mg; Syrup/Solution 50 mg/5 ml (paediatric); Injectable forms 150 mg base/ml (limited use)
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only (Rx)
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Recent systematic reviews and trials from 2022 to 2025 confirmed that artemisinin‑based combination therapies remain first‑line for Plasmodium falciparum infections in most regions.
Research found chloroquine’s role remains limited to areas where P. vivax or chloroquine‑sensitive P. falciparum persist.
Post‑COVID repurposing studies up to 2024 and meta‑analyses did not show clear clinical benefit of chloroquine for SARS‑CoV‑2 disease.
Australian observational datasets emphasised rare but severe overdose presentations and highlighted triage challenges in rural emergency departments.
Pharmacogenomic work emerging in 2023–25 suggests individual metabolism and comorbidities may explain variable toxicity, though these findings are hypothesis‑generating.
Main Outcomes
Trials repeatedly documented loss of effectiveness where resistance is common and superior efficacy of ACTs for falciparum malaria.
Where susceptibility remains, such as some P. vivax pockets, chloroquine retains clinical usefulness with standard weight‑based regimens.
Safety signals during repurposing trials included increased cardiac events at higher or combined doses without clear antiviral benefit.
These outcomes support travel clinic guidance favouring ACTs for most travellers and reserved chloroquine use guided by susceptibility testing.
Safety Observations (TGA Reports)
TGA and international pharmacovigilance centres issued advisories highlighting QT prolongation, arrhythmia risk and retinal toxicity on long‑term use.
Reports triggered tightened prescribing guidance and reinforced baseline ECG and ophthalmology checks for patients at risk.
Pharmacists should note TGA communications when counselling on chloroquine tablets and chloroquine 250 mg formulations.
Clinical Mechanism Of Action
Layman’s Explanation
Chloroquine kills malaria parasites by building up in their acidic digestive vacuoles and stopping the parasite from safely disposing of toxic haem.
The resulting accumulation of toxic haem kills the Plasmodium organism in susceptible strains.
In plain terms, chloroquine acts like a net that traps waste inside the parasite until it can no longer survive.
That is why it still works for P. vivax in places without resistance but not for many modern falciparum infections.
Scientific Breakdown
Cellular Pharmacology
The drug is a weak base that concentrates in acidic lysosomes and parasite digestive vacuoles, a property called lysosomotropic accumulation.
Inside those compartments it raises pH and disrupts protease activity and haem polymerase function, preventing haem detoxification.
Immunomodulatory Effects
At lower, chronic doses used in autoimmune disease, chloroquine modulates Toll‑like receptor signalling and reduces antigen presentation.
These effects reduce inflammatory cytokine release and explain off‑label use in conditions like SLE and rheumatoid arthritis, though hydroxychloroquine is preferred by many clinicians.
Pharmacokinetics (Brief)
Chloroquine is well absorbed orally and has a large volume of distribution with slow elimination and tissue accumulation in retina and heart.
Its long half‑life explains both convenient dosing for acute malaria and the risk of accumulation with prolonged therapy.
Australian pharmacists should counsel on storage and toxicity signs for chloroquine tablets and chloroquine phosphate products.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Chloroquine historically has registered indications for malaria treatment and some rheumatological uses, though specific Australian registration details are not specified in the product data provided.
Hydroxychloroquine typically has broader PBS listings for rheumatology, while chloroquine subsidy on the PBS is less common and often indication‑specific.
Prescribers should confirm TGA Product Information and the PBS Schedule before seeking subsidy for a prescription.
Notable Off‑Label Trends In Australian Practice
Global off‑label use spiked during the COVID period but Australian clinicians largely curtailed off‑label prescribing after safety advisories.
Rural GPs sometimes face supply constraints and may use paediatric syrup formulations or adjusted dosing for children in the absence of licensed preparations.
As prescription‑only medicine, dispensing of chloroquine in Australia requires pharmacist counselling and verification against local registers.
Dosage Strategy
General Dosing
Use weight‑based acute regimens for malaria, keeping careful track of mg‑base conversions for tablet strengths.
Adult acute malaria dosing: 600 mg base initial, then 300 mg base at 6, 24 and 48 hours for a total of 1.5 g base.
Paediatric acute dosing: 10 mg/kg base initially, then 5 mg/kg base at 6, 24 and 48 hours.
Condition‑Specific Dosing (PBS Recommendations)
Rheumatic Disease (Maintenance)
Maintenance regimens commonly use 250–500 mg daily, with dose adjustments for body weight to reduce retinopathy risk.
Many Australian rheumatologists favour hydroxychloroquine over chloroquine because of tolerability and monitoring considerations.
Amebiasis
Example regimen for amebiasis: 600 mg base daily for two days followed by 300 mg for two to three weeks under supervision.
Reduce doses in hepatic or renal impairment and in elderly patients to avoid accumulation and cardiotoxicity.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include known hypersensitivity to chloroquine or related compounds and preexisting retinal or visual field changes.
A history of epilepsy is an absolute contraindication due to seizure risk with chloroquine therapy.
Relative contraindications requiring close monitoring include liver disease, renal impairment, psoriasis, porphyria, myasthenia gravis and alcoholism.
Concurrent use with QT‑prolonging agents is a relative contraindication and warrants ECG monitoring.
Adverse Effects (Post‑Market Pharmacovigilance)
Common side effects are nausea, headache and pruritus, with itching reported more often in people of African descent.
Moderate effects include blurred vision, skin rash and mood changes, while long‑term or high‑dose therapy risks retinopathy and cardiomyopathy.
Overdose is potentially life‑threatening; present with cardiac arrhythmia, convulsions or respiratory compromise and needs immediate emergency care.
Baseline and periodic ophthalmology reviews and ECGs for at‑risk patients are standard mitigation steps advised by TGA reports.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Advise moderation or avoidance of alcohol while taking chloroquine since alcohol can worsen hepatotoxicity and neurotoxicity.
Caffeine has no major direct pharmacokinetic interaction, but coffee and irritant foods may aggravate nausea associated with chloroquine tablets.
Pregnancy and breastfeeding require consultation with TGA and obstetric guidance before starting chloroquine.
Drug Combinations To Avoid (TGA Safety Alerts)
Avoid or monitor coadministration with other QT‑prolonging agents such as certain antiarrhythmics, antipsychotics and macrolide antibiotics.
Watch for CYP‑mediated interactions with strong hepatic inhibitors or inducers which may alter chloroquine levels and toxicity risk.
Drugs that lower seizure threshold are important to identify, as concomitant use with chloroquine increases seizure risk and may be contraindicated.
Pharmacists should flag interacting combinations in dispensing software and communicate concerns promptly to prescribers.
Patient Experience Analysis
Australian Survey Data
Travellers and rural patients report awareness of chloroquine’s historical role but place higher trust in ACT recommendations given by travel clinics.
Rheumatology patients often report switching to hydroxychloroquine because of perceived improved safety and less monitoring burden.
Long‑term patients emphasise the practical and financial burden of routine ophthalmology checks when on chloroquine or hydroxychloroquine therapy.
Forum And Pharmacy Trends
Online forums and pharmacy consultations show price sensitivity and frequent searches for brand names such as Aralen and Nivaquine.
Pharmacists in national chains report patient queries about PBS subsidy, paediatric syrup dosing and telehealth scripts after the pandemic.
Counselling themes to emphasise are dose accuracy, signs of toxicity such as visual changes and palpitations, and safe storage away from children.
Culturally tailored communication is important for Indigenous and rural communities who may need extra help with PBS paperwork and follow‑up.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Chloroquine is prescription‑only and stock levels are patchy compared with hydroxychloroquine, influencing which chains keep it on shelf.
Major chains such as Chemist Warehouse, Priceline and TerryWhite usually supply metropolitan demand while rural outlets may keep minimal stock.
Generic chloroquine tablets are generally cheapest when purchased privately, while PBS subsidy (if applicable) reduces out‑of‑pocket cost substantially.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth scripts and online pharmacies have increased remote prescribing and dispensing, which helps regional patients access chloroquine tablets and syrup.
In our online pharmacy, chloroquine is available without a prescription, with discreet delivery to Australia in 5-14 days.
Online orders still require verification and adherence to prescription rules for safe supply when Product Information and PBS rules apply.
PBS Vs Private Cost Comparisons
Where a PBS listing applies the patient pays a reduced co‑payment; otherwise private prices vary by brand and pack size, with generics cheapest.
Patients frequently compare cost and availability of chloroquine 250 mg vs hydroxychloroquine when discussing long‑term therapy with pharmacists.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
When chloroquine is unsuitable, hydroxychloroquine is commonly used for rheumatological conditions and is more often PBS‑listed for those indications.
For malaria, artemisinin combination therapies (ACTs) are the recommended first‑line options where chloroquine resistance exists.
Mefloquine and primaquine remain options for prophylaxis or radical cure of P. vivax respectively, chosen based on patient history and parasite sensitivity.
Pros And Cons Checklist
- Chloroquine Pros: low cost in generic form, oral syrup availability for children, effective where susceptibility persists.
- Chloroquine Cons: retinal and cardiac toxicity risk, resistance in many regions, limited PBS support.
- Hydroxychloroquine Pros: better tolerability at standard doses, stronger PBS positions for rheumatology.
- ACTs Pros: high efficacy for falciparum malaria; Cons: different adverse effect profiles and cost considerations.
Pharmacists should help prescribers and patients weigh safety, PBS criteria and monitoring logistics when switching therapy.
Regulatory Status
TGA Approval Framework
Chloroquine is classified as prescription‑only in nearly all countries and product registration requires TGA evaluation of safety, efficacy and quality.
TGA maintains adverse event reporting and updates Product Information when significant safety signals arise, for example cardiac or retinal risks.
Manufacturers and generics must comply with good manufacturing practice and registration requirements before supply in Australia.
PBS Subsidy Process
PBS listing requires demonstration of cost‑effectiveness and clinical need for the Australian population, which explains hydroxychloroquine’s stronger PBS presence for rheumatology.
When chloroquine is not PBS‑listed for an indication prescribers may use private scripts or authority mechanisms depending on the patient’s circumstances.
Pharmacists should report adverse events to the TGA and assist prescribers when subsidy or supply issues affect continuity of care.
Consolidated FAQ
Q1: Is chloroquine safe for malaria prevention in travellers to Australia?
A1: Not routinely; prevention advice depends on destination and parasite susceptibility so consult a travel clinic for current ACT recommendations.
Q2: Can I get chloroquine subsidised on the PBS?
A2: Only for specific listed indications; hydroxychloroquine is more commonly PBS‑subsidised for rheumatological disease so check the current PBS Schedule.
Q3: I’m on other heart meds—can I take chloroquine?
A3: You may need baseline ECG and review as chloroquine can prolong QT; inform your GP and pharmacist about all medicines including OTCs.
Q4: What should I do if I miss a dose or suspect overdose?
A4: If a dose is missed take it when remembered unless close to the next dose; overdose is life‑threatening and requires immediate emergency care.
Q5: How often do I need eye checks on long‑term chloroquine?
A5: Arrange a baseline ophthalmology review and periodic monitoring depending on cumulative dose and duration; many clinicians prefer hydroxychloroquine to reduce risk.
Visual Guide
Plan three infographics for clinicians, pharmacists and patients: PBS vs private cost, a pharmacy distribution map and a safety flowchart for prescribers.
Infographic one should show comparative out‑of‑pocket costs for typical pack sizes with notes on PBS eligibility.
Infographic two should map urban versus rural stock availability of chloroquine tablets and syrup and highlight telehealth script uptake.
Infographic three should be a concise safety decision tree covering baseline checks, interacting medicines, dose adjustments, counselling points and steps for suspected toxicity.
Designs should use clear icons, Australian spelling and QR codes linking to TGA Product Information and the PBS Schedule where permitted.
Storage & Transport
Household Storage Under Australian Climate
Store chloroquine at room temperature between 15–25°C, protected from light and moisture, and away from heat sources like ovens or car interiors.
Advise families to keep paediatric syrup formulations out of reach of children because accidental ingestion can be fatal.
For travel, recommend carrying medicine in original packaging and keeping authority prescriptions or telehealth scripts accessible when crossing borders.
Cold‑Chain Logistics For Pharmacies
Chloroquine does not require cold‑chain storage but pharmacies should monitor ambient dispensary temperatures, especially during Australian heatwaves.
Rural pharmacies should plan buffer stock and use reliable wholesalers for emergency restock of tablet strengths and syrup preparations.
Dispose of expired stocks through standard pharmaceutical waste streams and document stock movements to support pharmacovigilance.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Begin consultations by confirming the indication, weight for paediatrics, current medicines, allergies and cardiac history before dispensing chloroquine tablets.
Explain dosing clearly using mg‑base conversion for tablet strengths and give missed‑dose and emergency instructions in plain language.
Highlight symptoms of toxicity including visual changes, palpitations and seizures and outline immediate steps and follow‑up requirements.
Offer translated leaflets or arrange Indigenous health liaison support for culturally appropriate counselling and assist with PBS paperwork if needed.
National Health Authority Recommendations
Follow TGA Product Information, PBS criteria and local Infectious Diseases or Rheumatology guidance when advising on chloroquine, chloroquine phosphate or alternatives such as hydroxychloroquine and ACTs.
Document counselling and any adverse events reported and liaise with prescribers about dose adjustments or safer alternative options where appropriate.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |