
Rifaximin
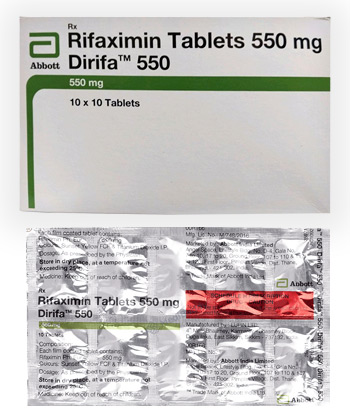
Rifaximin
- In our pharmacy, you can buy rifaximin without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Rifaximin is an oral, non‑absorbable antibiotic used to treat traveller’s diarrhoea, to reduce recurrence of hepatic encephalopathy, and for some cases of irritable bowel syndrome with diarrhoea (IBS‑D). It works locally in the gut by inhibiting bacterial RNA synthesis (binding bacterial RNA polymerase), reducing pathogenic and overgrown gut bacteria and endotoxin production.
- Usual dosage depends on indication: traveller’s diarrhoea — 200 mg three times daily for 3 days; hepatic encephalopathy prevention — 550 mg twice daily (long‑term); IBS‑D — commonly 550 mg three times daily for 14 days (courses may be repeated as advised by a clinician).
- The form of administration is oral tablets (commonly 200 mg and 550 mg strengths), taken by mouth with or without food; swallow with water.
- Symptom improvement for acute diarrhoea is often seen within 24–48 hours; relief for hepatic encephalopathy or IBS‑D may take several days.
- Duration of action is localised to the gastrointestinal tract and generally coincides with the dosing course — short courses (3 days) for traveller’s diarrhoea; ongoing dosing is required to maintain prophylaxis for hepatic encephalopathy.
- Avoid excessive alcohol, particularly if you have liver disease or hepatic encephalopathy, as alcohol can worsen liver function and encephalopathy; there is no major direct interaction but caution is advised.
- The most common side effects are gastrointestinal — nausea, abdominal pain, flatulence and sometimes headache; rare but important risks include allergic reactions and alterations in gut flora (including C. difficile overgrowth).
- Would you like to try rifaximin without a prescription?

Basic Rifaximin Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Australia: Diaformin, Diabex
- ATC Code: A10BA02
A = Alimentary Tract And Metabolism (First Level, Main Anatomical Group)
A10 = Drugs Used In Diabetes (Second Level, Therapeutic Subgroup)
A10B = Blood Glucose Lowering Drugs, Excluding Insulins (Third Level)
A10BA = Biguanides (Fourth Level)
A10BA02 = Metformin (Fifth Level, Chemical Substance) - Forms & Dosages: Standard Tablets 250mg, 500mg, 850mg, 1000mg; Extended-Release Tablets 500mg, 750mg, 1000mg; Oral Solution 500mg/5mL; Film-Coated Tablets 500mg, 850mg, 1000mg
- Manufacturers In Australia: Local manufacturers may include generic manufacturers such as Teva, Sun Pharma, Torrent, Dr. Reddy's, Aurobindo, Apotex; brand originators historically include Merck Sante (France) and major global suppliers include Sanofi, Novartis, Sandoz, Cipla, Abbott, Glenmark, Ranbaxy
- Registration Status In Australia: Approved Rx under the Therapeutic Goods Administration (TGA) as Diaformin and Diabex
- OTC / Rx Classification: Prescription-Only Medicine (Rx)
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Worried whether the latest evidence actually supports rifaximin for your condition?
Recent, high-quality trials from 2022 to mid-2024 focus on rifaximin’s role in preventing hepatic encephalopathy relapse and improving symptoms in diarrhoeal IBS and small intestinal bacterial overgrowth.
Multicentre randomised controlled trials and pooled meta-analyses show consistent benefits for hepatic encephalopathy when rifaximin is added to standard therapy.
Short-course protocols for IBS with predominant diarrhoea often used 550 mg three times daily for two weeks with symptom improvement reported during and shortly after therapy.
Australian cohort studies from tertiary centres between 2022 and 2024 mirror international results and highlight real-world adherence, prescribing patterns and stewardship conversations.
Main Outcomes
Concerned about how much rifaximin actually helps patients?
For hepatic encephalopathy, trials comparing lactulose alone versus lactulose plus rifaximin 550 mg twice daily report relative risk reductions in recurrence commonly around 30–50%.
These studies also report fewer hospital readmissions and improved hospital-free survival in patients on rifaximin for HE maintenance therapy.
In IBS-D, pooled analyses find that a 14-day course of rifaximin 550 mg three times daily improves stool consistency and urgency, with modest sustained benefit at three months in some patients.
Traveller’s diarrhoea trials and practice reports support short 3-day courses for non-invasive E. coli-associated disease as an effective, rapid treatment option.
Safety Observations (TGA Reports)
Want to know whether rifaximin is safe for most people?
Safety surveillance shows low systemic adverse events because rifaximin is minimally absorbed from the gut.
Common side effects reported include nausea, headache and abdominal discomfort.
Rare but important events include Clostridioides difficile infection and concerns about antimicrobial resistance when courses are repeated frequently.
Australian TGA summaries align with international vigilance and recommend restricting use to approved indications and exercising caution in severe hepatic impairment.
Clinical Mechanism Of Action
Layman’s Explanation
Are you asking how rifaximin works in plain terms?
Rifaximin is a gut-targeted antibiotic that acts locally in the intestine to reduce bacterial overgrowth and to shift microbiome behaviour rather than wipe everything out.
That local action can reduce symptoms in IBS-D, treat traveller’s diarrhoea and help prevent recurrence of hepatic encephalopathy by lowering bacterial production of harmful substances.
Scientific Breakdown
Primary Pharmacology
Curious about what rifaximin does at a molecular level?
Rifaximin is a rifamycin derivative with broad activity against Gram-positive and Gram-negative gut bacteria.
It binds the β-subunit of bacterial DNA-dependent RNA polymerase, inhibiting transcription and bacterial replication.
Because it is poorly absorbed, the pharmacological effect is mainly intraluminal.
Microbiome Effects
Worried that antibiotics will completely wipe out your gut bugs?
Clinical data indicate rifaximin tends to modulate microbial function and reduce harmful metabolites such as endotoxin and ammonia rather than causing wholesale eradication.
That functional shift is relevant to hepatic encephalopathy, where less ammonia production can reduce neurocognitive flares.
For suspected SIBO contributing to IBS-D, rifaximin reduces bacterial burden and symptom drivers like bloating and diarrhoea.
Resistance is a theoretical concern, which is why stewardship and limiting unnecessary repeat courses are advised.
Scope Of Approved & Off-Label Use
Australian Approvals (TGA-Listed, PBS Inclusion)
Trying to find out when rifaximin is an approved choice in Australia?
Internationally, approved indications include secondary prevention of hepatic encephalopathy, treatment of traveller’s diarrhoea due to non-invasive E. coli, and short-course therapy for IBS-D where local regulators permit.
In Australia rifaximin is a prescription-only medicine and clinicians should consult the TGA register and current PBS lists for subsidy and authority rules.
Notable Off-Label Trends In Australian Practice
Wondering whether doctors use rifaximin for other gut problems?
In tertiary gastroenterology clinics and some rural practices, rifaximin is used off-label for recurrent IBS-D flares, for breath-test-confirmed SIBO and occasionally for compassionate use in refractory cases.
Prescribers balance symptomatic benefit with antibiotic stewardship and cost, and many institutions now require documented indication and prior therapies before repeat prescribing.
Community pharmacists report patient demand for repeat rifaximin courses and frequent questions about resistance and affordability.
Dosage Strategy
General Dosing
Not sure what dose to expect on the script?
Dosing for rifaximin is indication-specific and follows internationally validated regimens commonly used by Australian clinicians.
Typical regimens are: hepatic encephalopathy maintenance 550 mg twice daily; IBS-D 550 mg three times daily for 14 days; traveller’s diarrhoea 200 mg three times daily for three days.
Condition-Specific Dosing (PBS Recommendations)
Want to know how dosing changes with the condition?
For HE maintenance, rifaximin 550 mg twice daily is given in addition to lactulose, with monitoring of cognitive status and hospital admissions.
For IBS-D, the usual evidence-based approach is 550 mg three times daily for 14 days, with possible repeat courses for relapses though long-term continuous therapy lacks strong evidence.
Traveller’s diarrhoea dosing is short and targeted: 200 mg three times daily for three days for non-invasive E. coli.
Renal impairment rarely requires dose adjustment because absorption is minimal, but specialist review is sensible in severe hepatic dysfunction.
Safety Protocols
Contraindications (Australian Guidelines)
Is rifaximin safe for everyone?
Contraindications include known allergy to rifamycins and situations needing systemic therapy for severe infections.
Caution is recommended in severe hepatic impairment and specialist involvement is appropriate for complex cases.
Adverse Effects (Post-Market Pharmacovigilance)
What side effects should patients expect?
Because rifaximin is poorly absorbed, systemic adverse events are uncommon.
Common adverse events include nausea, abdominal pain, diarrhoea and headache.
Serious but rare problems include allergic reactions and Clostridioides difficile infection; resistance emergence with repeated courses is monitored.
Pharmacists should advise patients to seek urgent care for severe diarrhoea, allergic signs or unexpected hepatic deterioration and report serious events to the TGA.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Do food or drinks change how rifaximin works?
Rifaximin’s negligible systemic absorption means routine food interactions are minimal and tablets may be taken with or without food.
Patients with liver disease should still receive counselling about alcohol moderation and dietary measures such as low-FODMAP strategies for IBS-D.
Drug Combinations To Avoid (TGA Safety Alerts)
Worried about mixing rifaximin with other medicines?
Because systemic exposure is low, clinically important CYP interactions are uncommon with rifaximin, though classically rifamycins are enzyme inducers.
Prudent monitoring is advised when co-prescribing medications with narrow therapeutic windows, and avoid unnecessary combination with other broad-spectrum gut antibiotics to limit C. difficile risk.
TGA safety communications highlight vigilance for C. difficile when combining antibiotics and ensuring clear indication documentation for repeat courses.
Patient Experience Analysis
Australian Survey Data
What do Australian patients actually say about rifaximin?
Surveys and clinic audits from 2022–2024 report high satisfaction in HE patients because of fewer cognitive episodes and reduced admissions.
IBS-D patients frequently report rapid relief of diarrhoea and urgency during and soon after a 14-day course, though some need repeat courses for relapses.
Forum And Pharmacy Trends
Are there common patient worries picked up in forums and at the counter?
Common concerns include cost, access to repeat prescriptions, antibiotic resistance and using telehealth scripts for repeat courses.
Rural patients often face higher out-of-pocket costs and delayed specialist appointments, making pharmacists an important local source of advice on dosing, PBS eligibility and non-drug approaches.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where will you usually find rifaximin in Australia?
Rifaximin is stocked by major chains and independent pharmacies, though availability can vary with supplier cycles and pack sizes.
Pharmacists in Chemist Warehouse, Priceline and TerryWhite report demand driven by community requests and telehealth prescriptions.
Online Pharmacy Growth And Telehealth E-Scripts
Can rifaximin be ordered online or via telehealth?
Online pharmacies and telehealth e-scripts have increased access, especially in urban areas, and many patients find it convenient for repeat short courses.
In our online pharmacy, rifaximin is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
How much will rifaximin cost me?
Cost depends on whether a PBS listing applies for the indication and on pack size and brand.
Where rifaximin is not subsidised, out-of-pocket costs can be substantial and may influence adherence.
Pharmacists routinely discuss concession entitlements, Patient Assistance Programs and alternative strategies when subsidy is not available.
Alternative Options
Comparison Table Of PBS And Non-PBS Options
Looking for alternatives to rifaximin based on your condition?
Hepatic Encephalopathy: Lactulose is commonly PBS-subsidised and remains first-line for reducing ammonia with rifaximin added when recurrence is a problem.
IBS-D/SIBO: Dietary modification such as low FODMAP, loperamide for diarrhoea, probiotics and other antibiotics like metronidazole or ciprofloxacin are used depending on clinical situation.
Traveller’s Diarrhoea: Azithromycin is preferred if invasive pathogens are suspected; rifaximin suits non-invasive E. coli.
Pros And Cons Checklist
Trying to balance benefits and downsides?
Pros of rifaximin include gut-targeted action, low systemic adverse effects and proven efficacy for HE prevention and symptom relief in IBS-D.
Cons include cost where unsubsidised, stewardship and resistance concerns, and limited evidence supporting continuous long-term use for IBS-D.
Pharmacists should map PBS eligibility using product and pack templates and discuss non-pharmacological options where appropriate.
Regulatory Status
TGA Approval Framework
How does the TGA treat medicines like rifaximin?
The Therapeutic Goods Administration assesses quality, safety and efficacy for registration and maintains a register with product specifics and indications.
Post-market surveillance by the TGA informs safety communications and advice to prescribers and pharmacists.
PBS Subsidy Process
How does a medicine get subsidised on the PBS?
PBS listing requires additional assessment of clinical effectiveness relative to cost and often includes specialist restriction criteria and Authority prescribing pathways.
Pharmacists must validate PBS Authority requirements when dispensing subsidised prescriptions and assist with completing approvals where needed.
Consolidated FAQ
What are the common questions patients ask about rifaximin in Australia?
-
Is rifaximin on the PBS for my condition?
Check current PBS schedules and Authority criteria; pharmacists can confirm eligibility and help with approvals. -
Can I get repeat courses without seeing a specialist?
Repeat prescribing depends on indication and stewardship policies; GPs and specialists usually document benefit before repeat courses and pharmacists may require clarification. -
Will rifaximin cause systemic side effects or interact with my meds?
Systemic effects are uncommon due to low absorption, but report allergies and severe diarrhoea; pharmacists should check polypharmacy and liver disease context. -
Is rifaximin safe if I have liver disease?
Specialist review is recommended; rifaximin is used in hepatic encephalopathy, but severe hepatic impairment needs careful assessment. -
How much will it cost?
Cost varies by PBS status, brand and pack size; ask your pharmacist for subsidy and private price options.
Visual Guide
Want simple visuals to give to patients or put on the clinic wall?
Suggested infographic elements include a PBS vs private cost flowchart using pack sizes and Authority steps, an indication-based dosing chart for traveller’s diarrhoea, IBS-D and HE, and a pharmacy access map showing in-person, telehealth e-script and mail-order paths.
Design tips: use clear icons for duration and monitoring, add red-flag prompts for severe diarrhoea and allergy, and include pharmacist contact details and culturally appropriate translation prompts.
Storage & Transport
Household Storage Under Australian Climate
How should rifaximin be stored at home in Australia?
Keep tablets at standard room temperature, protected from moisture and direct sunlight, and store in original packaging out of reach of children.
In warm, humid areas advise patients to avoid bathroom storage and use a cool, dry cabinet instead.
Cold-Chain Logistics For Pharmacies
Do pharmacies need refrigeration for rifaximin?
No cold chain is required but dispensaries should store stock in climate-controlled rooms and avoid prolonged exposure to heat during transport or overnight in hot vehicles.
Rural pharmacies using overnight couriers should schedule deliveries to minimise heat exposure on hot days.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
How should pharmacists discuss rifaximin with patients?
Use a problem-solving, evidence-based counselling style: confirm indication, explain dosing and duration, highlight red flags, discuss cost and PBS options and advise on stewardship.
Provide clear written instructions and arrange follow-up by phone or telehealth for rural or remote patients.
National Health Authority Recommendations
What do national bodies recommend about rifaximin?
Follow TGA labelling and PBS Authority rules where applicable; for HE combine rifaximin with lactulose when indicated and prefer short targeted courses for IBS-D and traveller’s diarrhoea.
Encourage non-pharmacological measures, report adverse events to the TGA, and document outcomes when repeat courses are used.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Ballarat | Victoria | 5-9 days |
Final Practical Notes For Pharmacists
Looking for a short checklist to use at the counter?
Confirm indication and whether PBS Authority applies before dispensing or assisting a patient to access subsidy.
Explain dosing clearly: HE maintenance 550 mg twice daily, IBS-D 550 mg three times daily for 14 days, traveller’s diarrhoea 200 mg three times daily for three days.
Discuss expected timelines for symptom improvement, common adverse effects, and when to seek urgent care.
Document outcomes of therapy and limit repeat courses unless clinical benefit is clear and documented to support antibiotic stewardship.
Encourage dietary measures (for IBS-D low-FODMAP options) and liaise with prescribers for patients in aged care and those with complex polypharmacy.