
Spironolactone
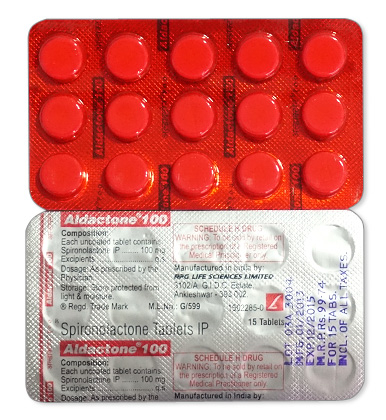
Spironolactone
- In many countries (including Australia) spironolactone is classified as a prescription-only medicine and normally requires a doctor’s prescription, however availability varies and some pharmacies or online suppliers may supply spironolactone without a prescription or receipt.
- Spironolactone is used for oedema (heart failure, cirrhosis, nephrotic syndrome), hypertension, primary aldosteronism, prevention of hypokalaemia with other diuretics, and off‑label for acne and hirsutism; it is a potassium‑sparing diuretic and aldosterone (mineralocorticoid) receptor antagonist with additional anti‑androgenic effects.
- Usual adult doses vary by indication: oedema 25–200 mg/day (typical ~100 mg/day), hypertension 25–100 mg/day, primary aldosteronism 100–400 mg/day, hirsutism/acne 50–200 mg/day; paediatric dosing is lower (approx. 1–3 mg/kg/day) and elderly or renally impaired patients usually start at the lower end with careful monitoring.
- Spironolactone is commonly supplied as oral tablets (25 mg, 50 mg, 100 mg), occasionally as compounded oral suspension, and in combination tablets with thiazide diuretics (e.g. hydrochlorothiazide) in some products.
- The diuretic effect typically begins within 24–48 hours with incremental effects over 2–3 days; anti‑androgenic benefits for acne or hirsutism may take several weeks to months to become apparent.
- Duration of action is relatively prolonged due to active metabolites (effects commonly persist 24–72 hours after a dose, with clinical effects depending on indication and dosing regimen).
- Avoid excessive alcohol while taking spironolactone as alcohol can worsen dizziness, orthostatic hypotension and dehydration; drink with caution and avoid heavy drinking.
- The most common side effects are gastrointestinal upset (nausea, vomiting, diarrhoea), drowsiness, menstrual irregularities and electrolyte disturbances—most importantly hyperkalaemia (high potassium), with gynecomastia and sexual dysfunction possible in males.
- Would you like to try spironolactone without a prescription?

Key Findings From Recent Trials
Basic Spironolactone Information
- INN (International Nonproprietary Name): Spironolactone
- Brand Names Available In Australia: Aldactone (widely marketed in Australia) with tablets commonly in 25 mg, 50 mg and 100 mg strengths.
- ATC Code: C03DA01
- Forms & Dosages: Tablets 25 mg, 50 mg, 100 mg; oral suspension (less common, sometimes compounded by pharmacies); combo tablets with hydrochlorothiazide.
- Manufacturers In Australia: Pfizer is a major manufacturer and supplier with products marketed in Australia.
- Registration Status In Australia: Registered and approved for prescription use by the TGA.
- OTC / Rx Classification: Prescription Only (Rx).
Recent evidence from 2022 to mid‑2024 reinforced spironolactone’s role in both cardiovascular and off‑label dermatology use.
Meta‑analyses and registry data continued to show mortality and hospitalisation benefits in heart failure with reduced ejection fraction when aldosterone antagonists are used at guideline doses.
For resistant hypertension, real‑world cohorts and PATHWAY‑2 follow‑ups indicate spironolactone remains the most effective fourth‑line agent, especially in low‑renin patients.
Dermatology trials reported clinical benefit for inflammatory acne and hirsutism at doses commonly between 50 mg and 200 mg daily with improvements typically evident by three to six months.
Australian post‑market safety surveillance emphasises hyperkalaemia and renal impairment as the leading harms associated with spironolactone.
Recent hospital audit data in Australia prompted a local emphasis on laboratory monitoring before and after initiation of therapy.
International trends include more teleprescribing and some combined formulary products that pair spironolactone with thiazides for selected patients.
Clinical Mechanism Of Action
Layman’s Explanation
Spironolactone blocks the salt‑retaining hormone aldosterone, helping the body remove excess fluid while sparing potassium.
The drug also reduces male hormone activity, which can help with acne and unwanted hair growth.
Scientific Breakdown
Spironolactone is an aldosterone receptor antagonist classified under ATC C03DA01.
It competitively inhibits mineralocorticoid receptors in the distal nephron to reduce sodium reabsorption and increase natriuresis while sparing potassium.
Renal/Haemodynamic Effects
Reduced aldosterone signalling decreases myocardial and vascular fibrosis and attenuates remodelling in heart failure.
Haemodynamic changes also contribute to reductions in blood pressure and relief of oedema.
Anti‑Androgenic Effects
Spironolactone exerts anti‑androgenic effects by antagonising androgen receptors and inhibiting steroidogenesis.
Those endocrine actions explain both therapeutic benefits in acne and hirsutism and adverse effects such as gynecomastia and menstrual irregularities.
Active metabolites and hepatic conversion inform dosing and monitoring decisions in clinical practice.
Scope Of Approved And Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Spironolactone is TGA‑registered and available in Australia under brand names such as Aldactone.
The TGA registration covers indications such as oedema from congestive heart failure, cirrhosis and nephrotic syndrome, certain forms of hypertension, primary hyperaldosteronism and adjunctive therapy in heart failure.
PBS subsidy depends on the indication and clinical criteria, with some heart‑failure uses historically receiving subsidy under PBAC‑approved criteria.
Notable Off‑Label Trends In Australian Practice
Dermatology is the most common off‑label area, with doses from 50 mg to 200 mg daily used for acne and hirsutism under specialist or GP supervision.
Peri‑menopausal androgenic symptoms and some transgender care regimens are also managed with spironolactone in selected patients under specialist oversight.
GPs and dermatologists increasingly document informed consent and monitoring plans when prescribing off‑label, and rural clinicians balance access with monitoring limitations.
Dosage Strategy
General Dosing
Tablets are commonly available in 25 mg, 50 mg and 100 mg strengths with a start‑low, titrate‑slow approach recommended.
Starting low and adjusting according to response and laboratory monitoring reduces the risk of hyperkalaemia and renal adverse events.
Condition‑Specific Dosing (PBS Recommendations)
Edema is typically managed with doses around 100 mg daily but the range used is 25–200 mg per day depending on response.
Hypertension doses commonly fall between 25 mg and 100 mg daily.
Primary aldosteronism for diagnostic control may require 100–400 mg daily under specialist supervision.
Heart failure adjunctive dosing is generally 12.5–50 mg daily as recommended in guideline‑aligned practice.
Off‑label dermatology dosing for acne or hirsutism is commonly 50–200 mg daily with at least three to six months before assessing full effect.
Paediatric, Elderly And Organ Impairment Adjustments
Paediatric dosing is specialist driven at approximately 1–3 mg/kg/day with close monitoring.
In elderly patients start at lower doses and monitor renal function and potassium more frequently due to higher risk of adverse events.
Renal impairment merits caution; avoid or use extreme caution when creatinine clearance is below 30 mL/min because of hyperkalaemia risk.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include acute renal insufficiency, anuria, Addison’s disease, known hypersensitivity and pre‑existing hyperkalaemia.
Relative contraindications that need close monitoring include renal impairment, liver dysfunction, pregnancy and lactation, and advanced age.
Adverse Effects (Post‑Market Pharmacovigilance)
Common mild effects are gastrointestinal upset, drowsiness and headache.
Important endocrine adverse effects include menstrual irregularities, gynecomastia and, rarely, impotence.
Hyperkalaemia and renal impairment are the primary safety signals in post‑market surveillance and are responsible for many hospitalisations that are potentially preventable with monitoring.
Recommended Monitoring Schedule
Obtain baseline serum creatinine and potassium before starting therapy.
Repeat blood tests within 3–7 days after initiation or dose change, again at one month, and then every three to six months depending on comorbidities.
Pharmacists play a key role in reminding patients about tests and documenting monitoring for PBS authority requirements where applicable.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
High‑potassium diets, salt substitutes and some sports supplements can increase the risk of hyperkalaemia when taking spironolactone.
Alcohol can worsen dizziness and orthostatic symptoms but does not have a direct pharmacokinetic interaction with spironolactone.
Caffeine has no specific pharmacological interaction beyond possible symptomatic effects such as palpitations.
Drug Combinations To Avoid (TGA Safety Alerts)
Concurrent use with ACE inhibitors, ARBs or direct renin inhibitors increases the risk of hyperkalaemia and should be monitored closely.
Potassium supplements and other potassium‑sparing diuretics are additive and generally contraindicated.
NSAIDs may reduce renal perfusion and potentiate hyperkalaemia and renal dysfunction when combined with spironolactone.
Trimethoprim can raise potassium and should prompt extra vigilance.
TGA safety communications have flagged combined RAAS blockade and community prescribing without adequate monitoring as an ongoing risk area.
Patient Experience Analysis
Australian Survey Data
Surveys and pharmacy counselling logs show mixed adherence driven by symptom benefit, side effects and monitoring inconvenience.
Many patients report improved oedema control or clearer skin, while others stop therapy because of dizziness or endocrine side effects.
Cost sensitivity is evident, with PBS subsidy status strongly influencing whether patients continue therapy long term.
Forum And Pharmacy Trends
Online forums emphasise the three to six month timeline for acne improvement and discuss practical approaches to managing menstrual changes and breast tenderness.
Pharmacists commonly field questions about contraception and pregnancy planning for women of childbearing potential starting spironolactone.
Rural patients face longer lab turnaround times and access barriers, and community pharmacists often coordinate with GPs to facilitate blood tests and dose adjustments.
Distribution And Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Aldactone and generic spironolactone tablets are widely stocked across national chains and independent pharmacies in Australia.
Packaging is typically blister packs or bottles, with 25 mg, 50 mg and 100 mg tablets commonly available.
Online Pharmacy Growth And Telehealth E‑Scripts
Online pharmacies and telehealth prescribing expanded significantly through 2020–24, improving remote access.
Despite easier access through e‑scripts, laboratory monitoring logistics remain a barrier for safe remote prescribing.
In our online pharmacy, spironolactone is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS Vs Private Cost Comparisons
Where PBS applies, patient co‑payments are substantially lower and continuity of treatment is more likely.
Private scripts can vary widely in price between chains and independent pharmacies, prompting customers to compare prices at popular retailers.
Rural supply chains sometimes have delays, and pharmacies mitigate this with buffer stock and patient reminder systems.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
Key alternatives include eplerenone, which is a selective aldosterone antagonist with fewer hormonal effects but higher cost.
Amiloride and triamterene are potassium‑sparing diuretics with differing potency profiles and are sometimes used as alternatives or adjuncts.
Thiazides and ACE inhibitors/ARBs remain important for blood pressure control but have different electrolyte effects.
Pros And Cons Checklist
- Spironolactone: Effective, low‑cost generics, anti‑androgenic side effects can be both therapeutic and adverse.
- Eplerenone: Less endocrine adverse effects but usually costlier and indication specific.
- Amiloride/Triamterene: Useful when potassium needs to be conserved, with different efficacy profiles.
Choice depends on indication, comorbidity, PBS eligibility and monitoring capacity.
Regulatory Status
TGA Approval Framework
Spironolactone is a prescription‑only medicine registered with the TGA and assessed for safety, quality and efficacy.
Post‑market surveillance informs label updates and ongoing safety communications from the regulator.
PBS Subsidy Process
PBAC assesses clinical benefit and cost‑effectiveness for PBS subsidy decisions and may attach authority requirements to subsidised listings.
Prescribers should confirm current PBS listings and any authority codes when prescribing for subsidy eligibility.
Consolidated FAQ
Q1: Can I get spironolactone on PBS?
A1: It depends on the indication and PBAC/PBS criteria, with heart‑failure uses commonly having subsidy pathways; check the Schedule and authority requirements.
Q2: How long until acne improves?
A2: Expect three to six months for meaningful change when used for acne or hirsutism.
Q3: Is it safe in pregnancy?
A3: Spironolactone is generally avoided in pregnancy and breastfeeding without specialist input due to potential endocrine effects; discuss contraception if appropriate.
Q4: What monitoring is required?
A4: Baseline creatinine and potassium, repeat within three to seven days after starting or changing dose, then at one month and periodically thereafter.
Q5: What signs require urgent care?
A5: Severe weakness, palpitations, collapse, or persistent vomiting and diarrhoea may indicate hyperkalaemia or dehydration and require emergency care.
Visual Guide
Suggested infographic elements include a PBS versus private cost bar chart showing typical co‑payments for concession, general and private scripts.
Another useful visual is a dosage timeline that highlights starting doses, titration steps and monitoring checkpoints at three to seven days, one month and three months.
A pharmacy distribution map contrasting national chains and independent rural access with typical stock and lead times supports patient planning.
A safety flowchart should show baseline labs, contraindications and action thresholds for potassium and creatinine with clear next steps.
Storage And Transport
Household Storage Under Australian Climate
Store spironolactone tablets at 20–25°C and protect from light and moisture.
Avoid keeping tablets in the bathroom where humidity is high or in a hot car during summer.
Keep medication in its original container and out of reach of children.
Cold‑Chain Logistics For Pharmacies
Normal ambient transport in cool, dry conditions is adequate and no special cold‑chain is required.
Avoid freezing and prolonged heat exposure and document any temperature excursions with standard pharmacy procedures.
Compounded oral suspensions should be labelled with storage requirements and expiry according to the pharmacist’s protocol.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Confirm the indication and PBS status before counselling on spironolactone.
Review concurrent medicines such as ACE inhibitors, ARBs, potassium supplements and NSAIDs that raise risk of hyperkalaemia or renal impairment.
Counsel on common side effects including dizziness, menstrual changes and breast tenderness and advise on signs of hyperkalaemia.
Set up a clear monitoring schedule and liaise with the prescriber for dose adjustments in renal impairment.
National Health Authority Recommendations
TGA, therapeutic guidelines and PBAC principles stress evidence‑based indication and the need for shared decision making.
Robust biochemical monitoring is required to reduce hyperkalaemia risk, and recall systems or shared electronic records improve safety for rural and telehealth patients.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
Closing Practical Notes
Before starting spironolactone ensure baseline kidney function and potassium are checked and documented.
Keep a personal record of all medicines, supplements and over‑the‑counter products to share with your pharmacist or GP.
Report symptoms such as new‑onset muscle weakness, palpitations or severe nausea immediately as these can indicate hyperkalaemia.
If cost is a concern, check PBS eligibility and consider comparing prices across national chains and independent pharmacies.
For rural patients, discuss blood‑test logistics with the prescribing clinician and your pharmacy to ensure timely monitoring.