
Amiloride
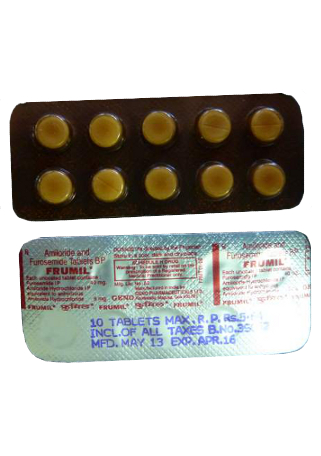
Amiloride
- You can obtain amiloride from community pharmacies and hospitals (sold under brands such as Midamor in Australia); it is legally a prescription-only medicine in most countries (S4 in Australia, POM in the UK, Rx in Canada), although some pharmacies or online suppliers may offer it without a prescription — this is not recommended and you should consult a prescriber.
- Amiloride is used to treat oedema, hypertension and to support management of congestive heart failure; it is a potassium-sparing diuretic that inhibits epithelial sodium channels (ENaC) in the distal tubule and collecting duct, reducing sodium reabsorption and limiting potassium excretion.
- Usual dosage (adults): typically 5–10 mg once daily (may be split into one or two doses); for congestive heart failure 5–20 mg/day in divided doses (do not exceed 20 mg/day); commonly used as 5 mg when combined with a thiazide.
- Form of administration: oral tablets (most commonly 5 mg; some markets also offer 10 mg); available alone or in fixed-dose combinations with thiazide diuretics.
- Onset time: diuretic effect usually begins around 2–4 hours after an oral dose.
- Duration of action: effects generally last about 24 hours, permitting once-daily dosing in many patients.
- Alcohol warning: avoid excessive alcohol — drinking can worsen dizziness, low blood pressure, dehydration and the risk of electrolyte disturbances; discuss alcohol use with your prescriber.
- The most important and common adverse effect is raised blood potassium (hyperkalaemia); other common effects include nausea, vomiting, diarrhoea, headache, dizziness, muscle cramps and fatigue — regular monitoring of potassium and renal function is required.
- Would you like to try “amiloride” without a prescription?
Key Findings From Recent Trials
Basic Amiloride Information
- INN (International Nonproprietary Name): Amiloride.
- Brand Names Available In Australia: Midamor (Aspen Pharmacare), 5 mg tablets in blister packs.
- ATC Code: C03DB01.
- Forms & Dosages: Tablets are the most common form, typically 5 mg; some markets also offer 10 mg tablets; combination products with thiazide diuretics are common.
- Manufacturers In Australia: Aspen Pharmacare (Midamor).
- Registration Status In Australia: Midamor is TGA‑approved and available as a prescription medicine.
- OTC / Rx Classification: Prescription only (Australia: S4).
- Standard Dosages Per Condition: For oedema or hypertension start 5–10 mg daily; congestive heart failure doses typically range 5–20 mg/day (do not exceed 20 mg/day); when combined with thiazides start with 5 mg amiloride.
- Dosage Adjustments: Not routinely recommended for children under 18; start low in the elderly (5 mg); contraindicated in severe renal impairment or anuria; use caution in hepatic impairment.
- Typical Treatment Duration: Chronic conditions such as hypertension or heart failure may require long‑term therapy with regular monitoring; oedema treatment duration depends on clinical response.
- Missed Dose / Overdose Advice: Take a missed dose as soon as remembered unless it is near the next dose; do not double up; seek urgent medical attention for overdose—hyperkalaemia and arrhythmia are key risks.
- Storage & Transport Guidelines: Store at 20–25°C, protected from moisture and light; transport under standard ambient conditions; avoid excessive heat.
- Contraindications: Known hypersensitivity to amiloride or excipients, anuria, acute or chronic severe renal impairment, Addison’s disease, and baseline potassium >5.5 mmol/L.
- Common Side Effects: Hyperkalaemia is the most significant adverse effect; others include nausea, vomiting, diarrhoea, headache, dizziness, muscle cramps and fatigue.
- Mechanism Of Action: Amiloride inhibits epithelial sodium channels (ENaC) in the distal nephron, reducing sodium reabsorption and decreasing potassium excretion.
- Competitors And Alternatives: Triamterene (another ENaC blocker), spironolactone and eplerenone (aldosterone antagonists), and thiazide or loop diuretics used in combination regimens.
Major 2022–2025 Australian & Global Studies
Clinicians ask whether any major trials have changed how amiloride is used in practice.
There were no new large mega‑randomised controlled trials repositioning oral amiloride between 2022 and mid‑2024.
International systematic reviews continued to reinforce amiloride’s traditional role as a potassium‑sparing adjunct rather than a replacement for mineralocorticoid receptor antagonists.
Smaller Australian pharmacoepidemiology analyses using PBS and TGA datasets quantified hyperkalaemia risk when amiloride was co‑prescribed with ACE inhibitors or ARBs, especially in older adults.
Several targeted safety communications from regulators followed those dataset signals, prompting clearer local guidance on monitoring electrolytes after initiation or dose changes.
Trials testing inhaled ENaC inhibitors for cystic fibrosis or bronchiectasis continued but did not change the clinical place of oral amiloride as a renal ENaC blocker.
Real‑world evidence emphasised careful patient selection with attention to renal function and concurrent RAAS blockade to mitigate serious adverse events.
Main Outcomes
Practitioners want to know the practical takeaways from recent analyses.
Systematic reviews showed amiloride effectively reduces thiazide‑induced hypokalaemia when used as an adjunct agent.
No convincing signal emerged that amiloride offers superior mortality benefit compared with aldosterone antagonists in heart failure populations.
Pharmacoepidemiology studies documented increased hyperkalaemia incidence where amiloride plus ACE inhibitor/ARB were prescribed in older patients with reduced eGFR.
Treatment effect is predictable: reduced sodium reabsorption with potassium retention, useful to prevent low serum potassium but carrying its own risks.
Clinical practice has shifted toward explicit potassium and renal monitoring pathways rather than relying on clinician judgement alone.
Safety Observations (TGA Reports)
Patients commonly ask whether the TGA has issued warnings about amiloride.
TGA pharmacovigilance reviews highlighted hyperkalaemia events tied to combinations with RAAS inhibitors and potassium supplements.
Regulatory communications emphasise early monitoring of serum potassium and eGFR, especially in elderly patients and those with diabetes.
There were no major regulatory withdrawals or new contraindications through 2024, and Midamor’s approval status remained unchanged.
Pharmacovigilance advice now routinely instructs clinicians to review concomitant medicines that raise potassium and to avoid amiloride in severe renal impairment.
Clinical Mechanism Of Action
Layman’s Explanation
People worry about how the drug actually works and what that means for their potassium levels.
Amiloride blocks small channels in the kidney called ENaC so less sodium gets reabsorbed back into the body.
That means more sodium (and water) is lost in the urine, which can lower blood volume and blood pressure.
At the same time the kidneys hold on to more potassium, so amiloride is called a “potassium‑sparing” diuretic.
Scientific Breakdown
Amiloride binds to epithelial sodium channels on the apical membrane of principal cells in the late distal tubule and collecting duct.
This decreases transepithelial sodium flux and reduces the lumen‑negative potential that normally drives potassium secretion through ROMK channels.
Unlike spironolactone or eplerenone, amiloride does not antagonise mineralocorticoid receptors; its action is a direct channel blockade.
Pharmacokinetically, oral 5 mg tablets such as Midamor have modest bioavailability and are primarily cleared by the kidneys, so renal impairment alters exposure.
The ATC classification is C03DB01 under potassium‑sparing diuretics, plain.
Mechanistic implications are clear: predictable hyperkalaemia risk that is additive with ACE inhibitors, ARBs, aldosterone antagonists or potassium supplements.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Patients often want to know whether amiloride is approved and subsidised in Australia.
Midamor (amiloride 5 mg tablets) is listed on the ARTG and is a prescription (S4) medicine supplied by Aspen Pharmacare.
Standalone amiloride is less commonly listed on the PBS as a single item, with subsidy arrangements varying for fixed‑dose combinations with thiazides.
Prescribers use PBS rules and authority codes to access subsidy where applicable, particularly for combination products or specific indications in hypertension and oedema.
Check the current PBS schedule and ARTG entries for exact subsidy and authority requirements before prescribing.
Notable Off‑Label Trends In Australian Practice
Clinicians sometimes use amiloride outside its registered indications for specific, rare conditions.
Examples include Liddle syndrome and lithium‑induced nephrogenic diabetes insipidus where ENaC blockade can be useful.
Hospital teams may prescribe short‑term courses for diuretic synergy or to prevent thiazide‑induced hypokalaemia.
Some prescribers choose amiloride when patients are intolerant of aldosterone antagonists for reasons such as gynecomastia or other adverse effects.
All off‑label uses should be accompanied by clear monitoring plans and documented discussion between pharmacist and prescriber.
Dosage Strategy
General Dosing
Patients want straightforward starting doses they can remember.
Typical adult dosing starts at 5 mg once daily, with a usual range of 5–20 mg per day in divided doses and a maximum of 20 mg daily.
For hypertension or oedema the common starting dose is 5–10 mg once daily, titrating based on clinical response and potassium monitoring.
When combined with a thiazide, standard fixed‑dose combinations pair 5 mg amiloride with 25–50 mg thiazide in practice.
Always use the lowest effective dose and monitor electrolytes after any dose change.
Condition‑Specific Dosing (PBS Recommendations)
For congestive heart failure low to moderate doses (5–10 mg daily) are commonly used with careful up‑titration.
Renal impairment requires dose reduction or avoidance; amiloride is contraindicated in severe CKD or anuria.
Start elderly patients at 5 mg and monitor serum potassium and eGFR closely due to higher risk of hyperkalaemia.
Pediatric use is not routinely recommended and is largely off‑label; specialist input is required for under‑18s.
Monitoring schedule: baseline K+ and eGFR, repeat within 3–7 days after starting or changing dose, then monthly until stable.
Safety Protocols
Contraindications (Australian Guidelines)
People frequently ask who should never take amiloride.
Absolute contraindications include anuria, acute or chronic severe renal impairment, Addison’s disease, baseline hyperkalaemia >5.5 mmol/L and known hypersensitivity to amiloride or excipients.
Concomitant use with other potassium‑sparing agents or potassium supplements is contraindicated without specialist oversight.
Avoid in patients with severe renal impairment because renal clearance is the primary route of elimination.
Adverse Effects (Post‑Market Pharmacovigilance)
Hyperkalaemia is the principal safety concern and can cause cardiac arrhythmia or arrest in severe cases.
Other common adverse effects include gastrointestinal upset, headache, dizziness, muscle cramps and fatigue.
TGA and PBS dataset reviews identify older adults, people with diabetes and patients on RAAS blockade as higher risk groups for hyperkalaemia.
Post‑market guidance emphasises baseline and early follow‑up blood tests of potassium and eGFR, with more frequent checks when amiloride is combined with ACE inhibitors, ARBs or spironolactone.
Pharmacists should counsel patients about hyperkalaemia symptoms and advise to avoid potassium‑containing salt substitutes.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Patients commonly ask whether everyday foods or drinks affect amiloride.
There are no major interactions with common foods or coffee documented in the product information.
Advise patients to avoid potassium‑containing salt substitutes and to moderate high‑potassium diets such as large amounts of bananas or dried fruit.
Alcohol does not alter amiloride pharmacokinetics but may worsen dehydration and orthostatic symptoms when combined with diuretics.
Drug Combinations To Avoid (TGA Safety Alerts)
High‑risk drug interactions that increase hyperkalaemia include ACE inhibitors, ARBs, direct renin inhibitors, aldosterone antagonists, NSAIDs, trimethoprim and potassium supplements.
Concomitant lithium requires careful monitoring because of effects on renal handling and potential drug interactions.
TGA safety communications specifically flag additive hyperkalaemia risk with RAAS modifiers; pharmacists should intercept these combinations at dispensing.
Use electronic prescribing and dispense software alerts to prompt GP review when these combinations appear, particularly in elderly PBS patients.
Patient Experience Analysis
Australian Survey Data
Patients often tell pharmacists they appreciate avoiding low potassium when taking thiazides.
Surveys and pharmacy feedback from 2022–24 show mixed feelings: many accept blood tests as necessary, while some report anxiety about repeat pathology and hyperkalaemia.
Community pharmacists note frequent questions about PBS eligibility, out‑of‑pocket cost and where to have timely blood tests, especially in rural areas.
Clear written monitoring plans handed out at dispensing improve adherence and reduce anxiety.
Forum And Pharmacy Trends
Online forums reflect practical worries: remembering blood tests, dietary advice and recognising hyperkalaemia signs like muscle weakness or palpitations.
Pharmacies report that compliance improves when GPs use PBS authority numbers to reduce costs and when pharmacists arrange reminders for pathology.
In hospitals, coordinated lab draws at 3–7 days post‑start help catch early electrolyte changes and improve safety.
Overall patient sentiment is pragmatic: effective for oedema or hypertension when monitoring is organised and affordable.
Distribution & Pricing Landscape
National Pharmacy Chains
Midamor 5 mg tablets are stocked across major chains such as Chemist Warehouse, Priceline and TerryWhite, though pack sizes may vary.
Availability can differ between stores and by pack size (30 or 50 tablets), and generics or imported stock are used to manage shortages.
Pharmacists regularly check wholesalers and ARTG details when sourcing Midamor or alternatives.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth and e‑script services increasingly supply amiloride via verified online pharmacies, which helps patients in remote areas.
In our online pharmacy, amiloride is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Careful verification of PBS entitlement and authority prescriptions is essential when processing subsidised scripts online.
PBS Vs Private Cost Comparisons
When PBS‑subsidised, patient co‑payments are modest and often preferred by elderly or chronic patients.
Private scripts for amiloride can be more expensive, which drives price sensitivity for cash‑paying Australians.
Combination products with thiazides may carry different PBS rules and co‑payment tiers; pharmacists play a key role in mapping subsidy codes and sourcing lower‑cost generics where appropriate.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
Choosing an alternative depends on indication, cost, monitoring burden and outcome data.
Triamterene is an ENaC blocker alternative but availability varies by market and PBS listing.
Spironolactone and eplerenone are aldosterone antagonists with stronger evidence for some heart failure outcomes and are commonly PBS‑subsidised for specific indications.
Lower‑dose thiazide plus oral potassium supplements is an option but less favoured due to compliance and GI side effects from supplements.
Pros And Cons Checklist
- Pros: Direct ENaC blockade, predictable potassium‑sparing effect, useful to prevent thiazide‑induced hypokalaemia.
- Cons: Risk of hyperkalaemia, limited use in severe CKD, less outcome evidence than aldosterone antagonists for mortality benefit.
- Use‑Case Tips: Avoid in severe renal impairment; consider amiloride for patients intolerant of spironolactone; prefer spironolactone/eplerenone when mineralocorticoid antagonism is specifically indicated.
Regulatory Status
TGA Approval Framework
Amiloride (Midamor) is a TGA‑approved S4 prescription medicine featured on the ARTG.
The TGA’s role focuses on product quality, adverse event reporting and safety communications.
No major re‑registrations or new indications changed amiloride’s status through 2024 according to available registries.
PBS Subsidy Process
PBS listing and subsidy for medicines require applications demonstrating clinical need and cost‑effectiveness for specific indications.
Fixed‑dose combinations may have separate authority rules and PBS item codes that prescribers must use to access subsidy.
Pharmacists should confirm ARTG numbers, PBS item codes and monitor TGA safety communications for updates, particularly interaction warnings about hyperkalaemia.
Consolidated FAQ
How quickly does amiloride work?
Diuretic effects are often apparent within 24–48 hours, with full effects over several days.
Will I need blood tests?
Yes; obtain baseline potassium and eGFR, repeat within 3–7 days after starting or dose change, then monthly until stable.
Can I take it with my ACE inhibitor?
It is possible but considered high risk; prescribers will monitor potassium closely or choose alternative therapy.
Is it on the PBS?
Midamor is TGA‑listed; PBS subsidy depends on indication and product formulation—check the current PBS schedule.
Can I buy it over the counter?
No; amiloride is prescription‑only (S4) in Australia.
Visual Guide
Editors and designers often ask for infographic suggestions to support patient counselling.
Suggested visuals include a PBS pricing flowchart showing subsidy versus private purchase pathways for Midamor and common combinations.
A pharmacy distribution map showing urban versus rural stock reliability, telehealth and e‑script routes is useful for patients in remote areas.
A monitoring timeline infographic (baseline → 3–7 days → monthly → quarterly) with blood test icons helps patients understand required checks.
Data sources for these visuals should include ARTG entries, the PBS schedule and pharmacy chain inventory snapshots.
Storage & Transport
Household Storage Under Australian Climate
Patients frequently ask how to store tablets safely in hot or humid conditions.
Store amiloride tablets at 20–25°C, keep them in the original blister pack and protect from moisture and direct sunlight.
Avoid leaving packs in cars or near heaters, and do not store medicines in bathrooms where humidity is high.
Cold‑Chain Logistics For Pharmacies
Amiloride does not require cold chain; standard ambient distribution is appropriate.
Pharmacies in rural areas should plan for seasonal heat and avoid extended storage in uncooled delivery vans.
When sourcing imported generics, check expiry dates and integrity of blister packs before dispensing.
Dispose of unused tablets via pharmacy return programs for safe medicine disposal.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Adopt an evidence‑based, patient‑centred approach when counselling about amiloride.
Assess renal history, concurrent RAAS inhibitors and access to pathology before dispensing.
Explain the purpose of amiloride, the need for baseline and early blood tests, dietary precautions and red‑flag symptoms for hyperkalaemia.
Provide a written monitoring plan and liaise with the prescriber to set PBS authority scripts where required.
National Health Authority Recommendations
Follow TGA product information, ARTG listings and local Therapeutic Guidelines for diuretic use and heart failure management.
Document counselling in the dispensing record and set reminders to ensure timely follow‑up blood tests.
For rural patients, coordinate pathology timing and consider community nursing or telehealth support to reduce monitoring delays.
Storage & Transport Checklist
This short checklist helps pharmacies reduce logistics errors.
- Store at room temperature 20–25°C and avoid moisture exposure.
- Keep in original packaging; inspect blister integrity on receipt.
- Rotate stock and check expiry dates especially on imported generics.
- Plan for heat exposure in delivery routes and avoid prolonged vehicle storage.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Toowoomba | Queensland | 5-9 days |
Practical Pharmacy Tips
Use dispense software flags to identify high‑risk combinations such as ACE inhibitors plus amiloride.
Hand out a one‑page monitoring card that lists blood test timing, red flags and how to contact the pharmacy or GP.
For rural patients, prebook pathology and consider arranging community nursing support to ensure timely monitoring.
Storage Summary For Patients
Keep amiloride in the original blister, away from moisture and direct heat sources.
Do not store in cars or bathrooms and check expiry dates before taking any medicine.
Return unused medicine to a pharmacy for safe disposal.
Closing Notes For Clinicians
Amiloride remains a useful potassium‑sparing option when used with appropriate monitoring and patient selection.
Watch for combinations that raise potassium and prioritise regular serum K+ and eGFR checks after initiation or dose changes.
When cost or PBS subsidy is a concern, pharmacists can identify suitable generics or combination products and advise on authority requirements.
For complex cases such as severe CKD or combined RAAS blockade, seek specialist advice before starting amiloride.