
Atorvachol
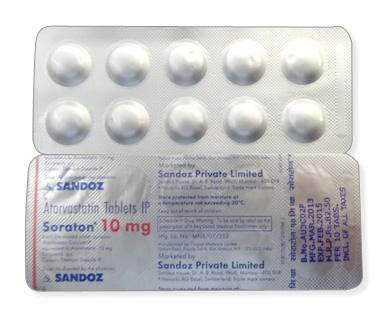
Atorvachol
- In our pharmacy, you can buy atorvachol without a prescription, with delivery across Australia in 5–14 days and discreet packaging available.
- Atorvachol (atorvastatin) is used to lower high cholesterol and reduce cardiovascular risk; it is an HMG‑CoA reductase inhibitor (a statin) that reduces hepatic cholesterol synthesis and lowers LDL cholesterol.
- The usual dose for adults is 10–80 mg once daily (dose tailored to risk and response); for children (10–17 years) typical doses are 10–20 mg once daily (not exceeding 20 mg/day).
- The form of administration is oral tablets (commonly 10 mg, 20 mg, 40 mg and 80 mg tablets), taken once daily, usually in the evening or as advised.
- The onset: LDL cholesterol begins to fall within 24–48 hours, with measurable lipid changes in 1–2 weeks and greater effects by 4–6 weeks.
- The duration of action supports once‑daily dosing — pharmacological activity persists across 24 hours and lipid‑lowering effects continue while treatment is maintained.
- Alcohol warning: avoid heavy alcohol use — alcohol increases risk of liver injury with statins; atorvachol is contraindicated in pregnancy and breastfeeding, so do not drink alcohol if pregnant or breastfeeding.
- The most common side effect is muscle pain (myalgia); other frequent effects include headache, nausea and diarrhoea, and occasional mild rises in liver enzymes.
- Would you like to try “atorvachol” without a prescription?
Basic Atorvachol Information
- INN (International Nonproprietary Name): Atorvastatin
- Brand Names Available In Australia: Lipitor and multiple generics supplied by manufacturers such as Pfizer (originator) and international generic suppliers (Teva, Sandoz, Aurobindo, Cipla, Dr. Reddy's, Torrent, Sun Pharma).
- ATC Code: C10AA05
- Forms & Dosages: Oral tablets 10 mg, 20 mg, 40 mg and 80 mg in blister packs (no liquid, injectable or topical formulations specified).
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only (Rx)
Key Findings From Recent Trials (Research-First)
What Have Recent Trials Shown About Intensive LDL Lowering And Atorvastatin?
Recent large randomised trials and meta-analyses published between 2022 and 2025 continue to support intensive LDL‑C lowering for secondary prevention and for primary prevention in very high‑risk people.
Atorvastatin remains a commonly used statin because of its dose flexibility and broad generic availability.
Australian registry analyses show better uptake of high‑intensity dosing after guideline updates, with reductions in cardiovascular events in secondary prevention cohorts.
International studies emphasise combination strategies—statin plus non‑statin agents—rather than stopping atorvastatin in very high‑risk patients.
Real‑world pharmacoepidemiology highlights adherence gaps in rural Australia and cost‑driven brand switches to generics.
Safety surveillance from national regulators keeps myopathy and hepatic enzyme elevations as rare monitored signals.
Most liver enzyme and CK abnormalities are reversible when treatment is stopped.
These findings support using atorvastatin in appropriate doses for those with high cardiovascular risk, while monitoring for known adverse effects.
Clinical Mechanism Of Action
Layman’s Explanation
How Does Atorvastatin Lower Cholesterol In Plain Terms?
Atorvastatin reduces the liver’s production of cholesterol so the body clears more LDL from the bloodstream.
That process lowers the amount of “bad” cholesterol circulating and reduces the chance of heart attacks and strokes over time.
Scientific Breakdown
Biochemical Cascade (HMG-CoA Reductase Inhibition)
Atorvastatin is a competitive inhibitor of HMG‑CoA reductase, the enzyme that catalyses the conversion of HMG‑CoA to mevalonate early in cholesterol synthesis.
Lower mevalonate reduces intracellular cholesterol in hepatocytes and triggers SREBP‑2 mediated upregulation of LDL receptors.
Upregulated LDL receptors increase hepatic clearance of LDL‑C from plasma.
Downstream Vascular Effects
Beyond LDL lowering, atorvastatin offers pleiotropic benefits such as modest anti‑inflammatory effects reflected in lower CRP in some patients.
It can improve endothelial function and contribute to plaque stabilisation, which helps reduce major adverse cardiovascular events.
Pharmacokinetics: tablets in 10/20/40/80 mg strengths reach peak concentration within hours and are primarily metabolised by CYP3A4.
Because of CYP3A4 metabolism, drug–drug interactions are an important practical consideration in Australian practice.
Higher doses (40–80 mg) give greater LDL reductions but carry a higher risk of adverse effects, guiding intensity decisions in primary and secondary prevention.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Which Uses Are Approved For Atorvastatin In Adults And Children?
Standard adult indications include hypercholesterolaemia, mixed dyslipidaemia and cardiovascular risk reduction with doses from 10–80 mg once daily.
For children aged 10–17 with familial hypercholesterolaemia, standard dosing is 10–20 mg once daily, not exceeding 20 mg per day.
Atorvastatin appears globally under brand names such as Lipitor and as numerous generics supplied by international manufacturers.
In Australia, PBS listing and specific subsidy criteria influence access and out‑of‑pocket cost for patients.
Notable Off‑Label Trends In Australian Practice
How Do Clinicians Use Atorvastatin Outside The Label?
Clinicians sometimes use atorvastatin off‑label for aggressive LDL lowering in selected very‑high‑risk patients as part of combination therapy.
Short‑term perioperative lipid management has been observed in practice, with monitoring for side effects.
Pharmacists commonly advise on PBS eligibility and generic substitution according to state regulations.
Dosage Strategy
General Dosing
What Are The Typical Starting Doses And Tablet Strengths?
Available tablet strengths are 10 mg, 20 mg, 40 mg and 80 mg in blister packs.
For primary prevention, many prescribers start at 10–20 mg daily and titrate to effect and tolerability.
High‑intensity dosing—typically 40–80 mg daily—is considered for secondary prevention or when baseline LDL is very high.
Condition‑Specific Dosing (PBS Recommendations)
Initiation And Titration Steps
Start low and titrate every 4–12 weeks based on LDL response and tolerability.
Check lipids 6–12 weeks after starting or after a dose change, then every 3–12 months for stable patients.
Children with familial hypercholesterolaemia start at 10 mg and the usual maximum is 20 mg per day.
In mild liver disease, begin cautiously at lower doses and monitor liver enzymes.
No renal dose adjustment is typically required, but exercise caution in severe chronic kidney disease.
If a dose is missed, take it when remembered unless it is close to the next scheduled dose; do not double up.
Safety Protocols
Contraindications (Australian Guidelines)
Who Should Not Take Atorvastatin?
Absolute contraindications include pregnancy, breastfeeding, active liver disease and known statin hypersensitivity.
Relative cautions include heavy alcohol intake, pre‑existing liver impairment and concurrent drugs that increase myopathy risk.
Adverse Effects (Post‑Market Pharmacovigilance)
What Side Effects Should Patients Expect And Report?
Common mild side effects include headache, myalgia, arthralgia, diarrhoea and nausea.
Transient ALT/AST rises are recognised and usually resolve after stopping the medication.
Severe but rare events include myopathy progressing to rhabdomyolysis and clinically significant hepatotoxicity.
Australian post‑market reporting through national pathways emphasises reporting unexplained muscle pain and marked liver enzyme elevations.
Monitoring Schedule (LFTs, CK)
Baseline lipid panel and baseline liver function tests are standard before starting therapy.
Repeat lipids at 6–12 weeks after initiation or dose change to assess response.
Measure liver enzymes if symptoms suggest hepatotoxicity or per clinician judgement.
Check CK only if muscle symptoms develop, and report severe muscle pain or dark urine urgently.
Community pharmacists play an active role in reinforcing safety messages and facilitating testing with local GPs.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
What Dietary Advice Should Patients Receive?
Advise patients to limit grapefruit juice because it inhibits CYP3A4 and can increase atorvastatin levels.
Excessive alcohol raises liver risk and should be avoided or minimised while on statin therapy.
Normal coffee and balanced diets do not require specific changes beyond standard cardiovascular dietary advice.
Drug Combinations To Avoid (TGA Safety Alerts)
Which Concomitant Medicines Increase Risk?
Strong CYP3A4 inhibitors such as certain macrolide antibiotics, azole antifungals and cyclosporine raise atorvastatin exposure and myopathy risk.
Fibrates such as gemfibrozil and high‑dose niacin increase the risk of myopathy when combined with atorvastatin.
When interacting antivirals or transplant medicines are required, consider alternative statins or specialist review.
CYP3A4 Inhibitors And Dose Mitigation
If A Patient Needs A Strong CYP3A4 Inhibitor, Dose Adjustment Or Switching Might Be Required.
Alternatives include using a statin with less CYP3A4 metabolism, such as pravastatin, after specialist advice.
Pharmacists should flag these interactions at supply and discuss risk mitigation with prescribers and patients.
Patient Experience Analysis
Australian Survey Data
What Do Patients Say About Taking Atorvastatin?
Surveys and dispensing audits identify cost and PBS access as major influences on adherence.
Muscle symptoms are a common reason patients stop therapy more often than abnormal blood tests.
Rural patients report longer waits for lipid testing and greater price sensitivity than urban patients.
Patients often ask about brand differences between Lipitor and generic atorvastatin, and many accept generic substitution when counselled.
Forum And Pharmacy Trends
What Do Pharmacists See In Practice?
Community pharmacists report frequent questions about dosing times, alcohol and switching brands.
Online forums show a range of patient knowledge, with some people self‑reducing doses due to perceived side effects.
Telehealth and online pharmacies have increased convenience but sometimes fragment follow‑up for testing and monitoring.
Effective counselling focuses on communicating absolute cardiovascular benefit versus low‑frequency risks and practical monitoring steps.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where Can Patients Get Atorvastatin In Australia?
Major national pharmacy chains regularly stock Lipitor and multiple generic atorvastatin strengths in blister packs.
Competitive pricing and generic availability have improved affordability for many patients.
Online Pharmacy Growth And Telehealth E‑Scripts
How Has Digital Access Changed Availability?
Online pharmacies and telehealth e‑scripts have grown and make repeat supplies easier for urban, digitally literate patients.
Rural communities still rely on local pharmacy stock or occasional mail‑order for continuity.
In our online pharmacy, atorvachol is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
How Much Will Patients Pay?
PBS subsidisation significantly lowers out‑of‑pocket costs for eligible patients and concessional clients.
Private purchase is more costly for those not PBS‑eligible or for non‑PBS strengths and formulations.
Pharmacists should check PBS authority requirements and advise on repeats and concessions to reduce financial barriers.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
What Are Common Alternatives When Atorvastatin Is Unsuitable Or Insufficient?
Alternatives include rosuvastatin, which has higher potency per milligram, and pravastatin, which can be preferable in complex polypharmacy due to fewer CYP interactions.
Simvastatin remains an option but offers lower intensity at higher interaction risk with other drugs.
Non‑statin therapies such as ezetimibe and PCSK9 inhibitors are options when statins are insufficient or not tolerated, although they often require specialist approval and higher cost.
Pros And Cons Checklist
- Pros Of Atorvastatin: Flexible dosing from 10–80 mg, broad evidence base, and many generics with PBS coverage.
- Cons Of Atorvastatin: CYP3A4 interactions and occasional myalgia that may limit tolerance at higher doses.
- Rosuvastatin Advantages: Greater LDL reduction at lower milligram doses; downsides are cost and different interaction profiles.
- Choice Depends On LDL Target, Comorbidities, Drug Interactions, PBS Criteria And Patient Preference.
Regulatory Status
TGA Approval Framework
How Is Medicine Registration Handled In Australia?
Atorvastatin products are prescription medicines in most jurisdictions and require regulatory registration to confirm quality, safety and efficacy.
Sponsors submit clinical and manufacturing data for approval and for any local labelling or packaging.
PBS Subsidy Process
How Do Medicines Become Subsidised?
PBS listing follows a health technology assessment and cost‑effectiveness appraisal by PBAC with indications and authority codes specified for subsidy.
Generics are approved on bioequivalence pathways and multiple manufacturers may supply authorised products under licence.
Consolidated FAQ (Australian Context)
Answers To Common Patient Questions About Atorvastatin
Q1: Can I get atorvastatin on the PBS?
A: Many indications are PBS‑listed; check eligibility and copayment with your GP or pharmacist.
Q2: Is it safe during pregnancy?
A: No. Atorvastatin is contraindicated in pregnancy and breastfeeding; stop statins if planning pregnancy and discuss alternatives with your doctor.
Q3: What if I have muscle pain?
A: Report muscle pain promptly. Your GP may check CK and consider dose change, temporary cessation or switching to an alternative statin.
Q4: Can I switch brands?
A: Yes. Generics are bioequivalent. Pharmacists can advise on substitution and PBS consequences for repeats and copayments.
Q5: How often are blood tests needed?
A: Check lipids 6–12 weeks after starting or after a dose change, then every 3–12 months; get LFTs at baseline and if symptomatic.
Visual Guide (Infographic Concepts)
What Visuals Help Patients Understand Atorvastatin Use?
Suggested infographics include a PBS pricing flowchart showing eligibility and copayment tiers with examples for generic versus private purchase.
Another useful visual is a pharmacy distribution map comparing urban access, rural mail‑order and telehealth e‑script services.
A dosing ladder shows 10/20/40/80 mg with typical LDL‑lowering expectations and monitoring checkpoints at 6–12 weeks.
A safety checklist highlights when to check LFT/CK and red‑flag symptoms, with clear calls to action to consult a GP or pharmacist and to report adverse events to the national authority.
Storage & Transport
Household Storage Under Australian Climate
How Should Patients Store Tablets At Home?
Store tablets at room temperature, ideally between 20–25°C and away from moisture, heat and direct sunlight.
Advise patients not to leave blister packs in parked cars or in direct sun during Australian summers.
Keep medications out of reach of children and retain original packaging and expiry dates.
Cold‑Chain Logistics For Pharmacies
Do Pharmacies Need Special Handling For Atorvastatin?
No cold‑chain is required for atorvastatin, but standard transport guidelines should avoid exposure to extremes of temperature.
Regional repackaging by authorised manufacturers is common; pharmacies must ensure packaging integrity during mail‑order and long‑distance transport.
For remote patients, pharmacists can plan PBS supply continuity to prevent lapses in therapy.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
How Should Pharmacists Talk To Patients About Atorvastatin?
Begin by outlining the benefits in terms of absolute cardiovascular risk reduction for that individual.
Discuss common and rare side effects, interaction checks (notably CYP3A4 inhibitors), alcohol guidance and pregnancy contraindication.
Use teach‑back to confirm dosing, monitoring schedules and what to do for missed doses.
Emphasise when urgent care is required, such as dark urine or severe unexplained muscle pain.
National Health Authority Recommendations
Which National Guidance Should Be Followed?
Follow national guidelines for cholesterol management, TGA safety communications and PBAC recommendations on PBS usage.
Collaborate closely with GPs and specialists for decisions about dose intensity, combination therapy or specialist referral when intolerance or insufficient LDL reduction occurs.
Pharmacists are pivotal for continuity of care, particularly where PBS rules and rural access complicate treatment.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
Concluding Notes For Australian Patients
How To Decide If Atorvachol Is Right For You?
Discuss cardiovascular risk, LDL targets and possible drug interactions with your GP or pharmacist before starting therapy.
Adherence to therapy and regular testing at 6–12 weeks are essential to get the full protective benefit against heart attack and stroke.
Report any unexplained muscle pain or signs of liver dysfunction promptly so tests and adjustments can be made.
Pharmacists can help with PBS eligibility checks, brand substitution questions and arranging repeat supplies, including telehealth and mail‑order options where available.
Atorvastatin (atorvachol) is a proven and flexible option for lowering LDL‑C when used with appropriate monitoring and counselling.