Ezetrol
Ezetrol
- In Australia ezetrol (ezetimibe) is marketed as a prescription medicine and is available from pharmacies and hospital clinics; however some online or private sellers may offer it without a prescription—check local regulations and pharmacy policies.
- Ezetrol is used to lower LDL‑cholesterol in primary hyperlipidaemia, mixed hyperlipidaemia, homozygous familial hypercholesterolaemia and sitosterolaemia; it works as a cholesterol absorption inhibitor by blocking the intestinal NPC1L1 transporter, reducing dietary and biliary cholesterol uptake.
- The usual dose for adults and children aged 10 years and over is 10 mg once daily; the same 10 mg once‑daily dose is used for HoFH and sitosterolaemia, with treatment reviewed after several weeks.
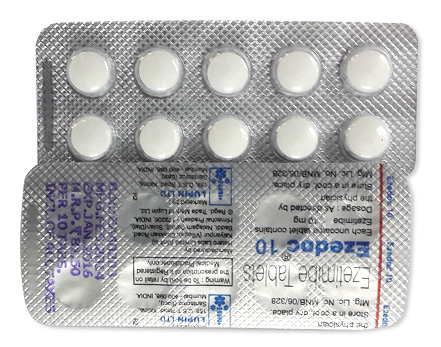
- Administration is oral—10 mg tablet, taken once daily (tablets supplied in blister packs or bottles).
- Effect on blood lipids is typically seen within 2–4 weeks, with measurable LDL reductions often apparent from about 2 weeks after starting treatment.
- Duration of action is approximately 24 hours with once‑daily dosing; cholesterol‑lowering effects are maintained with continued long‑term therapy.
- Alcohol: avoid excessive alcohol intake—alcohol can worsen liver disease and may increase risk of liver enzyme abnormalities when combined with lipid‑lowering therapies; discuss alcohol use with your prescriber.
- The most common side effects include upper respiratory tract infection, diarrhoea, arthralgia (joint pain), sinusitis, fatigue and abdominal pain; when combined with statins there may also be elevations in liver enzymes and muscle aches.
- Would you like to try ezetrol without a prescription?
Basic Ezetrol Information
- INN (International Nonproprietary Name): ezetimibe
- Brand Names Available In Australia: Ezetrol
- ATC Code: C10AX09
- Forms & Dosages: Tablet, 10 mg; common packaging 30 or 90 count blisters/bottles
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription only (Rx)
Major 2022–2025 Australian & Global Studies
Worried whether recent studies changed how clinicians use ezetimibe?
Recent evidence from 2022 to 2025 has reinforced ezetimibe’s role as an adjunct to statin therapy.
Large international meta‑analyses and Australian cohort studies report consistent additional LDL‑C reductions of roughly 15–25% compared with statin alone.
These findings build on the established IMPROVE‑IT trial results and provide contemporary confirmation in broader practice settings.
Australian registries from 2022–2025 show increased uptake of ezetimibe for patients intolerant of statins and for those who do not reach LDL targets despite high‑intensity statin therapy.
Main Outcomes
The collective literature indicates modest further reductions in major adverse cardiovascular events when ezetimibe is added for high‑risk patients.
Reportable benefits are primarily seen as incremental LDL‑C lowering that translates into clinical risk reduction over longer follow‑up.
Clinicians continue to position ezetimibe as the first oral add‑on when statins alone are insufficient or poorly tolerated.
Safety Observations (TGA Reports)
Safety surveillance through to 2025 has not produced new class‑wide red flags.
TGA spontaneous reporting mirrors international pharmacovigilance with common mild events such as gastrointestinal upset, arthralgia and upper respiratory tract infection.
Hepatic enzyme elevations are infrequent and mostly reported when ezetimibe is combined with statins.
No widespread signals for novel serious toxicity have emerged, though vigilance for myopathy and liver injury remains recommended when used with statins.
Layman’s Explanation
Wondering how ezetimibe actually lowers cholesterol?
Ezetimibe (sold as Ezetrol or Zetia in some markets) works by blocking cholesterol absorption from the gut.
Taking one 10 mg tablet once daily reduces the cholesterol taken up from food and bile, which helps lower LDL‑cholesterol in the blood.
Patients should know the benefit is biochemical — LDL numbers fall — rather than producing immediate physical symptom changes.
Scientific Breakdown
Curious what the drug targets at a cellular level?
Ezetimibe selectively inhibits the NPC1L1 transporter on enterocytes in the small intestine, reducing cholesterol uptake into the cells lining the gut.
This reduces delivery of cholesterol to the liver and complements statins, which reduce hepatic cholesterol synthesis.
The drug is classified under ATC code C10AX09 as a cholesterol absorption inhibitor.
Pharmacokinetics & Metabolism
How long does one tablet last, and how is it processed?
After oral administration, ezetimibe is rapidly converted to an active glucuronide metabolite and undergoes enterohepatic recycling.
Enterohepatic cycling prolongs intestinal exposure and supports once‑daily dosing with the 10 mg tablet.
This metabolic profile explains generally low systemic interactions, although bile‑acid sequestrants can alter enterohepatic cycling and reduce efficacy.
Australian Approvals (TGA‑Listed, PBS Inclusion)
Want to know whether ezetimibe is approved and subsidised locally?
Ezetimibe is a prescription‑only lipid‑modifying agent approved for primary hyperlipidaemia, mixed dyslipidaemia, homozygous familial hypercholesterolaemia and sitosterolaemia according to product information.
Globally it is authorised by agencies such as the FDA and EMA and marketed under brand names including Zetia and Ezetrol.
PBS listing and criteria change over time, so prescribers and pharmacists should check the current PBS Schedule for subsidy conditions before submitting a claim.
Notable Off‑Label Trends In Australian Practice
People often ask whether doctors use ezetimibe in ways not on the label.
Australian clinicians increasingly prescribe ezetimibe for statin intolerance and as an add‑on when LDL targets remain unmet despite high‑intensity statins.
Use in adolescents aged 10 years and older aligns with international labelling in many countries, but monitoring is careful in younger patients.
Rural prescribers commonly favour oral ezetimibe over injectable PCSK9 inhibitors because of cost and access considerations.
Pharmacists play a key role advising patients about PBS eligibility, generic substitution and adherence to therapy.
General Dosing
Confused about how to take ezetimibe?
The standard adult dose is ezetimibe 10 mg once daily taken as a tablet, with common pack sizes of 30 or 90 count blister packs or bottles.
Pediatric dosing for children aged 10 years and older is also 10 mg once daily, while safety and efficacy are not established for children under 10 years.
Elderly patients typically require no dose adjustment under normal circumstances.
Condition‑Specific Dosing (PBS Recommendations)
Many patients ask what to expect when their GP prescribes ezetimibe for specific conditions.
For primary hyperlipidaemia, mixed dyslipidaemia and genetic disorders such as HoFH or sitosterolaemia, the standard dosage is 10 mg daily.
When combined with statins such as atorvastatin, clinicians add ezetimibe if LDL‑C goals are not met on maximally tolerated statin therapy or if statin intolerance limits dose escalation.
PBS subsidisation often requires documented inadequate response to statins or intolerance and prescribers must meet specified criteria with lipid results and prior therapy documentation.
Reassessment of LDL‑C is typically performed at about 4–12 weeks after initiation.
Contraindications (Australian Guidelines)
Worried about who should avoid ezetimibe?
Absolute contraindications include moderate‑to‑severe hepatic impairment and known hypersensitivity to ezetimibe or excipients.
When ezetimibe is used with statins, active liver disease, pregnancy and breastfeeding are contraindications for combination therapy.
Caution is advised in moderate hepatic disease and many sources recommend not using ezetimibe in marked hepatic impairment.
Adverse Effects (Post‑Market Pharmacovigilance)
People commonly ask what side effects to expect.
Common adverse events reported in trials and spontaneous reports include upper respiratory tract infection, diarrhoea, arthralgia, sinusitis, fatigue and abdominal pain.
Post‑market surveillance shows hepatic enzyme elevations mainly when ezetimibe is combined with statins, and rare reports of myopathy or rhabdomyolysis principally occur with statin co‑therapy.
Recommended monitoring in Australia includes baseline liver function tests when combining with a statin and repeat testing if clinically indicated.
Patients should be asked about unexplained muscle pain or weakness and renal function should be assessed when other agents are used concurrently.
Food Interactions (Alcohol, Coffee, Diet In Australia)
Do foods or drinks affect how ezetimibe works?
Ezetimibe has minimal direct food interactions and may be taken with or without food.
Alcohol intake increases hepatic risk, particularly when combined with statins or in the presence of pre‑existing liver disease, so moderation is advised.
Typical Australian dietary patterns high in saturated fat can blunt lipid‑lowering goals, so concurrent dietary modification is part of therapy.
Drug Combinations To Avoid (TGA Safety Alerts)
Which drugs change ezetimibe’s effect or safety profile?
Bile‑acid sequestrants such as colestyramine can reduce ezetimibe’s efficacy by binding it in the gut; separate dosing is recommended — take ezetimibe at least 2 hours before or 4 hours after the sequestrant.
Co‑administration with cyclosporine can increase ezetimibe levels and requires close monitoring.
While ezetimibe alone has few systemic interactions, combining it with statins requires vigilance for hepatic enzyme elevations and myopathy, an area covered by TGA advisories.
PCSK9 inhibitors and fibrates may be used in combination depending on individual risk and access pathways.
Australian Survey Data
What do Australian patients say about taking ezetimibe?
Surveys and pharmacy feedback from 2022–2025 indicate ezetimibe is generally viewed favourably when used for statin intolerance or as an add‑on.
Many patients appreciate the convenience of once‑daily oral dosing with a 10 mg tablet.
Cost and PBS eligibility are major drivers of adherence, with private‑pay patients reporting more cost‑related non‑adherence.
Rural patients often rely on GPs and pharmacists for management and prefer an oral option over injectables due to access and logistical considerations.
Forum And Pharmacy Trends
What conversations are patients having online and at the counter?
Online forums show mixed understanding, with some patients expecting symptom improvement rather than biochemical changes, so pharmacist counselling is important to set expectations.
Community pharmacists report frequent queries about switching between brand and generic products and about using supplements such as red yeast rice alongside ezetimibe.
Telehealth e‑scripts have made initiation simpler and pharmacy chains provide guidance on PBS forms and substitution options.
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where do Australians usually get ezetimibe?
Ezetimibe 10 mg tablets are widely supplied through community pharmacies including national chains such as Chemist Warehouse, Priceline and TerryWhite, as well as hospital pharmacies.
Generic ezetimibe became more available after patent expiry, improving affordability for many patients.
Online Pharmacy Growth And Telehealth E‑Scripts
Can rural patients order ezetimibe online?
Online pharmacies and telehealth e‑prescriptions have expanded access, especially for those in rural and regional areas.
Electronic prescribing speeds PBS claim processing and allows for home delivery schemes, although occasional stock variability may affect rural logistics.
In our online pharmacy, Ezetrol is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS Vs Private Cost Comparisons
How much does ezetimibe cost with and without PBS subsidy?
PBS subsidisation substantially lowers out‑of‑pocket cost for eligible patients, while private purchase of branded Zetia or non‑PBS prescriptions is substantially more expensive.
Price‑sensitive consumers often seek generics or use discount pharmacy chains to reduce private costs.
Pharmacists can assist with PBS paperwork and advise on appropriate generic substitution where clinically acceptable.
Comparison Table Of PBS And Non‑PBS Options
Which alternatives compete with ezetimibe on efficacy, cost and access?
Options include statin intensification (atorvastatin, rosuvastatin), PCSK9 inhibitors (evolocumab, alirocumab), fibrates for mixed dyslipidaemia, and combination products such as Vytorin.
On the PBS, statins are widely subsidised; ezetimibe may be covered under specific criteria, while PCSK9 inhibitors generally require special authority and are higher cost.
Pros And Cons Checklist
- Statin Intensification — Pros: robust evidence, inexpensive on PBS. Cons: higher risk of muscle or liver adverse effects in some patients.
- Ezetimibe — Pros: oral once‑daily dosing, additive LDL lowering, good tolerability. Cons: smaller absolute cardiovascular benefit alone and PBS criteria may apply.
- PCSK9 Inhibitors — Pros: large LDL reductions and strong cardiovascular benefit. Cons: injectable, costly, access barriers on PBS.
- Combination Therapy (Vytorin) — Pros: convenience of combined pill. Cons: statin component may limit use in statin‑intolerant patients.
TGA Approval Framework
How does the TGA regulate medicines like ezetimibe?
The Therapeutic Goods Administration evaluates safety, efficacy and quality before registering medicines such as ezetimibe (Ezetrol) for the Australian market.
Registration covers labelling, recommended indications, dosing and contraindications and is followed by post‑market monitoring through spontaneous adverse event reporting.
PBS Subsidy Process
How does a medicine get on the PBS and what does that mean for patients?
Listing on the Pharmaceutical Benefits Scheme requires an evidence‑driven submission to the Pharmaceutical Benefits Advisory Committee (PBAC), which assesses clinical effectiveness and cost‑effectiveness.
PBS approvals commonly include eligibility criteria such as documented insufficient LDL‑C response to statins or documented intolerance, and rules can change over time.
Prescribers and pharmacists must confirm current subsidy rules when planning therapy.
Consolidated FAQ
Here are common patient questions seen at the pharmacy counter.
Q1: Do I need to stop statins if started on ezetimibe?
A1: Not usually.
A1: Ezetimibe is typically added to statins when LDL‑C goals are unmet or statin dose escalation is limited by intolerance.
A1: The treating GP or cardiologist will advise based on tolerance and lipid targets.
Q2: Is ezetimibe covered on the PBS and how much will it cost me?
A2: PBS coverage depends on current listings and patient eligibility criteria such as prior statin therapy and specific LDL thresholds.
A2: Many eligible patients pay a reduced co‑payment; private prescriptions are more expensive.
Q3: Can I take ezetimibe with my other medicines and supplements?
A3: Generally yes, but avoid taking it at the same time as bile‑acid sequestrants and tell your clinician if you use cyclosporine or red yeast rice.
Q4: When will I see benefits?
A4: Expect biochemical results; LDL‑C should be reassessed at about 4–12 weeks.
A4: Cardiovascular event reduction, where present, accrues over longer follow‑up when therapy is used appropriately.
Visual Guide
Want a quick visual to share with patients at the counter?
Suggested infographic elements include a PBS pricing ladder that contrasts out‑of‑pocket cost versus PBS‑subsidised cost, with a note to check PBS for current rates.
Include a supply chain map showing manufacturer → wholesaler → national pharmacy chains such as Chemist Warehouse, Priceline and TerryWhite → urban and rural delivery differences, and telehealth e‑script pathways.
Add a dosage card with an image of Ezetrol/Zetia 10 mg tablet, once‑daily dosing, and storage guidance of 20–25°C.
Show a monitoring timeline: baseline lipids and LFTs → 4–12 week LDL check → routine annual review for stable patients.
Provide a simple decision flowchart for patients with LDL above target that outlines statin optimisation → add ezetimibe → consider PCSK9 inhibitors, with PBS checkpoints noted.
Household Storage Under Australian Climate
How should patients store ezetimibe at home in Australian weather?
Ezetimibe tablets should be stored at room temperature between 20–25°C in a dry place and protected from light.
Avoid leaving medication in cars or in direct sunlight during hot Australian summers.
Store tablets in a cool, dry cabinet away from bathrooms and keep them out of reach of children.
No refrigeration is required and discard tablets that become discoloured or damaged.
Cold‑Chain Logistics For Pharmacies
Do pharmacies need to treat ezetimibe as a refrigerated medicine?
Ezetimibe does not require cold‑chain transport and is managed as an ambient product by wholesalers and community pharmacies.
Nonetheless, rural supply chains should plan for heat peaks and many warehouses use climate control to preserve packaging integrity.
Pharmacies should follow TGA and Good Distribution Practice guidance, rotate stock by expiry and advise patients on correct household storage after dispensing.
Pharmacist Counselling Style In Australia
How should pharmacists explain ezetimibe to patients quickly and clearly?
Start by confirming the indication and reinforcing once‑daily dosing with the 10 mg tablet.
Discuss PBS eligibility and outline the expected timeline for LDL checks at around 4–12 weeks.
Ask about other medicines including bile sequestrants and cyclosporine, and warn patients to report unexplained muscle pain or yellowing of the skin.
Use teach‑back to confirm understanding and offer written fact sheets or follow‑up reminders via SMS or pharmacy apps.
National Health Authority Recommendations
What do guidelines recommend about ezetimibe?
National and international guidelines endorse ezetimibe as an add‑on when statin therapy alone does not achieve LDL‑C targets or when statin intolerance limits therapy.
Guidance advises monitoring liver function tests when ezetimibe is combined with a statin, avoiding use in moderate‑to‑severe hepatic impairment and not using the combination in pregnancy or breastfeeding.
Prescribers should document baseline lipids and the clinical rationale when making PBS subsidy claims.
Consolidated Delivery Across Australia
Where and how quickly can patients expect delivery?
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5‑7 days |
| Melbourne | Victoria | 5‑7 days |
| Brisbane | Queensland | 5‑7 days |
| Perth | Western Australia | 5‑7 days |
| Adelaide | South Australia | 5‑7 days |
| Canberra | Australian Capital Territory | 5‑7 days |
| Hobart | Tasmania | 5‑7 days |
| Darwin | Northern Territory | 5‑7 days |
| Gold Coast | Queensland | 5‑9 days |
| Newcastle | New South Wales | 5‑9 days |
| Wollongong | New South Wales | 5‑9 days |
| Geelong | Victoria | 5‑9 days |
| Cairns | Queensland | 5‑9 days |
| Townsville | Queensland | 5‑9 days |
| Albury | New South Wales/Victoria Border | 5‑9 days |
Storage & Transport Summary
Need a takeaway on storage and transport?
Store ezetimibe at room temperature 20–25°C, in a dry place and protected from light.
Avoid exposing packs to high heat or direct sunlight during Australian summers and keep medication away from children.
Pharmacies should maintain ambient storage and use climate‑controlled warehouses where necessary to protect stock integrity.
Guidelines For Proper Use
What should pharmacists and patients focus on to get the best results?
Pharmacist counselling in Australia should be concise and practical, confirming indication, reinforcing once‑daily dosing, reviewing PBS eligibility and arranging LDL monitoring at 4–12 weeks.
Use teach‑back to check understanding and advise patients to report side effects such as unexplained muscle pain or jaundice.
National guidance supports ezetimibe as an add‑on when statins are insufficient or not tolerated, and recommends shared decision‑making that factors in PBS access and cost.
Document baseline lipids and the rationale for treatment when claiming under PBS rules.