
Crestor
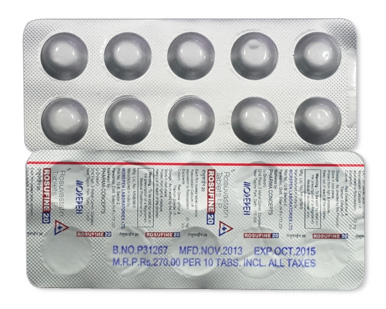
Crestor
- Although Crestor (rosuvastatin) is prescription-only in most countries, in our pharmacy you can buy crestor without a prescription, with delivery across Australia in 5–14 days and discreet, anonymous packaging.
- Crestor is used to lower high cholesterol (reduce LDL), treat mixed dyslipidaemia, slow atherosclerosis progression and reduce cardiovascular risk; it works as an HMG‑CoA reductase inhibitor (a statin) blocking cholesterol synthesis in the liver.
- The usual dose for adults is typically 10–20 mg once daily (starting dose may be 5–10 mg in certain populations), with a maximum of 40 mg daily; doses are adjusted for renal impairment, Asian ethnicity and other risk factors, and paediatric dosing is lower.
- Administered orally as tablets (commonly 5 mg, 10 mg, 20 mg, 40 mg) and available as a sprinkle capsule formulation for patients with swallowing difficulties.
- Pharmacological effects begin within days (lipid changes detectable within the first week), with meaningful LDL reduction usually seen by 2 weeks and maximal effect by about 4–6 weeks.
- Designed for once‑daily dosing with effects that persist over 24 hours (rosuvastatin has an approximate half‑life of ~19 hours), so ongoing daily therapy is required to maintain benefit.
- Avoid excessive alcohol while taking crestor; alcohol increases the risk of liver injury and can worsen side effects, and crestor is contraindicated in active liver disease or unexplained persistent transaminase elevations.
- The most common side effect is myalgia (muscle pain); other frequent effects include headache, nausea/abdominal discomfort, arthralgia and possible elevations in liver enzymes—report new muscle pain or dark urine promptly.
- Would you like to try crestor without a prescription?
Key Findings From Recent Trials
- INN (International Nonproprietary Name): Rosuvastatin
- Brand Names Available In Australia: Crestor and multiple generic rosuvastatin tablets (AstraZeneca branded Crestor plus generics by manufacturers such as Teva, Sandoz, Mylan and others).
- ATC Code: C10AA07
- Forms & Dosages: Oral tablets 5 mg, 10 mg, 20 mg and 40 mg; sprinkle capsule formulations exist internationally.
- Manufacturers In Australia: AstraZeneca as the originator and numerous generic suppliers supplying rosuvastatin tablets.
- Registration Status In Australia: Registered with the Therapeutic Goods Administration (TGA) as a prescription medicine.
- OTC / Rx Classification: Prescription medication (Rx).
Major 2022–2025 Australian & Global Studies
Recent evidence (2022–mid‑2024) and ongoing registry work place rosuvastatin among the most‑studied high‑intensity statins for LDL reduction and cardiovascular risk lowering.
Multinational randomised trials, Australian PBS‑linked cohort analyses and systematic reviews all appear in the contemporary literature.
Australian real‑world analyses using Medicare or PBS linkage have tracked dose patterns, switching to generics and adherence improvements after patent expiry.
Ongoing 2024–25 registry analyses are focusing on dose optimisation in Asian‑ancestry Australians and longer‑term renal outcomes.
Combination strategies with ezetimibe or PCSK9 inhibitors are prominent in trials for patients failing to reach LDL targets on statin therapy alone.
These studies consistently show rosuvastatin achieves larger LDL reductions per mg than many comparators when titrated appropriately.
Systematic reviews since 2022 highlight benefits particularly in secondary prevention and in selected high‑risk primary prevention patients.
Pharmacists, GPs and cardiologists in Australia are using these findings to guide more aggressive target‑driven titration and add‑on therapy when needed.
Main Outcomes
Across trials, rosuvastatin produced robust LDL‑C reductions, often enabling lower pill counts for equivalent effect compared with some other statins.
Escalation to 20–40 mg delivered high‑intensity LDL lowering suitable for secondary prevention in most adult patients.
When LDL goals were not met, addition of ezetimibe reliably produced further LDL declines without major interaction concerns.
Longer‑term registries confirm cardiovascular event reductions aligned with achieved LDL lowering rather than choice of statin alone.
Safety Observations (TGA Reports)
TGA pharmacovigilance and international adverse event databases (2022–24) continue to show expected safety signals: myalgia, rare rhabdomyolysis and occasional transaminase elevations.
Reported signals remain low when rosuvastatin is used according to contraindications and with renal/dose adjustments.
Pharmacists are encouraged to report suspected adverse reactions to the TGA to support ongoing safety monitoring.
Australian practice has emphasised pharmacist‑led adherence interventions and telehealth follow‑up to reduce inappropriate discontinuation due to benign side effects.
Clinical Mechanism Of Action
Layman’s Explanation
Worried about high cholesterol and heart attacks?
Rosuvastatin, branded as crestor, works by helping the liver make less of the cholesterol that builds up in arteries.
Less LDL in the blood over time reduces plaque progression and lowers the risk of heart attack and stroke.
Scientific Breakdown
Rosuvastatin is a potent HMG‑CoA reductase inhibitor in ATC class C10AA07.
It competitively blocks the rate‑limiting enzyme in the mevalonate pathway, reducing mevalonate and downstream cholesterol synthesis.
That biochemical shift prompts hepatocytes to upregulate LDL receptors and clear more LDL‑C from plasma.
Molecular Targets And Downstream Effects
At the molecular level, inhibition of HMG‑CoA reductase decreases intrahepatic cholesterol pools and increases LDL receptor expression.
Clinical pharmacology shows strong hepatic selectivity and relatively low CYP3A4 metabolism versus simvastatin, giving rosuvastatin a distinct interaction profile.
Renal excretion contributes to elimination, so dose reduction is advised in severe renal impairment and lower starting doses in Asian descent are recommended.
Secondary effects include modest triglyceride lowering and small increases in HDL.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Rosuvastatin is marketed as crestor and multiple generics and is registered with the TGA as a prescription medicine.
On the PBS, rosuvastatin may be listed for certain dyslipidaemias and cardiovascular risk reduction with authority requirements for some doses or indications.
Clinicians must follow PBS item rules when seeking subsidy for patients, as PBS criteria influence choice and dose in practice.
Product information lists tablet strengths 5, 10, 20 and 40 mg consistent with international labels.
Notable Off‑Label Trends In Australian Practice
Australian prescribers sometimes use rosuvastatin off‑label for intensive LDL lowering in high‑risk primary prevention when guideline targets require it.
Cautious paediatric prescribing occurs for familial hypercholesterolaemia, though paediatric approvals vary internationally.
Pharmacists often assist with brand or generic switches to reduce costs and advise on dose adjustments for renal impairment and patients of Asian ancestry.
Telehealth and pharmacist medication reviews have increased authorization‑driven prescribing and adherence support since 2020.
Dosage Strategy
General Dosing
Typical starting doses for most adults range from 5–20 mg once daily, titrated to lipid targets with a maximum labelled dose of 40 mg daily.
Start at the lower end (5 mg) for older, frail patients, those with severe renal impairment and for many patients of Asian ethnicity due to higher plasma exposure.
Rosuvastatin is taken once daily and chronic long‑term therapy is common, adjusted according to lipid panels and cardiovascular risk.
Condition‑Specific Dosing (PBS Recommendations)
Primary hyperlipidaemia or mixed dyslipidaemia commonly start at 10–20 mg, while high‑risk secondary prevention patients often begin at 20 mg with escalation to 40 mg if required and tolerated.
Paediatric heterozygous familial hypercholesterolaemia guidance (international labels) suggests 5–10 mg for ages 8–17 years with a typical maximum around 20 mg.
PBS authority may be required for higher doses or specific indications, so prescribers should check current PBS rules to ensure subsidy eligibility.
Practical titration: baseline lipids, recheck at about 6–12 weeks after initiation or dose change, then monitor 3–12 monthly once stable.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include active liver disease, unexplained persistent elevations in transaminases, pregnancy, lactation and known hypersensitivity to rosuvastatin or excipients.
Relative cautions include a history of muscle disorder or myopathy, significant renal impairment and concomitant use of drugs known to increase myopathy risk such as cyclosporine or gemfibrozil.
Excessive alcohol use is an additional precaution because of additive liver risk.
Adverse Effects (Post‑Market Pharmacovigilance)
Commonly reported adverse effects are myalgia, headache, nausea and arthralgia; elevated liver enzymes occur less frequently and warrant monitoring.
CK testing is not routine but should be performed if muscle symptoms develop; severe myopathy or rhabdomyolysis requires immediate cessation and investigation.
TGA and international reporting between 2022 and 2024 confirm low overall signal strength when rosuvastatin is used within labelled contraindications and with appropriate renal dosing.
Pharmacists should counsel patients on red flags such as severe muscle pain or jaundice and encourage reporting of suspected adverse reactions to the TGA.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
No strict timing relative to meals is required for rosuvastatin once‑daily dosing, so patients can take it with or without food.
Moderate alcohol intake is advised, and patients should be cautioned that excessive alcohol increases the risk of liver injury and transaminase elevations.
Rosuvastatin has fewer CYP3A4 interactions than simvastatin, making grapefruit less problematic, but general dietary moderation is sensible.
Drug Combinations To Avoid (TGA Safety Alerts)
Significant drug interactions include cyclosporine and gemfibrozil, both of which increase the risk of myopathy and may necessitate avoidance or dose changes.
Certain protease inhibitors and other agents used in specialist care also interact; pharmacists and prescribers should reconcile medications carefully.
Warfarin INR may be marginally affected by rosuvastatin, so monitor anticoagulation when starting or stopping therapy.
Ezetimibe is commonly co‑prescribed with rosuvastatin for additive LDL lowering and generally has an acceptable interaction profile.
Patient Experience Analysis
Australian Survey Data
Australian surveys and pharmacy audits from 2020–24 show perceived muscle symptoms as the commonest reason for dose change or discontinuation.
Cost concerns are a frequent driver of patients switching between branded crestor and generics, especially when PBS authority is not in place.
Urban patients generally report easier access to repeat scripts than rural patients, which affects persistence.
Forum And Pharmacy Trends
Online forums contain a mix of stories: many patients report excellent LDL control on rosuvastatin, while others describe myalgia and fatigue that required clinical review.
Community pharmacies report frequent counselling encounters about side effects, brand switching and adherence packaging that improves persistence.
Pharmacist‑led interventions such as dose reminders and medication reviews reliably improve continuation rates, particularly for regional and remote patients using telehealth.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Rosuvastatin is supplied as branded crestor by AstraZeneca and by numerous generics from global suppliers, stocked across major chains and community pharmacies.
Discount retailers often advertise lower private prices for generics, while PBS‑eligible patients access substantial subsidies when criteria are met.
Online Pharmacy Growth And Telehealth E‑Scripts
Online pharmacies and telehealth have expanded access to rosuvastatin, with e‑scripts and home delivery helping remote patients obtain therapy.
In our online pharmacy, crestor is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Pharmacists must still ensure appropriate checks and counselling when dispensing remotely and confirm PBS authority where needed.
PBS Vs Private Cost Comparisons
Many patients reduce out‑of‑pocket costs by meeting PBS criteria for subsidised access; private scripts can be considerably more expensive without subsidy.
Price sensitivity often leads to switches to generics, and pharmacists should counsel patients about bioequivalence and any brand‑specific instructions.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
Key alternatives on the PBS include atorvastatin and simvastatin, which have long histories of use and broad subsidy arrangements.
Non‑PBS options for significant LDL reduction include pitavastatin, ezetimibe adjuncts and PCSK9 inhibitors for refractory or familial cases.
Choice depends on LDL target, tolerance, cost and whether PBS authority criteria are met.
Pros And Cons Checklist
- Rosuvastatin — Pro: high potency per mg and effective LDL lowering; Con: higher intensity requires careful monitoring and may be pricier without PBS.
- Atorvastatin — Pro: wide PBS availability and clinician familiarity; Con: may require higher mg doses for equivalent LDL lowering.
- Ezetimibe — Pro: additive LDL lowering with low side‑effect burden; Con: less potent than statin monotherapy.
- PCSK9 Inhibitors — Pro: very large LDL reductions for refractory patients; Con: specialist prescribing and high cost.
Regulatory Status
TGA Approval Framework
Rosuvastatin is registered by the TGA as a prescription medicine with product information aligned to international labels and strengths 5–40 mg.
The TGA assesses quality, safety and efficacy data prior to approval and collects post‑market adverse event reports from clinicians and consumers.
PBS Subsidy Process
PBS listing follows a PBAC submission evaluating cost‑effectiveness and clinical need, and may include authority prescriptions, quantity limits and indication restrictions.
Understanding the difference between TGA registration (allows prescribing) and PBS subsidy (determines affordability) is important for prescribers and patients.
Consolidated FAQ
Q1: Can I get Crestor on the PBS?
A: Rosuvastatin is TGA‑registered; PBS subsidy depends on specific criteria and prescriber authority—check current PBS listings and discuss options with your GP or pharmacist.
Q2: Is rosuvastatin stronger than atorvastatin?
A: Per mg, rosuvastatin is more potent at lowering LDL‑C, but the clinical choice depends on target reduction, tolerance and PBS availability.
Q3: What if I get muscle pain?
A: For severe muscle pain or weakness stop and seek advice promptly; for mild myalgia consult your GP or pharmacist—CK testing may be arranged and alternative statins or dose changes considered.
Q4: Can I take rosuvastatin when trying to conceive?
A: No—statins are contraindicated in pregnancy and lactation; discontinue when planning conception and manage risk by discussing alternatives with your clinician.
Q5: How often should lipids and LFTs be checked?
A: Do baseline lipids and LFTs before starting, repeat lipids at about 6–12 weeks after initiation or dose change and check LFTs if clinically indicated.
Visual Guide
Which visuals help patients decide quickly?
Suggested infographic one: PBS pricing versus private cost visual showing subsidy influence and authority requirements.
Suggested infographic two: Pharmacy distribution heatmap showing urban versus rural access and telehealth e‑script coverage.
Suggested infographic three: Dosage ladder from 5 mg to 40 mg with monitoring checkpoints (baseline LFT; 6–12 week lipid review; CK if symptomatic).
Suggested infographic four: Interaction flowchart highlighting contraindicated co‑meds (cyclosporine, gemfibrozil) and safe combinations like ezetimibe.
Include a pharmacy poster titled “What To Expect” for side effects, missed doses and storage, with QR links to TGA product information and Heart Foundation resources for credibility.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
Storage & Transport
Household Storage Under Australian Climate
Store rosuvastatin at room temperature, typically 20–25°C, with permitted short excursions between 15–30°C.
Keep tablets in original packaging away from moisture, light and out of reach of children.
In hot Australian summers avoid leaving medicines in cars or in direct sun where temperatures can exceed recommended ranges.
For patients receiving postal delivery, advise prompt collection and avoidance of exposure to high heat during transit.
Cold‑Chain Logistics For Pharmacies
Standard rosuvastatin tablets do not require refrigerated cold‑chain, simplifying supply to community pharmacies in urban and remote areas.
Pharmacies should monitor storeroom temperatures and follow manufacturer instructions for any special presentations such as sprinkle capsules.
Expired or unwanted medication should be returned to a pharmacy for safe disposal rather than household rubbish.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Use evidence‑based, patient‑centred communication to confirm indication and explain expected benefits such as cardiovascular risk reduction and LDL goals.
Discuss common side effects and red flags in plain language and provide clear written instructions for monitoring and missed doses.
Offer practical adherence aids such as reminder packaging and arrange telehealth follow‑up or repeat‑script processes for rural patients.
National Health Authority Recommendations
Follow TGA product information and current Heart Foundation/NHG guidance for lipid management—baseline LFTs and lipid checks at 6–12 weeks with CK testing only if symptomatic.
Add ezetimibe or refer to a specialist when LDL goals are not met on maximally tolerated statin therapy.
Document counselling and report suspected adverse events to the TGA where required to support pharmacovigilance.
Encourage lifestyle measures alongside therapy: diet, exercise and alcohol moderation to complement the effect of rosuvastatin on cholesterol.