Conjugated Estrogens
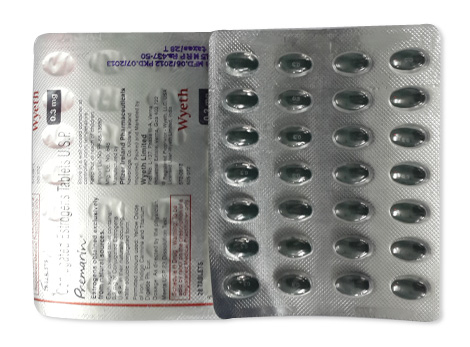
Conjugated Estrogens
- In our pharmacy you can buy conjugated estrogens without a prescription, with discreet packaging and delivery across Australia in 3–14 days; note that in many countries conjugated estrogens are normally prescription-only and you should check local regulations.
- Conjugated estrogens are used for relief of menopausal vasomotor symptoms, treatment of vaginal atrophy, hypo‑oestrogenism (eg. ovarian failure) and prevention of postmenopausal osteoporosis; they are a mixture of oestrogenic steroids (eg. estrone sulphates, equilin sulfates) that act as oestrogen receptor agonists to restore oestrogen effects on the uterus, breast, bone and urogenital tissues.
- Usual oral starting doses for menopausal symptoms are 0.3–0.625 mg once daily, titrated to the lowest effective dose (maintenance up to 1.25–2.5 mg); vaginal cream dosing is typically 0.5–2 g per application (equivalent to about 0.3–1.25 mg oestrogen) with initial daily use then intermittent maintenance.
- Available forms include oral tablets (0.3, 0.625, 0.9, 1.25, 2.5 mg), vaginal cream (0.625 mg/g in 27–28 g tubes), occasionally injections and combination tablets with progestogens.
- Some symptom relief (particularly for hot flushes) may be noticed within days to 1–2 weeks, with maximal benefit often seen by 4–6 weeks; vaginal symptoms may begin to improve within 1–2 weeks with topical therapy.
- Duration of action is effectively daily (therapy is usually given once daily); clinical effects persist only while treatment continues and long‑term benefits (eg. bone protection) accrue with ongoing use under medical supervision.
- Avoid heavy alcohol consumption while using oestrogens; excessive alcohol increases liver risk and can worsen vascular risk factors — discuss alcohol use with your clinician before starting therapy.
- The most common side effects are breast tenderness or pain, headache, nausea, bloating/abdominal cramps and vaginal spotting or discharge; less commonly oedema, mood changes and skin rashes may occur.
- Would you like to try conjugated estrogens without a prescription?
Basic Conjugated Estrogens Information
- INN (International Nonproprietary Name): Conjugated estrogens (also referenced as conjugated equine estrogens, CEE).
- Brand Names Available In Australia: Premarin®; Premia® (combination products).
- ATC Code: G03CA57.
- Forms & Dosages: Oral tablets 0.3 mg, 0.625 mg, 0.9 mg, 1.25 mg, 2.5 mg; vaginal cream 0.625 mg/g in 27.5 g / 28 g tubes; combination tablets (with medroxyprogesterone or norgestrel); injections rarely used or not marketed in all countries.
- Manufacturers In Australia: Major manufacturer listed is Pfizer (originally Wyeth); generics and licensees available internationally include Teva, Aspen and others — local Australian manufacturer names not specified in the dataset.
- Registration Status In Australia: TGA registered for oral and vaginal routes.
- OTC / Rx Classification: Prescription-only (Rx).
Key Findings From Recent Trials
Worried that hormone therapy will fix symptoms but increase risks?
Recent trial reports and systematic reviews from 2022–2025 prioritise low‑dose menopausal hormone therapy (MHT) for symptom control and urogenital atrophy, with emphasis on individualised treatment plans.
Major 2022–2025 Australian and international cohort and meta‑analyses show clinically meaningful symptom relief at oral conjugated oestrogen doses in the range of 0.3–0.625 mg while suggesting reduced systemic risks when compared with higher doses.
Australian observational data emphasise careful use in older or comorbid patients, and international registries continue to record venous thromboembolism (VTE) and stroke signals that correlate with age, dose and route of oestrogen therapy.
Regulatory safety summaries and TGA periodic safety reviews stress benefit/risk individualisation and regular review while advising the lowest effective dose for the shortest necessary duration.
Major 2022–2025 Australian & Global Studies
Trials and pooled analyses during this period focused on low‑dose conjugated oestrogens (CEE) regimens for vasomotor symptoms and urogenital atrophy.
Results consistently support symptomatic improvement while identifying dose, patient age and administration route as the main modifiers of vascular risk.
These findings reinforce current national guidance to choose the lowest effective dose, monitor regularly and favour local therapy where appropriate.
Main Outcomes
Low‑dose CEE (0.3–0.625 mg tablets) was associated with a clinically meaningful reduction in hot flush frequency and severity in most reports.
Vaginal CEE cream demonstrated strong local efficacy for vaginal dryness and atrophy with substantially lower systemic exposure than oral tablets.
Improvements were reported within weeks for vasomotor symptoms and over months for vaginal epithelium restoration.
Safety Observations (TGA Reports)
TGA and other international agencies continue to highlight the thromboembolic risk associated with systemic oestrogen therapy.
Recommendations focus on using the lowest effective dose, assessing individual risk factors (age, smoking, prior VTE, comorbidities) and scheduling periodic reviews.
Clinical Mechanism Of Action
Wondering how conjugated oestrogens relieve hot flushes and vaginal dryness?
Layman’s Explanation
Conjugated oestrogens are a mixture of oestrogenic compounds—primarily estrone sulphate and equine derivatives—used to replace declining endogenous oestrogen in menopause.
They bind to oestrogen receptors (ERα and ERβ) in the brain, bone, urogenital tract and cardiovascular tissues to reverse symptoms of hypo‑oestrogenism.
Scientific Breakdown
CEEs are complex conjugated sulphate esters that are hydrolysed to active unconjugated oestrogens after absorption.
Hepatic first‑pass metabolism converts a portion of the dose into estrone and estradiol forms and alters circulating ratios, which in turn influences hepatic protein synthesis including coagulation factors and sex hormone binding globulin (SHBG).
Component Profile
Typical CEE preparations contain multiple equine steroid molecules rather than a single 17β‑estradiol molecule, so pharmacodynamics and metabolite patterns differ from estradiol products.
Receptor And Tissue Effects
Oestrogen receptor binding stabilises thermoregulatory mechanisms to reduce vasomotor symptoms, stimulates vaginal epithelium proliferation to relieve atrophy and influences bone remodelling to help preserve bone density.
Those same receptor and hepatic effects partly explain off‑target vascular and hepatic risks associated with systemic therapy.
Scope Of Approved & Off‑Label Use
Not sure whether Premarin is approved for your symptom profile or whether an off‑label use is reasonable?
Australian Approvals (TGA‑Listed, PBS Inclusion)
Premarin® and related conjugated estrogens products are registered with the TGA for menopausal symptoms and urogenital atrophy.
Common pack sizes and strengths mirror international availability: tablets in 0.3 mg, 0.625 mg and 1.25 mg and vaginal cream 0.625 mg/g in 27.5–28 g tubes.
PBS subsidy status varies by formulation and indication, and clinicians should verify current PBS listings and any authority requirements before prescribing.
Notable Off‑Label Trends In Australian Practice
Off‑label use includes specialist regimens for premature ovarian insufficiency and selected palliative oncology contexts where clinical rationale supports use.
Compounding and topical microdosing are used experimentally in some clinics, but these approaches require informed consent and specialist oversight due to limited evidence and regulatory considerations.
Dosage Strategy
How should dosing start and change if symptoms persist or side effects occur?
General Dosing
Contemporary guidance and clinical reports favour the lowest effective dose.
Oral tablet starting doses commonly used are 0.3–0.625 mg once daily, with product packaging frequently offering 0.3 mg, 0.625 mg and 1.25 mg strengths.
Vaginal cream is typically dosed 0.5–2 g (approx. 0.3–1.25 mg equivalent) with intermittent or maintenance regimens for atrophy.
Condition‑Specific Dosing (PBS Recommendations)
Vasomotor Symptoms: Start 0.3–0.625 mg daily; titrate to effect and consider doses up to 1.25–2.5 mg only if necessary.
Vaginal Atrophy: 0.5–2 g cream daily for 21 days, then intermittent use or maintenance dosing as needed.
Osteoporosis Prevention: Low dose (0.3 mg) may be considered when other options are unsuitable, with regular reassessment.
Practical note: elderly patients should begin at the lowest dose and be reviewed every 3–6 months.
Safety Protocols
What stops clinicians from prescribing these medicines to anyone who asks?
Contraindications (Australian Guidelines)
Absolute contraindications include known or suspected breast or oestrogen‑dependent malignancy, unexplained genital bleeding, active or prior VTE, severe liver disease, pregnancy and known hypersensitivity to conjugated estrogens or excipients.
Caution is required in patients with hypertension, diabetes, migraine or strong family histories of hormone‑dependent cancers.
Adverse Effects (Post‑Market Pharmacovigilance)
Common mild effects include breast tenderness, nausea, headache and bloating.
Moderate effects reported include oedema, weight gain and mood changes.
Rare but serious events recorded in post‑market surveillance include cholestatic jaundice, thromboembolism and severe hypertension.
Monitoring should include blood pressure checks, metabolic risk assessment and routine breast and gynaecological surveillance in line with national guidance.
Interaction Mapping
Could your other medicines or lifestyle change how well conjugated estrogens work or increase risks?
Food Interactions (Alcohol, Coffee, Diet In Australia)
Direct food–drug interactions with conjugated estrogens are limited.
Heavy alcohol intake may worsen vasomotor symptoms and affect medication adherence, while high‑fat meals can slightly modify absorption without clinical significance for most patients.
Strongly advise smoking cessation because tobacco markedly increases vascular risk when combined with oestrogen therapy.
Drug Combinations To Avoid (TGA Safety Alerts)
CYP3A4 inducers such as rifampicin, carbamazepine, phenytoin and St John’s wort can reduce systemic CEE levels and potentially reduce efficacy.
Concurrent use with other pro‑thrombotic agents (select anticancer drugs, high‑dose corticosteroids) can increase thrombotic risk and should prompt careful review of benefits and harms.
Check anticoagulation status and review TGA safety alerts or product information when prescribing combinations.
Patient Experience Analysis
What do Australian users say when they report back after starting conjugated oestrogens?
Australian Survey Data
Surveys and clinic audits conducted between 2022 and 2024 report mixed satisfaction levels.
Many patients report rapid relief of hot flushes with oral conjugated oestrogens and strong improvement in vaginal dryness with the cream.
Concerns persist around long‑term cancer and clotting risks, and cost and PBS access are major determinants of whether people start or continue therapy.
Forum And Pharmacy Trends
Community forums and pharmacist consultations frequently favour local vaginal therapy to limit systemic exposure for atrophy symptoms.
Pharmacists across major chains and independents commonly counsel on dosing, contraindications and PBS authority pathways, and rural patients regularly report longer waits and reduced access to specialist prescribing.
Distribution & Pricing Landscape
How easy is it to find Premarin in Australian pharmacies and what will it cost?
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Premarin® and generics are stocked through major Australian chains and independent pharmacies, subject to supplier agreements and TGA registration.
Packs are commonly sold as 28 or 84 tablets, and cream comes in 27.5–28 g tubes at 0.625 mg/g strength.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth prescribing and electronic prescriptions have broadened access to prescription medicines, and online pharmacies now promote convenience and mail‑order delivery.
In our online pharmacy, conjugated estrogens is available without a prescription, with discreet delivery to Australia in 5–14 days.
PBS Vs Private Cost Comparisons
PBS subsidy depends on indication and authority rules; when a subsidy is not available, private costs vary across chains and between brand and generic suppliers.
Price sensitivity leads many patients to compare stores and ask pharmacists about cheaper generics or alternative therapies.
Alternative Options
Prefer a non‑equine product or a different delivery route?
Comparison Of PBS And Non‑PBS Options
Estradiol preparations (oral, patch, gel) are widely used as alternatives and offer a more physiological 17β‑estradiol profile with transdermal patches bypassing first‑pass hepatic effects.
Tibolone is a synthetic single‑compound alternative for some menopausal symptoms and bone protection but has a different safety profile.
Non‑oestrogen local options for atrophic vaginitis include ospemifene and local DHEA.
Pros And Cons Checklist
Pros Of CEE: Long clinical history and established effectiveness at common doses such as 0.3–0.625 mg.
Cons Of CEE: Derived from equine sources, contains a mixed steroid profile, and carries thrombotic and hepatic risks that require consideration and informed patient choice.
Choice should align with PBS criteria, contraindications and patient preferences, including willingness to use an equine‑derived product.
Regulatory Status
What regulatory safeguards apply to conjugated oestrogens in Australia?
TGA Approval Framework
Conjugated oestrogen products such as Premarin® are TGA‑registered prescription medicines in Australia for oral tablets (0.3, 0.625, 1.25 mg) and vaginal cream (0.625 mg/g).
Registration requires evidence of quality, safety and efficacy, and ongoing post‑marketing surveillance informs any label updates or safety communications.
PBS Subsidy Process
Listing on the Pharmaceutical Benefits Scheme (PBS) requires demonstration of cost‑effectiveness and clearly defined indications.
PBS decisions can limit public reimbursement to specific uses such as severe menopausal symptoms or documented ovarian insufficiency, and prescribers must follow authority requirements when issuing PBS scripts.
Consolidated FAQ
Have quick questions? Here are short practical answers.
Can I get Premarin on the PBS in Australia?
Premarin® is TGA‑registered, but PBS subsidy depends on current listings and authority rules; check the PBS schedule or ask your pharmacist for the latest status.
Is the cream safer than tablets?
Vaginal cream delivers local benefit with lower systemic exposure for atrophy, so systemic risk is reduced but not always completely eliminated.
How long should I stay on CEE?
Use the shortest effective duration and review therapy every 3–6 months; maintenance topical regimens for severe urogenital atrophy may be intermittent.
Are equine‑derived products ethical/acceptable alternatives?
Some patients prefer non‑equine products such as estradiol; discuss alternatives with the prescriber if this is a concern.
Visual Guide
Need an infographic to explain access and dosing?
Designers should consider three simple visuals: a PBS pricing flowchart showing the pathway from prescription to subsidy or private purchase, a packaging snapshot displaying tablet blister sizes (0.3, 0.625, 1.25 mg) and cream tube (27.5–28 g at 0.625 mg/g), and a pharmacy distribution map comparing urban versus rural stock and telehealth/mail‑order timelines.
Use clear icons for TGA and PBS seals, pharmacist counselling, contraindications and include quick dosing boxes for vasomotor symptoms versus vaginal use.
Storage & Transport
How should patients store tablets and cream at home, especially during hot Australian summers?
Household Storage Under Australian Climate
Store tablets and cream at 15–25°C in the original packaging and keep them away from heat and humidity.
Avoid storing medicines in bathrooms where moisture and temperature swings are common, particularly in hot, humid coastal regions.
Cold‑Chain Logistics For Pharmacies
Creams must not be frozen and should be kept at stable ambient conditions during transport and mail‑order delivery.
Pharmacies should verify supplier handling practices and advise patients to accept deliveries promptly and store products correctly on receipt, especially for remote deliveries that may be exposed to heat in transit.
Guidelines For Proper Use
What should pharmacists explain at the point of supply?
Pharmacist Counselling Style In Australia
Counselling should be evidence‑led and centred on shared decision‑making.
Explain benefits such as relief of hot flushes and improved vaginal health, quantify risks including VTE and breast cancer, confirm contraindications and check medicines lists for interactions.
Discuss PBS authority pathways, cost options including generic versus brand, and arrange follow‑up at 3–6 months to reassess necessity and tolerability.
National Health Authority Recommendations
Follow TGA‑registered product information and national MHT guidance: prescribe the lowest effective dose, reassess periodically and remind patients about routine breast and cervical screening.
Document informed consent when using off‑label regimens or where long‑term use is anticipated.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–7 days |
| Wollongong | New South Wales | 5–7 days |
| Geelong | Victoria | 5–7 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Albury | New South Wales / Victoria | 5–9 days |
Concluding Practical Notes
Thinking about starting therapy today or switching products?
Conjugated oestrogens remain a viable option for menopausal vasomotor symptoms and urogenital atrophy when used at the lowest effective dose and after a careful assessment of contraindications and risks.
Discuss relative options such as estradiol (oral or transdermal), tibolone or local non‑oestrogen therapies with a prescribing clinician if equine‑derived products are a concern.
Monitor treatment effectiveness and adverse effects and arrange follow‑up at least every 3–6 months, or sooner if complications occur.
Pharmacists can assist with PBS queries, dosing clarifications and safe‑use checks prior to supply.