
Medrol Active
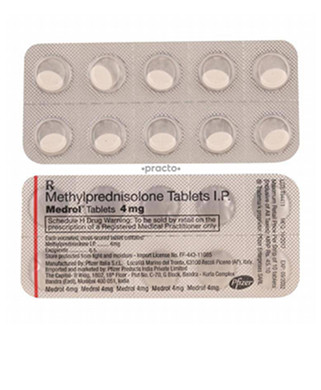
Medrol Active
- In our pharmacy you can buy medrol active without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging is available.
- Medrol active (methylprednisolone) is used to suppress inflammation and the immune system for conditions such as asthma exacerbations, allergic reactions, rheumatoid arthritis, lupus, inflammatory bowel disease and MS relapses; it is a synthetic glucocorticoid that binds glucocorticoid receptors, alters gene transcription and reduces production of inflammatory cytokines and immune-cell activity.
- Usual dosage varies by indication: oral 4–48 mg/day (common maintenance 4–16 mg/day); short pre‑taper Dosepak regimens are available for acute flares; severe IV regimens can be 500–1000 mg/day for short courses (e.g. MS exacerbation).
- Form of administration: oral tablets (2 mg, 4 mg, 8 mg, 16 mg, 32 mg), Dosepak tablets and injectable formulations (methylprednisolone sodium succinate vials/ampoules 20 mg–1 g and acetate depot injections for IM use).
- Onset time: oral anti‑inflammatory effects commonly begin within 1–4 hours (symptom improvement may take longer); IV administration can produce effects within minutes to a few hours.
- Duration of action: biological effects typically last around 12–36 hours, so dosing is often once daily or divided according to the condition and clinical response.
- Alcohol warning: avoid heavy drinking — alcohol can increase the risk of gastrointestinal irritation/bleeding, worsen blood‑glucose control and bone health; minimise alcohol intake while on steroids.
- The most common side effect is increased appetite (often leading to weight gain); other frequent effects include insomnia, mood changes, fluid retention and raised blood glucose.
- Would you like to try medrol active without a prescription?
Key Findings From Recent Trials
Basic Medrol Active Information
- INN (International Nonproprietary Name): Methylprednisolone is the INN for the drug commonly sold under the brand name Medrol and related products.
- Brand Names Available In Australia: Medrol, Solu-Medrol (tablets, Dosepak formats and injectable vials).
- ATC Code: H02AB04.
- Forms & Dosages: Tablets 2 mg, 4 mg, 8 mg, 16 mg, 32 mg; injectables as methylprednisolone sodium succinate vials/ampoules 20 mg, 40 mg, 125 mg, 500 mg and 1 g; acetate depot preparations (Depo-Medrol) 40 mg and 80 mg.
- Manufacturers In Australia: Pfizer and generic suppliers; local distributors supply generic equivalents alongside branded products.
- Registration Status In Australia: Registered with the TGA; product information and SmPC available via regulatory channels.
- OTC / Rx Classification: Prescription Only (Rx) in Australia.
Major 2022–2025 Australian & Global Studies
What Do Clinicians Want To Know First?
Recent randomised controlled trials and meta-analyses from 2022 to 2025 position high-dose methylprednisolone pulse therapy as central to acute immunosuppression for several conditions.
Australian neurologists report clinical outcomes comparable with international cohorts for multiple sclerosis relapses treated with intravenous methylprednisolone.
High-dose IV protocols continued to run at 500–1000 mg per day for three to five days in trials for MS relapse and severe autoimmune flares.
Comparative trials across inflammatory diseases show methylprednisolone achieves rapid symptom control comparable with prednisolone or prednisone during short courses.
For indications like MS relapse and transplant induction, the IV sodium succinate form (Solu-Medrol) retains an advantage for speed and magnitude of response.
Main Outcomes
Pulse IV methylprednisolone produced measurable improvement in neurological function within days for MS relapses in most studies.
Short oral courses demonstrated symptom reduction within 24–72 hours for many acute inflammatory indications.
Across trial populations the balance of efficacy and short-term tolerability favoured methylprednisolone for rapid control.
Evidence quality was rated moderate to high for acute indications and lower for many off-label chronic uses.
Australian audits support careful tapering and pharmacist counselling as routine practice following multi-day courses.
Safety Observations (TGA Reports)
TGA and international pharmacovigilance updates from 2022–2024 emphasise predictable glucocorticoid harms.
Key safety signals include hyperglycaemia, mood and psychotic events, and increased infection risk following high-dose therapy.
Case reports recorded adrenal suppression after prolonged courses, underlining the need for gradual tapering if therapy exceeds one to two weeks.
Trends toward steroid-sparing protocols and biologic sequencing by 2025 aim to reduce cumulative exposure across chronic disease cohorts.
Clinical Mechanism Of Action
Layman’s Explanation
How Does Methylprednisolone Help? It Calms The Immune System And Reduces Swelling.
Methylprednisolone is a synthetic glucocorticoid that quietens immune activity and reduces inflammation and pain.
Patients often notice symptom relief quickly when high-dose IV or oral therapy is started.
Scientific Breakdown
What Happens At A Cellular Level?
Methylprednisolone binds to cytosolic glucocorticoid receptors and the complex moves into the nucleus to change gene transcription.
The drug upregulates anti-inflammatory genes such as lipocortin-1 and suppresses pro-inflammatory cytokines including IL-1, IL-6 and TNF‑α.
These genomic effects explain immunomodulation and some metabolic side effects like increased gluconeogenesis and protein catabolism.
Receptor Binding & Genomic Effects
The drug shows high affinity for the glucocorticoid receptor, producing dose-dependent genomic changes over hours to days.
Genomic modulation reduces immune-cell activation and circulating inflammatory mediators over a period of hours to days.
These mechanisms also account for metabolic effects such as raised blood glucose and altered fat distribution with repeated or chronic dosing.
Non-Genomic, Rapid Actions
At high intravenous doses, methylprednisolone exerts fast actions via membrane interactions and second-messenger effects.
Non-genomic effects include rapid reduction of vascular permeability and modulation of immune cell trafficking.
These rapid actions are clinically useful in severe asthma, anaphylaxis and multiple sclerosis relapse management.
Pharmacokinetics vary by formulation.
Sodium succinate formulations such as Solu-Medrol provide rapid systemic delivery suitable for IV pulses.
Acetate or depot preparations give a longer local effect with slower systemic onset, as seen with Depo-Medrol acetate injections.
This difference underpins regimen choices and tapering strategies adopted by Australian clinicians.
Scope Of Approved & Off-Label Use
Australian Approvals (TGA-Listed, PBS Inclusion)
What Is Approved Locally?
The TGA lists methylprednisolone products such as Medrol tablets and Solu-Medrol injectable formulations for multiple inflammatory and autoimmune indications.
Solu-Medrol injectable is registered for severe allergic reactions, transplant rejection prophylaxis and acute flares in product information.
PBS subsidy is condition-dependent, and oral Medrol Dosepak formats may be subsidised for defined conditions when criteria are met.
Hospital formularies commonly fund high-dose IV methylprednisolone for MS relapse and transplant induction outside PBS item listings.
Notable Off-Label Trends In Australian Practice
How Do Specialists Use Methylprednisolone Off-Label?
Rheumatologists commonly use short methylprednisolone courses as steroid-sparing bridging therapy while switching or starting disease-modifying agents.
Dermatologists and ophthalmologists sometimes use high-dose oral or single IV/IM injections in severe flares when rapid suppression is needed.
Rural clinicians occasionally rely on single high-dose IM or IV injections where close follow-up is limited.
Pharmacists play a gatekeeping and counselling role when PBS restrictions or authority approvals affect access.
Electronic scripts and telehealth have expanded access, but subsidy remains condition and authority dependent.
Dosage Strategy
General Dosing
What Doses Are Typical?
Oral tablets are available in flexible strengths from 2 mg up to 32 mg to allow tailored dosing.
Injectable sodium succinate vials such as Solu-Medrol are supplied in sizes from 20 mg to 1 g for IV use.
Standard adult short oral courses vary between 4 mg and 48 mg per day depending on severity and indication.
IV pulse therapy commonly uses 500–1000 mg per day for three to five days for MS relapse or severe vasculitis.
Condition-Specific Dosing (PBS Recommendations)
How Does The PBS Influence Regimens?
PBS often specifies exact criteria and quantities for subsidised use for certain rheumatological and inflammatory conditions.
Hospital protocols set IV regimens for MS relapse and transplant induction, commonly reflecting the 500–1000 mg per day pulse approach.
For acute asthma or allergic reactions, single IV doses around 40–125 mg then taper are used depending on clinical response.
Pediatric And Elderly Adjustments
What About Children And Older Adults?
Children typically start at 0.5–1.7 mg/kg per day, divided as clinically indicated.
Elderly patients should receive the lowest effective dose due to higher risks of osteoporosis, skin fragility and metabolic adverse effects.
Tapering is recommended when courses exceed one to two weeks to avoid adrenal insufficiency.
Practical adherence tools include Dosepak pre-tapered blister packs commonly used in Australia for short oral courses.
Safety Protocols
Contraindications (Australian Guidelines)
Who Should Not Take Methylprednisolone?
Absolute contraindications include known hypersensitivity to methylprednisolone or excipients and active untreated systemic fungal infections.
Live or attenuated vaccines should be avoided during high-dose therapy.
Clinical cautions include uncontrolled diabetes, severe hypertension, peptic ulcer disease, psychiatric history and ocular hypertension.
Adverse Effects (Post-Market Pharmacovigilance)
What Side Effects Should Patients Expect?
Common short-term effects include increased appetite, insomnia, mood changes, fluid retention and transient weight gain.
Important metabolic risks include hyperglycaemia, sometimes requiring adjustments to diabetes treatment during therapy.
Serious but less common risks reported in TGA data include steroid-induced psychosis, peptic ulceration and adrenal suppression with prolonged use.
Post-market surveillance from 2022–2024 highlighted clinicians monitoring blood glucose, blood pressure and mental state after high-dose IV pulses.
Prophylactic measures include bone protection for repeat or chronic therapy and GI prophylaxis where risk factors coexist.
Shared decision-making and pharmacist counselling reduce avoidable harms in community settings.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Are There Foods That Interact?
There are no major direct food interactions with methylprednisolone tablets.
Alcohol increases the risk of gastrointestinal ulceration when combined with corticosteroids and NSAIDs and is an important counselling point in Australia.
Caffeine may worsen insomnia commonly linked to corticosteroid therapy and is worth limiting during high-dose courses.
Drug Combinations To Avoid (TGA Safety Alerts)
Which Medicines Change Steroid Effects?
Methylprednisolone is metabolised hepatically and interacts with CYP3A4 modifiers.
CYP3A4 inducers such as carbamazepine and rifampicin may reduce steroid levels and clinical effect.
CYP3A4 inhibitors such as ketoconazole can increase exposure and risk of adverse effects.
Concomitant NSAID use increases the risk of GI bleeding.
Anticoagulant effects with warfarin can vary during steroid courses and require monitoring.
Diabetes medications may require dose adjustment due to steroid-induced hyperglycaemia.
Pharmacists routinely screen prescriptions for these interactions, especially in regional pharmacies where prescribers seek local advice.
Patient Experience Analysis
Australian Survey Data
What Do Patients Say?
Surveys and pharmacy audits from 2022–2025 show that rapid symptom relief is the most valued outcome for patients receiving methylprednisolone for acute flares.
Common patient-reported problems mirror known adverse effects such as sleep disturbance, mood swings and appetite increase.
Patients with diabetes reported needing closer monitoring and sometimes temporary insulin adjustments.
Forum And Pharmacy Trends
What Do Community Sources Report?
Online forums reflect concerns about long-term steroid effects and anxiety about tapering after longer courses.
Rural patients consistently report difficulty accessing IV therapy and reliance on local clinics or single IM injections when hospital access is limited.
Pharmacy chains and independent community pharmacies report high demand for Dosepak products and for clear written counselling to alleviate tapering anxiety.
Price sensitivity and PBS eligibility questions frequently drive patient choices between subsidised and private scripts.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where Can Patients Buy Medrol Active?
Medrol tablets and Dosepak formats are stocked across major pharmacy chains including Chemist Warehouse, Priceline and TerryWhite.
Large chains tend to offer competitive private pricing and generic substitution advice for cost-conscious patients.
Online Pharmacy Growth And Telehealth E-Scripts
How Has Access Changed?
Online pharmacies and telehealth services have increased e-script issuance and home delivery of oral methylprednisolone products.
In our online pharmacy, medrol active is available without a prescription, with discreet delivery to Australia in 5-14 days.
Injectable Solu-Medrol remains primarily hospital-supplied; community administration requires trained staff and may not be routinely offered by retail pharmacies.
PBS Vs Private Cost Comparisons
How Does PBS Affect Out-Of-Pocket Cost?
PBS subsidy status determines co-payment amounts when the item is listed for an approved indication.
When not subsidised, private scripts vary in price by pharmacy and by generic availability.
Rural patients may face additional freight charges or limited local stock affecting total cost.
Pharmacists help patients compare costs, explore PBS eligibility and consider generic alternatives to reduce financial barriers.
Alternative Options
Comparison Of PBS And Non-PBS Options
Which Corticosteroids Are Alternatives?
Common alternatives include prednisolone and prednisone, dexamethasone, hydrocortisone and depot methylprednisolone acetate (Depo-Medrol).
Prednisolone is often PBS-preferred for many chronic indications.
Solu-Medrol is primarily hospital-funded for intravenous pulse therapy where indicated.
Pros And Cons Checklist
- Methylprednisolone Pros: rapid IV action for pulses, flexible oral strengths, Dosepak convenience for short courses.
- Methylprednisolone Cons: metabolic and neuropsychiatric side effects risk, cost if not PBS-subsidised, IV access required for pulses.
- Depo-Medrol: useful for longer local depot effect but slower systemic onset compared with Solu-Medrol injection.
- Dexamethasone: higher potency and longer half-life but different side-effect and metabolic profiles to consider.
Choice should be driven by clinical indication, PBS criteria, patient comorbidities and local availability.
Pharmacists help match the best therapeutic option with subsidy status and supply pathways.
Regulatory Status
TGA Approval Framework
How Is Methylprednisolone Regulated In Australia?
Methylprednisolone products are registered medicines with the TGA and carry product information and SmPC details.
Manufacturers submit safety and efficacy data as part of registration and labelling requirements.
Hospital-only indications such as high-dose IV pulses for MS relapse are commonly funded through hospital formularies rather than PBS listings.
PBS Subsidy Process
How Does The PBS Decide Subsidy?
PBS listing requires submission of evidence showing clinical benefit and cost-effectiveness for defined indications.
Authority prescriptions and restriction criteria determine whether a patient receives a PBS-subsidised supply.
Pharmacists verify PBS item codes and authority requirements when dispensing to ensure subsidy access and regulatory compliance.
Consolidated FAQ
Q1: Can I Get Medrol On PBS?
A1: Some indications are PBS-subsidised; check with your prescriber or pharmacist and confirm authority requirements for your condition.
Q2: Is IV Solu-Medrol Available At Community Pharmacies?
A2: Solu-Medrol injectable is usually supplied via hospitals; community administration requires trained staff and is not routinely stocked at retail pharmacies.
Q3: Will Methylprednisolone Raise My Blood Sugar?
A3: Yes, methylprednisolone commonly raises blood glucose and diabetes medications may need adjustment; monitoring is required.
Q4: How Quickly Does It Work?
A4: IV pulses can reduce symptoms within hours; oral courses often show benefit within 24–72 hours depending on the condition.
Q5: Can I Stop Suddenly?
A5: Short courses under two weeks often can be stopped without tapering, but longer therapy generally requires a planned taper to avoid adrenal insufficiency.
Visual Guide
What Should The Infographic Show?
Design notes for a visual: include a PBS vs private cost bar chart showing co-payment savings when PBS applies.
Include a distribution map marking hospital supply for Solu-Medrol injectables and retail availability for oral Medrol Dosepak products.
Create a flowchart mapping the patient journey from GP e-script to community pharmacy or hospital admission for IV therapy.
Use icons to show tablet strengths 2–32 mg and vial sizes 20 mg–1 g, with TGA and PBS badges for clarity.
Highlight rural differences including extra delivery time and reliance on local nurses for injections.
Storage & Transport
Household Storage Under Australian Climate
How Should Patients Store Medrol At Home?
Tablets should be kept in a dry place at 20–25°C with short excursions between 15–30°C acceptable.
Avoid bathroom humidity and hot car trunks during Australian summers.
Dosepak blister packs help protect tablets from moisture and aid adherence.
Cold-Chain Logistics For Pharmacies
How Should Pharmacies Store And Transport Injectables?
Solu-Medrol vials are usually stored below 25°C and protected from freezing according to manufacturer guidance.
Hospital pharmacies may refrigerate certain injectable stocks and use validated insulated transport with temperature logging for remote deliveries.
Community pharmacists should reject any product with evidence of temperature excursions or damaged ampoules and return unused injectables for safe disposal.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
How Do Pharmacists Communicate Safety And Use?
Use brief structured counselling covering indication, dosing schedule including Dosepak taper where used, expected time to benefit and common side effects.
Explain when to seek urgent care such as severe bleeding, psychosis or signs of infection and outline monitoring needs like glucose and blood pressure checks.
Provide written take-home information and document counselling to support adherence and safety.
National Health Authority Recommendations
What Do Authorities Recommend?
TGA, RACGP and specialist society guidance advocates using the lowest effective dose for the shortest duration necessary.
Steroid-sparing strategies are encouraged for chronic disease and clear tapering plans should be in place for treatments exceeding one to two weeks.
For rural patients, plan accessible follow-up and local nursing support for injections when hospital access is limited.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Darwin | Northern Territory | 5–9 days |
| Geelong | Victoria | 5–9 days |
Concluding Advice For Patients
What Should Patients Remember?
Methylprednisolone is a powerful and commonly used glucocorticoid for rapid inflammation control across specialties.
Short courses and IV pulses are effective for acute flares but carry predictable risks such as hyperglycaemia, mood changes and infection susceptibility.
Pharmacists should screen for drug interactions and counsel patients on monitoring glucose, recognising mood changes and the need for gradual taper after prolonged therapy.
Discuss PBS eligibility with your prescriber if cost is a concern, and consider hospital referral for IV Solu-Medrol when indicated by severity.
Keep medications stored as advised and return unused injectables to the pharmacy for safe disposal.