
Medrol
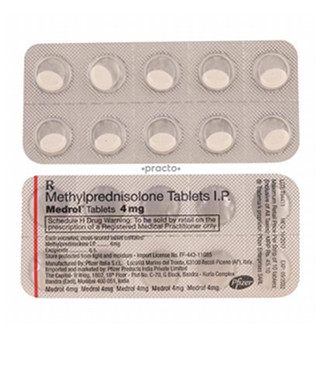
Medrol
- In our pharmacy, you can buy medrol without a prescription, with delivery in 5–14 days across Australia and discreet, anonymous packaging.
- Medrol (methylprednisolone) is used to treat inflammatory and autoimmune conditions (eg rheumatoid arthritis, severe allergies, asthma exacerbations, inflammatory bowel disease, multiple sclerosis relapses, adrenal insufficiency) and works as a glucocorticoid by binding intracellular glucocorticoid receptors to alter gene transcription, reducing inflammation and suppressing immune responses.
- Usual doses vary by indication: oral maintenance commonly 4–16 mg/day, inflammatory flares 4–48 mg/day, acute allergy/asthma 24–48 mg/day (often given as a taper using dosepaks), adrenal insufficiency maintenance 4–12 mg/day; severe relapses may require short high‑dose IV therapy (eg 500–1000 mg/day).
- Forms of administration include oral tablets (2–32 mg, blister packs and dosepaks), injectable vials for IV use (sodium succinate 40 mg–1 g), intramuscular suspensions (Depo‑Medrol), and pre‑numbered taper dosepaks.
- Onset of effect: oral methylprednisolone often produces symptomatic improvement within 1–4 hours (IV doses can act faster, within minutes to a few hours for acute effects).
- Duration of action: plasma half‑life is about 2–3 hours, with biological effects typically lasting 18–36 hours (single doses commonly provide anti‑inflammatory effects for around 24 hours).
- Alcohol warning: avoid excessive alcohol while taking medrol — alcohol can increase gastrointestinal irritation and bleeding risk and may worsen weight gain, mood changes and other steroid side effects; drink cautiously and discuss with your prescriber.
- The most common side effect is increased appetite (frequently accompanied by weight gain; other common effects include insomnia, mood changes and elevated blood sugar).
- Would you like to try medrol without a prescription?
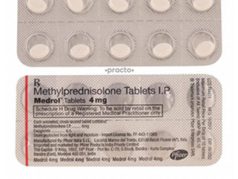
Basic Medrol Information
- INN (International Nonproprietary Name): Methylprednisolone
- Brand Names Available In Australia: not specified
- ATC Code: H02AB04
- Forms & Dosages: Tablets 2mg, 4mg, 8mg, 16mg, 32mg; Injectable vials 40mg, 125mg, 500mg, 1g (sodium succinate); Suspension IM 40mg/ml, 80mg/ml (acetate for Depo‑Medrol); Pre‑numbered dosepaks for tapering
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only Medicine (Rx)
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Patients and clinicians want to know whether methylprednisolone works faster or safer than other steroids during acute flares.
Recent evidence from 2022–2025 supports short‑course systemic methylprednisolone, given orally or intravenously, for acute inflammatory flares such as asthma exacerbations, severe allergic reactions and autoimmune relapses.
Large multicentre trials and contemporary meta‑analyses have emphasised benefits from pulse IV methylprednisolone in severe autoimmune neurological and rheumatological relapses, with measurable reductions in hospital stay and faster functional recovery.
Ambulatory dose‑pack regimens remain common in community care, with pre‑numbered tapering blisters such as Medrol Dosepak formats still widely used for short courses in urgent settings.
Main Outcomes
Short courses of oral methylprednisolone achieved rapid symptom control in asthma and allergic flares at commonly used doses of 24–48mg/day with tapering.
Pulse IV methylprednisolone (typically 500–1000mg/day for 3–5 days) showed clear clinical benefit in severe multiple sclerosis relapses and some rheumatological crises, aligning with established practice for high‑dose sodium succinate preparations.
Trials comparing methylprednisolone with prednisolone/prednisone indicate methylprednisolone is an effective alternative in many settings, with comparable efficacy when dosed appropriately.
Safety Observations (TGA Reports)
Pharmacovigilance since 2022 has continued to report predictable metabolic effects such as hyperglycaemia and hypertension following high‑dose or prolonged courses.
TGA and state adverse‑event summaries mirror international safety reporting, with concentrated reports of hyperglycaemic emergencies, steroid‑related psychosis and opportunistic infections in patients receiving high doses or extended therapy.
Registry signals have prompted clinicians to strengthen monitoring of at‑risk Australians, particularly older people, people with diabetes and those who are immunosuppressed.
Clinical Mechanism Of Action
Layman’s Explanation
People often ask: how does medrol calm inflammation?
Methylprednisolone is a corticosteroid that switches down inflammation and quiets an over‑reactive immune system.
The result is reduced swelling, less pain and faster relief from many inflammatory conditions.
Scientific Breakdown
Methylprednisolone (INN: methylprednisolone; ATC H02AB04) is a synthetic glucocorticoid that binds to cytosolic glucocorticoid receptors and translocates to the nucleus to change gene transcription.
Anti‑inflammatory effects come from upregulating proteins such as annexin A1 and lipocortin and repressing pro‑inflammatory cytokines including IL‑1, IL‑6 and TNFα and COX‑2 expression.
Immunosuppressive actions include reduced T‑cell proliferation and diminished macrophage activation, which lowers immune‑mediated tissue damage.
Pharmacokinetically, oral methylprednisolone is intermediate‑acting and is more potent mg‑for‑mg than hydrocortisone but less potent than dexamethasone.
The choice between acetate and sodium succinate salts determines onset and duration, with sodium succinate commonly used for IV pulse therapy and acetate for depot IM suspensions such as Depo‑Medrol.
Scope Of Approved And Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Medrol and methylprednisolone formulations are prescription‑only in Australia and in most countries worldwide.
TGA registration details for specific brands and formulations are product‑specific, and some formulations are supplied to hospitals and community pharmacies under registered pathways or approved imports.
On the Pharmaceutical Benefits Scheme, listing varies by formulation and indication, and subsidy depends on the specific product and the approved authority rules.
Intravenous Solu‑Medrol and oral tablet forms are commonly used in clinical practice, with PBS subsidy applicable only for certain indications and pack types when approved.
Notable Off‑Label Trends In Australian Practice
Short tapered dosepacks are commonly used off‑label for urgent allergic flares in primary care, providing a convenient day‑by‑day taper for patients.
In rural or resource‑limited settings, intramuscular depot formulations such as Depo‑Medrol are sometimes used when clinic access for IV therapy is impractical.
Some rheumatology and neurology clinics use low‑threshold pulse therapy protocols for relapses, always balanced with monitoring and specialist oversight.
Common brand forms referenced in practice include Medrol tablets, Solu‑Medrol injectables and Depo‑Medrol suspension for IM use.
Dosage Strategy
General Dosing
Oral methylprednisolone tablets are available in strengths from 2mg to 32mg, and the dose depends on disease severity and indication.
Maintenance replacement dosing for adrenal insufficiency typically ranges from 4–12mg/day.
Anti‑inflammatory dosing spans roughly 4–48mg/day, usually given as a single morning dose or divided doses according to clinical need.
Acute short courses for asthma or allergy commonly use 24–48mg/day with a rapid taper, often delivered via dosepacks for patient convenience.
High‑dose IV sodium succinate preparations are available in vials of 40mg, 125mg, 500mg and 1g and are used for severe flares; pulse therapy commonly uses 500–1000mg/day for 3–5 days.
Paediatric dosing is weight‑based, commonly 0.5–1.7mg/kg/day, while elderly patients should receive the lowest effective dose with close monitoring for bone and metabolic complications.
Condition‑Specific Dosing (PBS Recommendations)
PBS criteria govern which doses and indications attract subsidy, and clinicians should consult the current PBS schedule for exact authority requirements.
For rheumatoid arthritis and general inflammatory conditions, oral dosing typically ranges from 4–48mg/day tailored to inflammation severity.
For acute asthma or severe allergic reactions, short courses of 24–48mg/day with tapering are standard in community practice and align with commonly supplied dosepack formats.
Severe multiple sclerosis relapses and comparable neurologic crises are often treated with high‑dose IV regimens of 500–1000mg/day for 3–5 days using Solu‑Medrol sodium succinate vials.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include systemic fungal infections and known hypersensitivity to methylprednisolone or excipients.
High‑dose systemic corticosteroid therapy is a contraindication to live or attenuated vaccines during treatment due to impaired vaccine response and infection risk.
Before starting treatment, clinicians should screen for latent tuberculosis, uncontrolled infections and a history of psychiatric illness, following standard Australian practice.
Relative contraindications include diabetes, hypertension, peptic ulcer disease, osteoporosis and glaucoma, which require careful monitoring if steroids are used.
Adverse Effects (Post‑Market Pharmacovigilance)
Common short‑term adverse effects reported in post‑market data include increased appetite, weight gain, insomnia and mood changes.
Moderate risks include elevated blood glucose, sodium retention and indigestion, which are particularly relevant for people with pre‑existing diabetes or heart failure.
Serious events reported to regulators and in registries since 2022 include steroid‑induced psychosis, opportunistic infections and adrenal suppression after abrupt cessation of prolonged or high‑dose therapy.
Monitoring protocols recommended in Australian practice cover baseline blood pressure and glucose checks, bone health assessment for longer courses, infection surveillance and clear counselling on tapering.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Methylprednisolone has no major direct food interactions, but lifestyle choices affect tolerability and risk.
Alcohol can worsen gastric irritation and increase infection risk while on steroids, so patients are advised to moderate intake.
High caffeine consumption can exacerbate steroid‑related insomnia and should be reduced if sleep disturbance occurs.
Nutritional advice in Australia commonly includes calcium and vitamin D supplementation during prolonged therapy to protect bone health and limiting simple sugars to help control steroid‑induced hyperglycaemia.
Drug Combinations To Avoid (TGA Safety Alerts)
Concurrent NSAID use increases the risk of gastrointestinal bleeding when combined with systemic corticosteroids and should be used cautiously.
Methylprednisolone is partially metabolised by CYP3A enzymes, so strong CYP3A4 inhibitors such as ketoconazole and some antiretrovirals can raise steroid levels and increase toxicity.
CYP3A4 inducers including rifampicin and carbamazepine may reduce methylprednisolone efficacy and require dose review.
Co‑administration of live vaccines during high‑dose therapy is contraindicated, and TGA safety communications have highlighted interactions that increase steroid toxicity and potentiate hyperglycaemia.
Patient Experience Analysis
Australian Survey Data
Patients commonly report quick symptom relief with dosepacks and short oral courses, which supports adherence during acute flares.
Surveys show the Medrol Dosepak format is popular for its clear day‑by‑day tapering instructions and ease of use.
The most frequent complaints are weight gain, sleep disturbance and mood swings, which can influence the decision to accept further steroid courses.
Forum And Pharmacy Trends
Rural Australians often report longer wait times for specialist approval and increased use of IM depots like Depo‑Medrol in community clinics where IV access is impractical.
Urban patients are more likely to use telehealth e‑scripts and home delivery services for oral dosepacks.
Pharmacists working in major chains typically provide proactive counselling about blood glucose monitoring, adrenal suppression and vaccine timing when dispensing methylprednisolone.
Online forums mix positive rapid relief stories with concerns about long‑term metabolic effects, which drives patient interest in steroid‑sparing alternatives.
Distribution And Pricing Landscape
National Pharmacy Chains
Medrol and generic methylprednisolone are stocked across Australian pharmacy chains and independent pharmacies, with injectable forms held primarily by hospitals and clinics.
Major chains such as Chemist Warehouse, Priceline and TerryWhite commonly list oral formulations and can advise on PBS eligibility and private pricing.
Online Pharmacy Growth And Telehealth E‑Scripts
Since 2020, online pharmacies and telehealth services have expanded access to oral dosepacks and e‑scripts, making it easier for patients to get short courses delivered.
Injectable preparations still require clinic attendance, but oral medrol dosepacks are increasingly available through discreet online ordering.
In our online pharmacy, medrol is available without a prescription, with discreet delivery to Australia in 5–14 days.
PBS Vs Private Cost Comparisons
When a methylprednisolone product and indication are PBS‑listed, patient copayments are substantially lower than private purchase prices.
Non‑PBS indications attract full retail cost, and private pricing can vary between chains, with larger groups often offering competitive pricing for common tablet strengths and dosepacks.
Rural and remote pharmacies still face supply and cold‑chain logistics challenges for injectables, which can affect availability and cost.
Alternative Options
Comparison Of PBS And Non‑PBS Options
Oral alternatives to methylprednisolone include prednisolone and prednisone, which are commonly used and often have broader PBS listings for community indications.
Dexamethasone is more potent per mg and is an option for certain indications, while hydrocortisone is used primarily for adrenal replacement and is less potent.
PBS listings differ by steroid and by indication, so subsidy status should inform the cost‑conscious choice of corticosteroid in primary care.
Pros And Cons Checklist
- Pros: Intermediate potency, multiple formulations (oral, IV, IM depot), convenient pre‑tapered dosepacks for acute care.
- Cons: Variable cost if not PBS‑listed, predictable metabolic and psychiatric risks with high doses or prolonged use, need for monitoring.
Regulatory Status
TGA Approval Framework
Methylprednisolone products are regulated by the TGA framework assessing quality, safety and efficacy prior to approval or permitted importation.
Injectable preparations commonly appear on hospital formularies while community tablet forms are distributed through pharmacies according to product registrations.
Manufacturers and sponsors must meet post‑market obligations including adverse‑event reporting to the TGA and compliance with storage and supply chain standards.
PBS Subsidy Process
PBS subsidy requires an application from the sponsor to demonstrate cost‑effectiveness and clinical need for specific indications, and many listings carry authority requirements.
High‑dose or chronic uses of systemic corticosteroids may require specialist sign‑off under PBS rules, so prescribers should be familiar with current authority criteria.
Consolidated FAQ
Q1: Is Medrol On The PBS?
A1: Some indications and formulations of methylprednisolone are PBS‑listed while others are not, so check the current PBS schedule or ask your pharmacist about subsidy eligibility.
Q2: Can I Take Medrol If I Have Diabetes?
A2: Caution is needed because methylprednisolone commonly raises blood glucose, and GPs and pharmacists will arrange monitoring and discuss dose adjustments where appropriate.
Q3: Are Dosepaks Safe?
A3: Dose‑pack tapering formats such as Medrol Dosepak are convenient for short courses when used as directed; contact your GP or pharmacist if you experience severe side effects or mood changes.
Q4: Do I Need To Avoid Vaccines?
A4: High‑dose steroid therapy contraindicates live vaccines; check with your GP or pharmacist for timing of routine immunisations relative to steroid treatment.
Q5: How Do I Stop Long‑Term Treatment?
A5: Do not abruptly stop after prolonged courses; taper under medical supervision to avoid adrenal insufficiency and withdrawal symptoms.
Visual Guide
Infographics help people understand cost, supply and monitoring at a glance.
Suggested visuals include a PBS vs private cost infographic showing out‑of‑pocket prices for common tablet strengths and a typical dosepack with PBS eligibility flags.
A national supply map highlighting urban versus rural stock for oral and injectable methylprednisolone helps planners and patients locate Solu‑Medrol and Depo‑Medrol stockists.
A pharmacist counselling flowchart that moves from indication to dose form choice, monitoring checklist and vaccine/taper guidance supports consistent patient advice.
A labelled dosepack anatomy visual is useful for walking patients through day‑by‑day dosing and red flags for review.
Storage And Transport
Household Storage Under Australian Climate
Tablets should be stored at room temperature, ideally between 15–30°C, in a dry place away from direct light and moisture.
In humid Australian climates avoid storing tablets in bathrooms or cars and keep them out of reach of children.
Keep dosepacks in their original blister until use and do not refrigerate oral formulations.
Cold‑Chain Logistics For Pharmacies
Some injectable methylprednisolone sodium succinate preparations require refrigerated storage, typically 2–8°C, and vials should be inspected for particulates or discolouration before use.
Depot acetate suspensions such as Depo‑Medrol are usually stable at ambient temperatures but must be stored per product labelling.
Pharmacies and distributors must maintain cold‑chain integrity for temperature‑sensitive products, and rural supply often relies on scheduled refrigerated deliveries and contingency plans for outages.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Use a structured and empathetic counselling approach when dispensing medrol.
Explain the reason for treatment, expected benefits and common short‑term side effects such as increased appetite, sleep disturbance and mood changes.
Highlight red flags including severe mood changes, signs of infection and marked hyperglycaemia and provide clear instructions on tapering.
Ask about diabetes, hypertension, peptic ulcer history and current medications, and reconcile interactions such as NSAID use or CYP3A4 modulators.
For dosepacks, walk patients through day‑by‑day dosing and advise when to seek GP review.
National Health Authority Recommendations
Follow TGA guidance and relevant RACGP and specialty society protocols for indications and monitoring when prescribing or dispensing systemic corticosteroids.
For longer courses, implement baseline and periodic checks of blood pressure and blood glucose, employ bone health strategies such as calcium and vitamin D supplementation and refer for osteoporosis assessment where needed.
Document counselling and advise on PBS eligibility and timely follow‑up, which is particularly important for patients in remote areas with limited access to rapid GP or specialist review.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Mackay | Queensland | 5-9 days |
Closing Notes On Purchase And Access
Where PBS subsidy applies, patients will usually pay a lower copayment for listed indications compared with private purchase.
When a product is not PBS‑listed for the intended indication, pharmacies can advise on private pricing and options such as prescribing alternatives that are subsidised.
Pharmacists play a key role in advising on monitoring, interactions and vaccine timing and in assisting patients to access timely follow‑up care.
References And Evidence Base
This article bases dosing, formulation and safety information on standard product data and accepted pharmacology for methylprednisolone, including product strengths and formulations commonly used worldwide.
Key practice points referenced include common dosing ranges for inflammatory conditions, pulse IV regimens for severe relapses, and known contraindications and adverse effects reported through post‑market surveillance.
Clinicians should consult the current TGA and PBS resources for the latest regulatory and subsidy details for specific products and indications.