
Omnicef
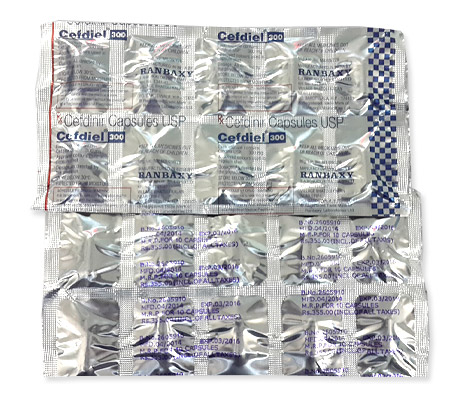
Omnicef
- In our pharmacy, you can buy omnicef without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Omnicef (cefdinir) is a third‑generation oral cephalosporin antibiotic used for community‑acquired pneumonia, acute bacterial sinusitis, pharyngitis/tonsillitis, acute exacerbations of chronic bronchitis and uncomplicated skin and skin‑structure infections; it works by binding penicillin‑binding proteins and inhibiting bacterial cell‑wall synthesis, producing a bactericidal effect.
- Usual doses: adults/adolescents (≥13 years) commonly 300 mg every 12 hours or 600 mg once daily depending on the indication (typical courses 5–10 days, 10 days for pneumonia); children 6 months–12 years: approximately 14 mg/kg/day divided q12–24h (maximum 600 mg/day); pharyngitis regimens may be 7 mg/kg q12h or 14 mg/kg once daily for 5–10 days.
- Form of administration: oral only — capsules 300 mg and reconstitutable oral suspension 125 mg/5 mL or 250 mg/5 mL (paediatric flavours available).
- Onset time: many patients notice symptom improvement within 24–48 hours, though full clinical response may take up to 72 hours depending on the infection.
- Duration of action: each dose provides antibacterial coverage for roughly 12–24 hours (allowing once‑ or twice‑daily dosing); treatment courses usually last 5–10 days depending on the indication.
- Alcohol warning: avoid alcohol while taking omnicef as it can worsen side effects (especially gastrointestinal upset and dizziness) and may impede recovery.
- The most common side effect is diarrhoea; other frequent effects include nausea, vomiting, abdominal pain, headache and rash (rarely children may have red‑coloured stools when cefdinir is taken with iron products).
- Would you like to try omnicef without a prescription?
Basic Omnicef Information
- INN (International Nonproprietary Name): Cefdinir
- Brand Names Available In Australia: not specified
- ATC Code: J01DD15
- Forms & Dosages: Capsules 300 mg; Oral suspension 125 mg/5 mL and 250 mg/5 mL; common adult dosing 300 mg every 12 hours or 600 mg once daily for selected indications; paediatric dosing weight‑based with maximum 600 mg/day; renal dose adjustment if creatinine clearance <30 mL/min.
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription‑only (Rx) in major jurisdictions
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Patients and clinicians often ask whether new large trials changed how cefdinir is used in practice.
Recent literature from 2022 to 2025 focused largely on surveillance, stewardship and comparative effectiveness rather than new large randomised cefdinir trials.
Australian and international respiratory surveillance studies reported variable susceptibility of Streptococcus pneumoniae and Haemophilus influenzae to oral third‑generation cephalosporins.
Many papers recommend reserving oral third‑generation cephalosporins for cases where first‑line agents are unsuitable.
Smaller observational paediatric outpatient studies noted cefdinir’s convenience as an oral suspension and twice‑daily capsule dosing.
Main Outcomes
Short‑term clinical efficacy for uncomplicated sinusitis and pharyngitis was similar between oral third‑generation cephalosporins in international meta‑analyses from 2023–24.
Studies underscored the antimicrobial‑resistance risk when these agents are used indiscriminately.
Australian data support targeted cefdinir use aligned with local susceptibility patterns and stewardship guidance.
Clinicians are advised to check ARTG and PBS listings for current approvals and subsidy status before prescribing or stocking cefdinir.
Safety Observations (TGA Reports)
TGA pharmacovigilance summaries from 2022–25 highlighted antibiotic‑associated diarrhoea and rare hypersensitivity events associated with cephalosporins broadly.
No new Australia‑specific contraindications for cefdinir were flagged in that period.
Reports emphasised vigilance for severe diarrhoea that could indicate Clostridioides difficile infection.
Pharmacists and prescribers should continue to report adverse events to the TGA Adverse Event Reporting System.
Clinical Mechanism Of Action
Layman’s Explanation
People commonly wonder how cefdinir actually works against infections.
Cefdinir is an oral third‑generation cephalosporin antibiotic that weakens bacterial cell walls so the bacteria cannot survive.
The weakened cell wall causes the bacteria to break apart and die, which helps resolve infections when the bug is susceptible.
Cefdinir is mainly used for common respiratory infections and some uncomplicated skin infections.
Scientific Breakdown
Cefdinir is classified under the ATC code J01DD15 as a systemic third‑generation cephalosporin.
It binds to penicillin‑binding proteins (PBPs) and inhibits peptidoglycan crosslinking during bacterial cell‑wall synthesis.
The result is a bactericidal effect against susceptible pathogens, particularly many Gram‑positive respiratory organisms and some Gram‑negative enteric organisms.
Activity can be reduced by extended‑spectrum beta‑lactamases and other resistance mechanisms.
Formulations include 300 mg capsules and reconstitutable suspensions of 125 mg/5 mL and 250 mg/5 mL.
Oral bioavailability is moderate and elimination is predominantly renal, so dose adjustment is required when creatinine clearance is under 30 mL/min by extending the dosing interval to every 24 hours.
An important interaction is with oral iron, which can cause red stool discolouration in children and reduce cefdinir absorption.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Clinicians often want to know which infections cefdinir is approved to treat and whether it is subsidised.
Approved indications based on international product information and common practice include community‑acquired pneumonia, acute maxillary sinusitis, pharyngitis/tonsillitis, acute exacerbations of chronic bronchitis and uncomplicated skin infections.
Typical adult dosing is 300 mg every 12 hours, with some indications allowing 600 mg once daily.
Paediatric dosing is weight‑based and commonly approximates 14 mg/kg/day divided or 7 mg/kg every 12 hours, with a maximum of 600 mg/day.
In Australia, clinicians must verify current TGA ARTG entries and PBS listings before prescribing or stocking cefdinir.
Cefdinir is a prescription‑only medicine and PBS subsidy varies by indication and listing status.
Notable Off‑Label Trends In Australian Practice
Off‑label use is typically selective and guided by allergy, prior antibiotic failure or local susceptibility data.
Some general practitioners use cefdinir suspension for paediatric otitis media or sinusitis when amoxicillin is unsuitable.
It is also chosen for certain outpatient infections in penicillin‑allergic patients when narrow alternatives are unsuitable.
Antimicrobial stewardship guidance encourages confirmation of clinical need and using the shortest effective duration when cefdinir is used off‑label.
Dosage Strategy
General Dosing
Common dosing questions usually centre on how to give cefdinir to adults and children safely.
Adults and adolescents aged 13 and over commonly receive capsules of 300 mg every 12 hours.
Some indications allow 600 mg once daily as an alternative regimen.
Paediatric dosing uses the 125 mg/5 mL or 250 mg/5 mL suspension and is weight‑based with a maximum of 600 mg per day.
For renal impairment with creatinine clearance less than 30 mL/min, extend the dosing interval to every 24 hours.
Elderly patients do not require routine adjustment unless renal function is impaired.
Condition‑Specific Dosing (PBS Recommendations)
Dosages and durations differ by condition and by product information.
Community‑acquired pneumonia commonly uses 300 mg every 12 hours for 10 days in adults and 14 mg/kg/day divided for children for 10 days.
Acute maxillary sinusitis and uncomplicated skin infections are often treated with 300 mg every 12 hours for 10 days.
Pharyngitis/tonsillitis regimens may be 300 mg every 12 hours or 600 mg once daily for 5–10 days.
Acute exacerbations of chronic bronchitis are typically 300 mg every 12 hours for 5–10 days.
PBS subsidy varies according to indication and prescriber criteria, so check the PBS schedule for eligibility before assuming subsidy applies.
When using suspension, counsel carers on accurate dose measurement with an oral syringe and the 10‑day discard rule after reconstitution.
Safety Protocols
Contraindications (Australian Guidelines)
Safety screening is a central pharmacist task before supply.
Absolute contraindications include known allergy to cefdinir or other cephalosporins and prior severe beta‑lactam hypersensitivity.
Relative cautions include documented penicillin allergy where cross‑reactivity should be assessed, renal impairment that requires dose adjustment, and a history of significant gastrointestinal disease such as previous C. difficile colitis.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects are gastrointestinal and usually mild to moderate.
Reported events include diarrhoea, nausea, vomiting and abdominal pain.
Other effects include headache, rash and vaginal candidiasis.
In children, red stool discolouration can occur with concomitant iron; this is benign but alarming to parents and should be pre‑warned.
TGA reports from 2022–25 record rare serious hypersensitivity and antibiotic‑associated diarrhoea, which may indicate C. difficile and requires urgent review.
Pharmacists should screen for allergies, advise on warning signs and report suspected adverse events to the TGA.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Patients commonly ask whether they can take cefdinir with food or alcohol.
Food has limited clinically important effect on cefdinir absorption, so it may be taken with or without food for tolerability.
There is no alcohol‑specific pharmacological interaction, but alcohol can worsen gastrointestinal upset while taking antibiotics.
Advise patients to avoid excessive alcohol while unwell and taking antibiotics due to reduced tolerance and hydration concerns.
Drug Combinations To Avoid (TGA Safety Alerts)
The most important interaction to highlight is with oral iron products and iron‑containing formula in children.
Concurrent iron can reduce cefdinir absorption and cause red stool discolouration that looks like blood but is not.
Recommend separating iron and cefdinir doses by at least two to three hours where possible.
No major cytochrome P450 interactions are reported with cefdinir.
Coadministration with probenecid can alter renal excretion and may require monitoring.
Avoid combining multiple nephrotoxic agents in patients with renal impairment without appropriate monitoring.
Refer to ARTG product information and local interaction checkers such as MIMS or AusDI when in doubt.
Patient Experience Analysis
Australian Survey Data
Patients frequently prioritise price, taste for paediatric suspensions and clear dosing instructions.
Survey data and pharmacy feedback show high reliance on pharmacist counselling when patients receive antibiotics.
Concerns commonly raised include private cost when a medicine is not PBS‑subsidised and how to measure suspension doses accurately.
Adherence improves when pharmacists provide practical demonstration with an oral syringe and written dosing schedules.
Forum And Pharmacy Trends
Online forums and pharmacy comments repeatedly mention convenience of twice‑daily dosing as helpful for adherence.
Parents often report diarrhoea or red stool discolouration when cefdinir is taken with iron and appreciate clear pre‑warning from pharmacists.
Rural and remote patients sometimes face intermittent stock and rely on pharmacists to arrange e‑scripts or sourcing from alternate wholesalers.
Major chains list generics variably, and online pharmacies plus telehealth have increased access since 2020.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Availability of cefdinir in Australia varies by supplier and ARTG registration of specific products.
Major chains such as Chemist Warehouse, Priceline and TerryWhite may stock generic cefdinir when supplied by wholesalers.
Rural pharmacies often report intermittent supply and rely on wholesalers for allocations and parallel imports where permitted.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth consultations and e‑prescriptions have made it easier for patients to access antibiotics nationwide.
Online pharmacies offer national dispensing and can deliver to remote addresses subject to prescription requirements and PBS rules.
In our online pharmacy, omnicef is available without a prescription, with discreet delivery to Australia in 5–14 days.
PBS Vs Private Cost Comparisons
Whether a patient pays the PBS copayment or a private price depends on PBS listing for the indication and prescriber criteria.
If cefdinir is not PBS‑listed for a patient’s indication, private costs vary considerably between chains and online retailers.
Pharmacists should check PBS eligibility, discuss cheaper effective alternatives such as cefalexin or amoxicillin/clavulanate when appropriate, and document any supply issues for the prescriber.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
Clinicians often ask what competitors exist if cefdinir is unavailable or unsuitable.
- Cefalexin: First‑generation cephalosporin; widely PBS‑subsidised for many indications and useful for skin infections.
- Cefuroxime: Second‑generation cephalosporin; alternative for some respiratory infections.
- Cefixime: Third‑generation oral cephalosporin; similar class but different pharmacokinetics.
- Amoxicillin/Clavulanate (Augmentin): Broadly PBS‑subsidised and often first‑line for many community infections.
- Azithromycin: Macrolide used when penicillin allergy is present, subject to stewardship considerations.
Pros And Cons Checklist
When choosing an alternative, consider these practical points.
- Confirm pathogen susceptibility or guideline alignment before selecting a third‑generation agent.
- Screen allergy history carefully, particularly for penicillin and severe beta‑lactam reactions.
- Assess renal function and need for dose adjustment.
- Consider PBS subsidy and patient affordability when suggesting an alternative.
- Prefer narrow‑spectrum agents where clinically appropriate to reduce resistance pressure.
Regulatory Status
TGA Approval Framework
The Therapeutic Goods Administration regulates medicine approvals and ARTG listings in Australia.
Manufacturers or sponsors must submit clinical, quality and safety data for ARTG entry.
Clinicians and pharmacists should verify current ARTG entries and product‑specific information before ordering stock or dispensing cefdinir.
PBS Subsidy Process
The Pharmaceutical Benefits Scheme requires an economic and clinical case for listing and subsidy for specific indications.
Cefdinir may or may not be PBS‑listed for particular uses, so check the PBS schedule for current entries and prescriber criteria.
If not listed, patients will pay a private price and prescribers cannot claim a PBS subsidy unless criteria are met.
Consolidated FAQ
Here are common patient questions pharmacists hear about omnicef in Australia.
Q1: Is Omnicef available on the PBS?
A1: Check the PBS schedule and the TGA ARTG for current listings, because cefdinir is not universally PBS‑subsidised for all indications.
Q2: Can my child take iron with cefdinir suspension?
A2: Separate iron and cefdinir by two to three hours to reduce interaction and avoid red stools and reduced absorption.
Q3: What if I have a penicillin allergy?
A3: Discuss with your prescriber because cephalosporin cross‑reactivity is lower than historically thought but depends on prior reaction severity; alternatives such as azithromycin or doxycycline may be preferable in some cases.
Q4: How long is a typical course?
A4: Most outpatient regimens last 5–10 days, with pneumonia and some skin infections often treated for 10 days.
Q5: What should pharmacists counsel on?
A5: Counsel on accurate dose measurement for suspensions, reconstitution and 10‑day discard rule, allergy screening, renal dosing, and when to seek urgent review for severe diarrhoea or allergic reaction.
Visual Guide
Clinics and pharmacies often want quick printable handouts for patients and staff.
Suggested infographic topics are practical and reference TGA/PBS guidance where possible.
- “Cefdinir At A Glance” showing INN, forms (300 mg capsule; 125/250 mg per 5 mL suspension), adult and paediatric dosing ranges and renal adjustment.
- “PBS Vs Private Cost” flowchart advising to check PBS eligibility and compare alternatives where not subsidised.
- “Pharmacy Distribution Map” highlighting likely availability in metro versus rural pharmacies and actions if stock is unavailable.
- “Parent Handout” on reconstitution, measuring dose with an oral syringe, iron interaction and the 10‑day discard rule.
Storage & Transport
Household Storage Under Australian Climate
Patients commonly store medicines in unpredictable conditions, so provide clear advice.
Capsules should be stored at 20–25°C in a dry place and protected from heat and sunlight.
The oral suspension powder should be stored dry until reconstitution.
After reconstitution, store the suspension at 20–25°C and discard after 10 days.
In hot Australian climates, advise carers not to leave bottles in cars or in direct sun and to use insulated bags for short transport if ambient temperatures are very high.
Cold‑Chain Logistics For Pharmacies
Cefdinir does not require cold‑chain storage, but excessive heat during distribution can degrade some products.
Pharmacies and wholesalers should follow labelled storage temperatures and check batches on receipt for integrity and expiry.
Remote pharmacies should maintain buffer stock and supplier contacts to manage intermittent supply.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Pharmacist counselling should be practical, empathetic and focused on adherence and safety.
Confirm the clinical indication, check allergy history and renal function before supply.
Demonstrate measuring the suspension dose using an oral syringe and provide written instructions for dosing times and duration.
Warn about the iron interaction and red stool in children and advise separating doses by two to three hours.
Explain the 10‑day discard rule after reconstitution and advise when to seek urgent care for severe diarrhoea or allergic signs.
National Health Authority Recommendations
National stewardship resources and TGA guidance support using narrower‑spectrum agents where clinically appropriate.
Prescribers should align choice of cefdinir with local susceptibility data and therapeutic guidelines.
Where supply problems occur, pharmacists should liaise with prescribers regarding alternative PBS‑listed options and report adverse events to the TGA.
Surveillance data from 2022–25 emphasise reserving oral third‑generation cephalosporins for targeted use to limit resistance.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
Storage & Transport Practicalities
Pharmacists should check batch numbers and expiry dates before supply and counsel patients on proper storage.
Advise patients to keep capsules in a cool, dry place and the suspension out of direct sunlight and heat after reconstitution.
For transport from pharmacy to home in hot weather, suggest insulated bags for short periods rather than leaving products in cars.
Guidelines For Proper Use
Follow a consistent counselling routine to reduce errors and improve outcomes.
Use an oral syringe for suspensions and demonstrate dose volumes to carers.
Record allergy status and verify renal function where indicated.
Encourage completing the full course as prescribed to prevent resistance and recurrence.
Concluding Notes For Clinicians And Pharmacists
Cefdinir is a useful oral third‑generation cephalosporin with specific respiratory and skin infection indications.
Recent surveillance and meta‑analytic data from 2022–25 stress stewardship and targeted use rather than routine broad use.
Adverse events are mostly gastrointestinal, with rare serious hypersensitivity events reported to the TGA.
Pharmacists play a key role in screening, counselling, ensuring accurate dosing and reporting adverse events.
Always check ARTG product information and the PBS schedule before prescribing or supplying cefdinir and consider cheaper, narrower alternatives where clinically appropriate.
Frequently Asked Questions
These short answers cover the questions patients call or message the pharmacy about most often.
Is cefdinir safe for children?
Cefdinir suspension is commonly used in paediatrics with weight‑based dosing up to 600 mg/day, but warn parents about iron interaction and red stool.
What should I do if my child has red stools?
Reassure parents that red stool can be caused by the interaction between cefdinir and iron and is not blood, but advise contacting a clinician if there are other concerning signs.
Can I buy Omnicef online?
Check prescription and PBS requirements first, and ask your pharmacist about private pricing and legitimate online suppliers if a prescription is provided.
How is overdose managed?
Overdose causes primarily gastrointestinal upset and possible seizures; supportive care and consideration of haemodialysis for severe cases in renal impairment are noted in product information.
When should I revisit the GP?
If symptoms worsen, fail to improve within 48–72 hours, or severe diarrhoea or signs of allergic reaction occur, return for reassessment promptly.
Quick References For Pharmacy Staff
Keep these practical checks in the dispensary to ensure safe supply.
- Confirm indication and PBS eligibility before dispensing.
- Screen and document allergy history; clarify any prior severe beta‑lactam reactions.
- Demonstrate suspension reconstitution and use an oral syringe for dose measurement.
- Warn about iron interaction and the 10‑day discard rule after reconstitution.
- Report suspected serious adverse events to the TGA.