
Prandin
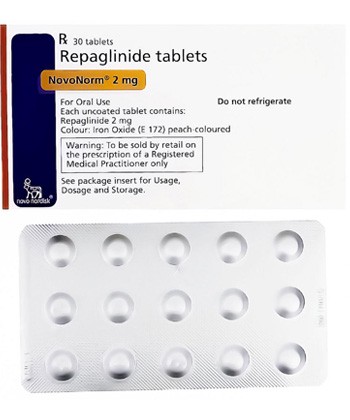
Prandin
- In our pharmacy, you can buy prandin without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Prandin (repaglinide) is used to treat type 2 diabetes mellitus as an adjunct to diet and exercise; it is a rapid‑acting insulin secretagogue in the meglitinide (glinide) class that stimulates pancreatic insulin release to reduce post‑meal glucose spikes.
- The usual adult dose is 0.5 mg orally with each main meal if HbA1c <8%, or 1 mg with each main meal if HbA1c ≥8%; dose may be titrated weekly up to 4 mg per meal and a total daily maximum of 16 mg. Not established for children; use caution and dose adjustment in the elderly and in renal or hepatic impairment.
- Form of administration: oral tablets (0.5 mg, 1 mg, 2 mg), taken just before meals (0–30 minutes prior).
- Onset time: rapid onset, typically within 15–30 minutes after dosing.
- Duration of action: short‑acting; glucose‑lowering effect generally lasts about 4–6 hours, targeting mealtime glucose excursions.
- Alcohol warning: avoid alcohol as it can increase the risk of hypoglycaemia and may mask hypoglycaemic symptoms; monitor blood glucose closely if alcohol is consumed.
- The most common side effect is hypoglycaemia; other frequent adverse effects include headache, upper respiratory tract infections, back pain and gastrointestinal upset.
- Would you like to try prandin without a prescription?
Basic Prandin Information
- INN (International Nonproprietary Name): Repaglinide
- Brand Names Available In Australia: Not specified
- ATC Code: A10BX02
- Forms & Dosages: Tablets 0.5 mg, 1 mg, 2 mg
- Manufacturers In Australia: Not specified
- Registration Status In Australia: Not specified
- OTC / Rx Classification: Prescription only (Rx)
Major 2022–2025 Australian & Global Studies
Worried that there’s been a big new trial you’ve missed on repaglinide?
Recent literature from 2022 to 2025 shows there have been few large new randomised controlled trials focused on repaglinide specifically.
Most contemporary evidence for the meglitinide class comes from meta-analyses and observational cohort studies rather than fresh, large RCTs.
Those analyses tend to compare meglitinides with sulfonylureas, DPP-4 inhibitors and SGLT2 inhibitors for type 2 diabetes control.
Cardiovascular and renal outcome trials for newer drug classes dominate the field and have indirectly reduced repaglinide uptake in many settings.
Australian-specific data remain sparse in the peer-reviewed record for 2022–2025.
State-based registries and GP prescribing audits carried out between 2022 and 2024 report declining prescriptions in urban centres in Australia.
Prescribers still use repaglinide occasionally for patients intolerant of metformin or where postprandial hyperglycaemia is the main problem.
Pharmacy audit data and practice surveys indicate a trend away from meglitinides towards once-daily or cardiorenal-benefit agents.
Main Outcomes
Are meglitinides still useful for meal-time sugar control?
Consistent signals across recent reviews are that repaglinide effectively reduces post-meal glucose excursions.
The drug’s short onset and offset profile makes it suitable for people with irregular meals or shift work patterns.
No contemporary large trial has altered the safety and tolerability profile that was established before the 2000s.
Clinical use today is therefore often targeted and individualised rather than first-line in most guidelines.
Safety Observations (TGA Reports)
What safety flags should Australian patients and clinicians watch?
Post-market surveillance identifies hypoglycaemia as the principal risk with repaglinide, particularly when combined with other insulin secretagogues or insulin itself.
Severe hypoglycaemia reports often involve interacting drugs such as gemfibrozil or circumstances of reduced oral intake.
Regulators advise caution in hepatic impairment because repaglinide is primarily metabolised in the liver.
Australians should check TGA safety alerts and local pharmacovigilance entries for any updates when counselling patients.
Layman’s Explanation
What does repaglinide actually do when you take it?
Repaglinide is a rapid-acting oral medicine from the meglitinide family that helps the pancreas release insulin around mealtimes.
The tablet is taken just before a meal – typically 0 to 30 minutes beforehand – to blunt the rise in blood sugar after food.
That makes it a good option for people who struggle most with postprandial glucose rather than fasting glucose.
Think of it as a short, targeted boost of insulin release that follows the rhythm of meals rather than a continuous basal effect.
Scientific Breakdown
How does repaglinide work on a molecular level?
Repaglinide binds to ATP-sensitive potassium channels (KATP) on pancreatic beta cells at a site adjacent to where sulfonylureas bind.
Its association and dissociation kinetics are faster than sulfonylureas, producing a rapid but short-lived insulin release.
Clinical products are available in 0.5 mg, 1 mg and 2 mg tablet strengths for per-meal titration.
Pharmacokinetics Highlights
The drug is rapidly absorbed and has a short half-life, which supports dosing with each main meal.
Hepatic metabolism is the main elimination route and is therefore relevant to dosing adjustments and contraindications.
Australian Approvals (TGA-Listed, PBS Inclusion)
Can Australians assume global approvals equal local subsidy?
Internationally, repaglinide was approved by the FDA in 1997 and is authorised in regions such as the EU and Canada under names like NovoNorm and Gluconorm.
Clinicians and pharmacists in Australia must verify current ARTG listing and PBS subsidy status via official TGA and PBS portals before supply or counselling.
Historically, repaglinide’s role has been as an adjunct to diet and exercise for type 2 diabetes with a focus on mealtime glucose control.
PBS subsidy has been less prominent for repaglinide compared with metformin and many newer agents, so always check the PBS online for current subsidy status.
Notable Off-Label Trends In Australian Practice
Do Australian clinicians use repaglinide outside its registered indications?
Common off-label clinical uses include substitution for sulfonylureas in people with erratic meals.
Other pragmatic uses are short-term bridging where insulin initiation is delayed, and cautious low-dose titration in frail elderly patients.
All off-label decisions should weigh contraindications, notably the interaction with gemfibrozil, and be documented in the patient record.
General Dosing
How should a typical adult start repaglinide?
Starting dose advice in product information is 0.5 mg orally with each main meal if HbA1c is under 8%.
For HbA1c at or above 8%, initial dosing can start at 1 mg with each main meal.
Doses may be titrated weekly up to a single dose of 4 mg and a total daily maximum of 16 mg according to glycaemic response.
The tablet is taken 0 to 30 minutes before food and should be skipped if that meal is omitted.
Condition-Specific Dosing (PBS Recommendations)
What adjustments should prescribers consider for special populations?
When PBS rules apply, prescribers must follow authority and indication criteria for subsidy where relevant.
In renal impairment start at the lowest dose of 0.5 mg and titrate carefully while monitoring for hypoglycaemia.
In elderly patients exercise caution due to higher hypoglycaemia risk and check renal and hepatic function before up-titration.
Repaglinide is contraindicated in severe hepatic impairment and should be used cautiously in mild to moderate liver disease.
Consider SMBG or CGM for patients at higher risk while titrating treatment.
Contraindications (Australian Guidelines)
Who should not take repaglinide?
Repaglinide is contraindicated in type 1 diabetes and in diabetic ketoacidosis.
Do not give it to patients with known hypersensitivity to repaglinide or any excipients in the product.
Concurrent prescription of gemfibrozil is a specific contra-indication because of documented severe hypoglycaemia risk.
Always cross-check hospital formularies and the TGA for full contraindication lists.
Adverse Effects (Post-Market Pharmacovigilance)
What side effects do patients report in Australia and abroad?
Hypoglycaemia is the principal safety concern and must be covered in counselling every time the medicine is supplied.
Other common adverse events include headache, upper respiratory tract symptoms and back pain.
Moderate effects can include gastrointestinal upset and arthralgia.
Pharmacovigilance guidance recommends prompt reporting of serious events to the TGA safety-watch system.
Food Interactions (Alcohol, Coffee, Diet In Australia)
How does food or drink change repaglinide’s effect?
Repaglinide is intended to be taken with a meal so skipping meals increases hypoglycaemia risk and the dose should be skipped if the meal is missed.
Alcohol potentiates hypoglycaemia and should be limited or avoided when taking repaglinide.
High-carbohydrate meals common in many Australian diets may necessitate closer monitoring of blood glucose and possible dose adjustments.
Caffeine does not have a direct interaction but may mask symptoms of low blood sugar for some patients.
Drug Combinations To Avoid (TGA Safety Alerts)
Which medicines are unsafe to combine with repaglinide?
Co-administration with gemfibrozil is contraindicated because it can cause severe and prolonged hypoglycaemia.
Strong CYP3A4 inhibitors or inducers and drugs that alter hepatic clearance require a cautious review of dosing and monitoring.
Combining repaglinide with other insulin secretagogues or insulin increases the risk of hypoglycaemia and generally should be avoided unless closely supervised.
Clinicians should check the TGA and ARTG regularly for updated interaction notices.
Australian Survey Data
Do patients like taking repaglinide?
Primary care surveys and pharmacy audits in Australia between 2022 and 2024 show mixed patient persistence with repaglinide.
Patients commonly report better control of post-meal glucose but also cite hypoglycaemia concerns and the inconvenience of multiple daily dosing.
Cost and PBS subsidy status influence adherence, with rural communities more likely to report price-related switching.
Forum And Pharmacy Trends
What do pharmacists and online forums say about prandin?
Pharmacists in chains and independent rural pharmacies emphasise correct meal timing, hypoglycaemia recognition and checking for interacting medicines.
Online forums show price sensitivity and consumer interest in generics or searching for terms like prandin 1 mg price.
Pharmacists often use e-scripts and telehealth to correct misinformation and provide adherence aids for those on per-meal dosing.
For shift workers or those who share meals, per-meal flexibility can be either very helpful or impractical depending on routines.
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where can Australians expect to get repaglinide?
Prandin and generic repaglinide circulate internationally but availability in Australia varies by supplier and ARTG listing.
Large chains source generics where available but stock levels differ between metropolitan and regional stores.
Rural pharmacies may need to plan ahead and use buffer stocks to maintain supply.
Online Pharmacy Growth And Telehealth E-Scripts
Is it safe to order prandin online?
Online pharmacies and telehealth e-scripts make access easier but increase the need for careful interaction checks and pharmacist review.
Consumers frequently search to buy Prandin online and compare prices, which can lead to mismatched expectations about prescription status.
In our online pharmacy, prandin is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
How much will repaglinide cost out of pocket?
PBS listing status changes and clinicians should check the PBS website for up-to-date subsidy information before advising patients.
When unsubsidised, out-of-pocket costs can be significant and encourage switching to PBS-listed alternatives such as metformin or some sulfonylureas.
Rural patients often face both supply and cost barriers and rely on pharmacists to source affordable generics where possible.
Comparison Table Of PBS And Non-PBS Options
Which alternatives should GPs and pharmacists consider?
Alternatives to repaglinide include sulfonylureas such as gliclazide and glipizide, the meglitinide nateglinide, DPP-4 inhibitors like sitagliptin, SGLT2 inhibitors and metformin.
PBS coverage and authority requirements vary by drug, and choice should balance postprandial efficacy, hypoglycaemia risk, cardiovascular or renal benefit, and cost.
Pros And Cons Checklist
- Pros: Rapid onset, meal-tied flexibility and useful for irregular eaters.
- Cons: Multiple daily dosing, hypoglycaemia risk, hepatic metabolism concerns and interactions such as with gemfibrozil.
TGA Approval Framework
How is repaglinide regulated in Australia?
Prescription medicines require ARTG listing after TGA assessment in Australia and clinicians should verify current ARTG entries before supply.
International approvals such as FDA (1997) and EMA support repaglinide’s regulatory history but do not replace local verification.
PBS Subsidy Process
How does a medicine get subsidised in Australia?
PBS listing decisions come after PBAC assessment of clinical need and cost-effectiveness, and applications are reviewed formally.
Where repaglinide is not PBS-listed, clinicians may prescribe privately or seek individual patient access pathways if appropriate.
Local health services and hospital formularies can vary, so always confirm local policy.
Consolidated FAQ (Australian Context)
Q1: Can I take repaglinide if I skip meals?
A: No — skip the dose for that meal and do not double the next dose.
Q2: Is repaglinide on the PBS?
A: PBS status changes; check the PBS website or ask your pharmacist for current subsidy details.
Q3: What if I take gemfibrozil?
A: Co-administration is contraindicated due to severe hypoglycaemia risk — inform prescribers and pharmacists immediately.
Q4: How should I store repaglinide at home?
A: Store at 25°C with permitted excursions 15–30°C, protect from moisture and heat and keep in the original packaging.
Q5: Who should avoid repaglinide?
A: People with type 1 diabetes, diabetic ketoacidosis, severe hepatic impairment or known hypersensitivity should avoid repaglinide.
Infographic Concepts
Would a visual help patients remember dosing and safety?
Infographic 1 could show “How Repaglinide Works” with a timeline illustrating 0–30 minute pre-meal dosing, a rapid insulin spike and short duration, plus tablet strengths 0.5/1/2 mg and ATC A10BX02.
Infographic 2 might compare “PBS Vs Private Cost” in a flowchart checking PBS rules, authority requirements and private prescription pathways with major pharmacy chains listed as sourcing options.
Infographic 3 should be a “Hypoglycaemia Action Plan” showing symptoms, fast sugar choices and when to call emergency services, with pharmacist contact points highlighted for rural communities.
Household Storage Under Australian Climate
How should people store repaglinide in an Aussie home?
Store tablets at 25°C with permitted excursions between 15°C and 30°C and protect them from moisture and heat.
Avoid storing tablets in bathrooms or cars where humidity and temperature can exceed recommended ranges.
Keep medicine in original blister packs or bottles with expiry dates visible and follow pharmacist labelling.
Cold-Chain Logistics For Pharmacies
Does repaglinide need refrigeration during transport?
No special refrigeration is required, which simplifies supply chain handling for pharmacies.
Pharmacies must still monitor ambient storage, practice good stock rotation and confirm supplier ARTG details when ordering.
Rural pharmacies should plan buffer stocks and verify packaging and batch information for products labelled as Prandin, NovoNorm or local generics.
Pharmacist Counselling Style In Australia
How should pharmacists explain repaglinide to patients?
First, verify the indication and recent blood glucose or HbA1c results with the prescriber if needed.
Explain the per-meal timing of 0–30 minutes preprandial and stress that missing a meal means skipping the dose for that meal.
Cover hypoglycaemia recognition and management, check for gemfibrozil or other interacting medicines and discuss safe storage and expiry.
Offer adherence aids such as dose organisers and liaise with the GP for dose titration and monitoring plans.
National Health Authority Recommendations
Which guidelines should clinicians follow?
Follow TGA, PBS and RACGP guidance when managing type 2 diabetes and when selecting medicines for postprandial control.
Use repaglinide primarily where it is clinically indicated for mealtime control and avoid it in type 1 diabetes and DKA.
Report adverse events to the TGA and tailor therapy based on comorbidities, liver and kidney function, and patient lifestyle.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Ballarat | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
Who Should Consider Alternatives
Which patients might be better served by a different medicine?
Patients with high cardiovascular or renal risk often receive SGLT2 inhibitors or GLP-1 agonists instead because of proven cardiorenal benefits.
People with unreliable mealtimes may still favour repaglinide, but those who prefer once-daily dosing often switch to DPP-4 inhibitors or long-acting agents.
Patients with significant hepatic impairment should avoid repaglinide and discuss alternatives with their GP.
Practical Counselling Examples
Here are short, real-world counselling scenarios you can use in practice.
Example 1: A 68-year-old patient with erratic appetite and mild renal impairment starts at 0.5 mg with main meals and uses SMBG twice daily during titration.
Example 2: A shift worker who eats irregularly finds repaglinide useful when doses are taken strictly before each meal and carries fast-acting glucose for lows.
Example 3: A rural patient asks about cost and subsidy; the pharmacist checks PBS status, offers a generic source and arranges delivery within the usual lead time.
Reporting And Follow-Up
What follow-up should pharmacists and prescribers arrange?
Arrange blood glucose monitoring and review within weeks of initiation and after each dose change.
Document any hypoglycaemic episodes and consider dose reduction or therapy change if they recur.
Report serious adverse reactions to the TGA and keep clear notes in the patient’s record for continuity of care.
Key Takeaway For Patients
If your main concern is post-meal sugar spikes, repaglinide is a targeted option that works quickly around mealtimes.
It does require multiple daily dosing, careful timing with meals and close attention to hypoglycaemia risk, especially with interacting medicines or alcohol.
Always check with your GP and pharmacist before switching or starting therapy and confirm local subsidy status through PBS if cost is a concern.