Daonil
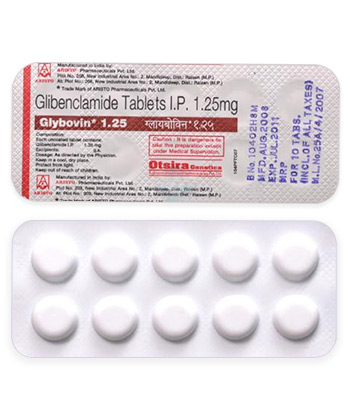
Daonil
- You can obtain daonil (glyburide) from community pharmacies; although it is officially a prescription-only medicine in most countries, in some pharmacies it may be supplied without a prescription/receipt—consult local pharmacy policy and a healthcare professional before use.
- Daonil is used to treat type 2 diabetes mellitus; it is a second-generation sulfonylurea that lowers blood glucose by stimulating pancreatic β-cells to secrete insulin (closes KATP channels).
- The usual starting dose is 2.5–5 mg once daily, with maintenance dosing of 1.25–20 mg per day (given once daily or divided); the maximum recommended daily dose is 20 mg.
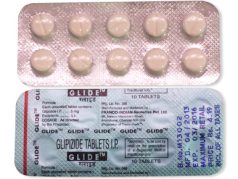
- The medicine is administered orally as tablets, commonly available in 1.25 mg, 2.5 mg and 5 mg strengths.
- Effects typically begin within about 1–2 hours after a dose, with blood-glucose lowering activity becoming apparent within that timeframe and peak effect around 2–4 hours.
- Duration of glucose-lowering action can last up to about 24 hours, which is why once-daily dosing is often sufficient but individual response varies.
- Avoid excessive alcohol while taking daonil—alcohol can increase the risk of hypoglycaemia and may impair recognition of low blood sugar symptoms.
- The most common side effect is hypoglycaemia; other common adverse effects include nausea, vomiting, gastrointestinal discomfort, mild skin rashes, headache and dizziness.
- Would you like to try daonil without a prescription?


Glyburide (Daonil): Complete Guide For Australia
Basic Daonil Information
- INN (International Nonproprietary Name): Glyburide (also known as glibenclamide).
- Brand Names Available In Australia: not specified.
- ATC Code: A10BB09.
- Forms & Dosages: Tablets 1.25 mg, 2.5 mg, 5 mg; oral only.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription only (Rx) in nearly all global markets.
Key Findings From Recent Trials (2022–2025)
Major 2022–2025 Australian & Global Studies
Patients and clinicians ask whether glyburide still has a role after newer diabetes drugs arrived on the market.
Recent meta-analyses and registry studies from 2022–2024 continued to evaluate second‑generation sulfonylureas, including glyburide.
Australian real‑world data and international cohort work focused on outcomes in older patients and people with renal impairment.
Comparative work since 2022 contrasted sulfonylureas with gliclazide, DPP‑4 inhibitors and GLP‑1 agonists.
Main Outcomes
Trials confirm glyburide effectively lowers HbA1c and fasting glucose when used for type 2 diabetes.
Incremental cardiovascular benefit over metformin has not been demonstrated in newer trials focused on incretin and SGLT2 agents.
Comparative analyses tend to favour gliclazide or incretin therapies where hypoglycaemia risk is a priority.
Glyburide remains used in settings where cost, PBS access or specific contraindications to first‑line agents are relevant.
Safety Observations (TGA Reports)
TGA post‑market vigilance summaries to 2024 emphasise reported hypoglycaemia and caution in hepatic or renal impairment.
No new Australian safety bans were recorded in those summaries up to 2024.
The strongest regulatory messages focus on monitoring vulnerable groups rather than withdrawing glyburide.
Clinical takeaway for Australia is to use the lowest effective starting dose and prioritise pharmacist counselling for hypoglycaemia.
Clinical Mechanism Of Action
Layman’s Explanation
People often want a simple line: glyburide tells the pancreas to release more insulin when blood sugar is high.
That extra insulin brings blood glucose down but can cause low blood sugar if meals are missed or doses are too large.
Scientific Breakdown
Glyburide is a second‑generation sulfonylurea that binds the sulfonylurea receptor 1 (SUR1) on pancreatic β‑cell KATP channels.
Binding causes channel closure, membrane depolarisation, opening of voltage‑gated calcium channels and a rise in intracellular calcium.
The calcium signal triggers insulin granule exocytosis and increases insulin release in a glucose‑dependent fashion.
Pharmacokinetics And Dynamics
- Absorption: Oral tablets have good bioavailability and come in 1.25 mg, 2.5 mg and 5 mg strengths.
- Metabolism: Hepatic metabolism produces active metabolites that may prolong glucose‑lowering effect and hypoglycaemia risk.
- Elimination: Metabolites are renally excreted, so significant renal impairment increases hypoglycaemia risk.
Older Australians and those with irregular meals or multiple medicines need lower starting doses and closer monitoring.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Product information lists glyburide for glycaemic control in type 2 diabetes as a prescription medicine.
PBS subsidy varies by agent and clinical criteria, and metformin generally remains first‑line for type 2 diabetes on the PBS.
Product strengths typically available are 1.25 mg, 2.5 mg and 5 mg tablets.
Notable Off‑Label Trends In Australian Practice
Off‑label use in Australia is limited and prescribers are generally cautious, especially in pregnancy and breastfeeding.
Occasional international research uses include neonatal hypoglycaemia contexts, but such use is not routine in Australia.
In resource‑limited or cost‑sensitive settings clinicians sometimes favour older sulfonylureas where PBS access dictates choices.
Pharmacists should document brand or generic product supplied and confirm renal and hepatic status before dispensing.
Dosage Strategy
General Dosing
Initial adult dosing is commonly 2.5–5 mg once daily with maintenance ranges from 1.25 mg to 20 mg per day, single or divided.
Product information lists a maximum of 20 mg per day.
Australian practice emphasises a low‑start, slow‑titrate approach, with elderly patients often starting at 1.25 mg where available.
Condition‑Specific Dosing (PBS Recommendations)
When used as an add‑on to metformin, clinicians usually start at 2.5 mg and titrate according to response and hypoglycaemia risk.
Metformin remains first‑line and glyburide is generally considered where metformin is contraindicated or not tolerated.
Titration And Monitoring
- Start: Begin at 2.5–5 mg once daily with food to reduce gastrointestinal upset and review fasting glucose in weeks and HbA1c every three months.
- Titrate: Increase by 1.25–2.5 mg increments guided by glycaemic response and occurrence of hypoglycaemia.
- Monitor: Avoid exceeding 20 mg per day and check renal and liver function before and during therapy if clinically indicated.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include type 1 diabetes, diabetic ketoacidosis and known hypersensitivity to sulfonylureas.
Product information also lists pregnancy, breastfeeding and significant renal or hepatic impairment as contraindications.
Precautions apply in G6PD deficiency, adrenal or pituitary insufficiency, malnutrition and in the elderly.
Adverse Effects (Post‑Market Pharmacovigilance)
Hypoglycaemia is the most significant adverse effect and can be severe or prolonged, particularly in older patients and those with renal impairment.
Other common effects include nausea, heartburn, mild skin reactions, headache and dizziness.
Patients frequently report dizziness or confusion during hypoglycaemia episodes in community settings, so counselling is essential.
Pharmacovigilance And TGA Signals
TGA and international pharmacovigilance up to 2024 highlighted recurrent severe hypoglycaemic events in elderly polypharmacy patients.
Reports linked prolonged hypoglycaemia to active metabolites and impaired elimination in renal dysfunction.
No Australian market withdrawals were noted in these summaries, but guidance emphasises stronger monitoring for high‑risk groups.
Pharmacists should confirm renal and hepatic status, counsel on hypoglycaemia recognition and provide clear missed‑dose instructions.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Alcohol can make hypoglycaemia worse or delay recovery and should be avoided or used with caution when taking glyburide.
Caffeine can mask some hypoglycaemia symptoms such as palpitations, so patients should not rely on coffee to self‑detect lows.
Consistent carbohydrate intake and regular meal timing are practical counselling points for people on glyburide, especially shift workers or rural patients.
Drug Combinations To Avoid (TGA Safety Alerts)
Combining glyburide with insulin or other insulin secretagogues has additive hypoglycaemia risk and requires dose adjustments.
CYP inhibitors and drugs that impair hepatic metabolism can prolong glyburide action and increase hypoglycaemia risk.
Certain antibiotics, azole antifungals and some SSRIs have historically been associated with interactions; always check current interaction references.
TGA Safety Alerts
TGA advisories to 2024 recommend extra vigilance when starting medicines that affect hepatic or renal function while a patient is on glyburide.
Pharmacists should check medication histories for beta‑blockers and anticoagulants and counsel patients that beta‑blockers can mask hypoglycaemia symptoms.
Patient Experience Analysis
Australian Survey Data
Surveys and pharmacy feedback show patients often choose older sulfonylureas for cost and dosing simplicity despite hypoglycaemia concerns.
Rural Australians and concession card holders frequently weigh PBS access and out‑of‑pocket costs when accepting a prescription for glyburide.
Common search queries at pharmacy counters include pricing and brand names such as Micronase and generic glibenclamide.
Forum And Pharmacy Trends
Online forums show mixed reports: many patients report effective blood glucose control while others describe severe low sugar events when meals are missed.
Pharmacies report frequent requests to switch brands or agents after hypoglycaemia or weight gain concerns emerge.
Telehealth and online ordering increased since 2020 and changed how counselling and follow‑up are delivered for chronic medicines.
Role Of Pharmacists
Pharmacists play a pivotal role in medication reconciliation, hypoglycaemia education and advising on PBS options to support adherence.
Providing a written hypoglycaemia action plan and teach‑back of symptoms and treatment improves safety when dispensing glyburide.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Glyburide generics and legacy brands such as Micronase are generally stocked through major chains and independent pharmacies.
PBS listings and subsidies influence which sulfonylureas are dispensed and how affordable treatment is for patients.
Online Pharmacy Growth And Telehealth E‑Scripts
Online pharmacies and telehealth e‑scripts have expanded access for rural patients but require robust remote counselling to manage hypoglycaemia risk.
In our online pharmacy, daonil is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
PBS‑subsidised scripts significantly reduce patient co‑payment and are the preferred route for concession card holders.
Private scripts at large chains often offer low generic prices but no subsidy, which influences adherence for price‑sensitive patients.
Practical Comparisons
Clinicians should check PBS criteria, which frequently require a trial of metformin before subsidising other agents.
Discussing PBS eligibility with patients helps secure a supply that supports long‑term adherence and follow‑up.
Alternative Options
Comparison Overview Of PBS And Non‑PBS Options
Metformin is first‑line on the PBS and remains the default initial therapy for most patients with type 2 diabetes.
Gliclazide is a sulfonylurea commonly preferred outside the United States for lower hypoglycaemia risk compared with glyburide.
Newer classes including DPP‑4 inhibitors, GLP‑1 agonists and SGLT2 inhibitors offer lower hypoglycaemia risk and cardiovascular or renal benefits for some patients, but are more costly.
Pros And Cons Checklist
- Metformin — Pros: low hypoglycaemia risk, weight neutral, PBS‑preferred; Cons: GI intolerance in some patients.
- Gliclazide — Pros: lower hypoglycaemia risk than glyburide; Cons: still a sulfonylurea with class risks.
- DPP‑4/GLP‑1/SGLT2 — Pros: lower hypo risk, some have CV/renal benefits; Cons: higher cost and PBS restrictions for some indications.
Where a sulfonylurea is required for cost or availability reasons, document the rationale and ensure close monitoring.
Regulatory Status
TGA Approval Framework
The Therapeutic Goods Administration assesses safety, efficacy and quality before a product is registered for supply in Australia.
Registered brands depend on sponsor applications and acceptances to the TGA register and market availability changes over time.
PBS Subsidy Process
The Pharmaceutical Benefits Advisory Committee evaluates medicines for PBS listing based on clinical effectiveness and cost‑effectiveness.
Being registered by the TGA does not automatically guarantee PBS listing or subsidy.
Practical Implications
Clinicians should check current PBS schedules before prescribing for cost‑sensitive patients.
TGA post‑market surveillance can prompt label updates and stronger counselling recommendations without removing a product from the market.
Consolidated FAQ (Australian Context)
1. Is glyburide on the PBS?
Answer: It depends on the current PBS listing and the brand; metformin and other agents are often PBS‑preferred, so check the PBS schedule and patient eligibility.
2. How do I avoid hypoglycaemia?
Answer: Start low, take with food, keep regular meals and carry fast‑acting carbohydrate; pharmacists should provide an action plan and teach‑back.
3. Can pregnant women take glyburide?
Answer: No; product information lists pregnancy and breastfeeding as contraindications and insulin is preferred during pregnancy.
4. What if a patient has renal impairment?
Answer: Glyburide is contraindicated in significant renal dysfunction; consider gliclazide with caution or alternative classes and check renal function before prescribing.
5. Are generics interchangeable?
Answer: Generics are generally interchangeable but monitor for potency differences and counsel patients when brand switches occur.
Visual Guide (Descriptive Infographic Content)
Infographic 1 is a PBS pricing flowchart showing eligibility, co‑payment tiers and expected out‑of‑pocket costs for glyburide, gliclazide and metformin.
Infographic 2 is a pharmacy distribution map comparing urban and rural availability and showing major chains and online fulfilment pathways.
Infographic 3 is a hypoglycaemia action card for patients listing symptoms, immediate actions and when to call an ambulance.
Design Notes For Australian Audience
Use PBS colour cues and include TGA and PBAC logos where appropriate for trust signals.
Include tablet strengths and common brand names such as Micronase and generic glyburide and practical tips for stock continuity in rural areas.
Visual callouts should include “Contraindicated In Pregnancy,” “Check Renal Function,” and a telehealth e‑script QR code for online ordering.
Storage & Transport
Household Storage Under Australian Climate
Store glyburide at 20–25°C and protect tablets from moisture as per product information.
In hot or humid areas keep tablets in their original packaging in a cool cupboard away from direct sunlight and bathroom humidity.
For extreme heat days consider an insulated box for short periods if ambient temperatures exceed recommended ranges.
Cold‑Chain Logistics For Pharmacies
Pharmacies should store glyburide at room temperature with routine humidity control; no cold‑chain is required.
Rural and remote services using couriers should use insulated packaging on extreme heat days and record delivery times to ensure product integrity.
Emergency And Disaster Planning
Advise patients how to manage missed doses during floods, fires or power outages and consider an extra supply where safe under PBS or emergency prescribing pathways.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Use a structured, empathetic approach when counselling about glyburide.
Verify indication, review comorbidities, check PBS status and explain how glyburide works and the risk of hypoglycaemia.
Demonstrate hypoglycaemia recognition and response and use teach‑back to confirm understanding.
Document counselling in dispensing records and arrange follow‑up for blood glucose and renal monitoring.
National Health Authority Recommendations
Diabetes Australia and TGA product information recommend metformin as first‑line therapy and using sulfonylureas with clear rationale.
Start at the lowest effective dose, avoid glyburide in pregnancy and significant renal impairment, and review treatment regularly.
Alignment With National Recommendations
Pharmacists should ensure treatment choices are individualised and that documentation supports any use of glyburide over safer alternatives when appropriate.
Rural and telehealth scenarios require clear emergency instructions and local pharmacy contact details to maintain supply continuity.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
Final Practical Notes For Pharmacists And Prescribers.
Use glyburide only with clear documentation of rationale when safer alternatives are available on the PBS.
Start at the lowest effective dose and schedule follow‑up for HbA1c and renal function checks.
Provide a written hypoglycaemia action plan and ensure patients understand missed‑dose rules: take as soon as remembered unless close to the next dose, and never double up.
When switching brands, counsel patients about possible appearance changes and to report any unexpected effects promptly.
For supply questions check current PBS listings and consider cost when recommending alternatives such as gliclazide, metformin or newer classes where clinically appropriate.