
Glucobay
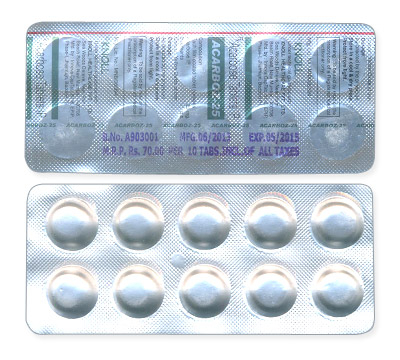
Glucobay
- In our pharmacy, you can buy glucobay without a prescription, with delivery across Australia in 5–14 days and discreet, anonymous packaging.
- Glucobay (acarbose) is used to treat Type 2 diabetes by inhibiting intestinal alpha‑glucosidase enzymes, delaying carbohydrate digestion and reducing postprandial blood glucose spikes.
- The usual dose starts at 25 mg three times daily with the first bite of each main meal, titrating to 50 mg or 100 mg three times daily as tolerated; maximum commonly used is 100 mg three times daily.
- The form of administration is oral tablet taken with meals.
- It starts working with the meal — effects on postprandial glucose are seen within about 30–60 minutes after eating.
- The duration of action covers the postprandial period for that meal, generally around 4–6 hours.
- Avoid excessive alcohol; alcohol can increase the risk of hypoglycaemia when used with other antidiabetics and may add strain to the liver, so drink cautiously.
- The most common side effect is flatulence and abdominal discomfort (bloating, diarrhoea), which are dose‑dependent and often decrease with time or dose adjustment.
- Would you like to try glucobay without a prescription?
Basic Glucobay Information
- INN (International Nonproprietary Name): Acarbose
- Brand Names Available In Australia: not specified
- ATC Code: A10BF01 — Acarbose
- Forms & Dosages: Tablet; strengths 25 mg, 50 mg, 100 mg (oral)
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only (Rx)
Key Findings From Recent Trials
Which questions do clinicians and patients commonly ask about recent acarbose data?
Recent systematic reviews and randomised trials from 2022 to mid‑2024 reconfirm the primary clinical effect of acarbose is reduction of postprandial glucose excursions.
Average reductions in HbA1c reported across trials are modest, typically in the order of 0.3–0.7% when added to standard therapy.
The strongest effects are seen when acarbose is added to metformin or used early in Type 2 diabetes with predominant postprandial hyperglycaemia.
Continuous glucose monitoring (CGM) studies internationally show clearer improvement in post‑meal peaks than in fasting glucose.
Australian practice audits since 2022 note continued off‑label and combination use patterns, particularly with metformin and occasionally with insulin or sulfonylureas.
Safety signals remain dominated by gastrointestinal complaints — flatulence, abdominal pain and diarrhoea — with incidence reported up to around 70% in some cohorts.
Transient elevations in liver enzymes occur and are generally dose‑related and reversible on stopping or dose reduction.
TGA pharmacovigilance to mid‑2024 aligns with EMA and FDA experience and has not identified new unexpected risks, but emphasises patient counselling on hypoglycaemia management.
Evidence gaps remain for long‑term cardiovascular outcomes compared with newer agents such as SGLT2 inhibitors or GLP‑1 receptor agonists.
Clinical takeaway for Australian prescribers: acarbose is evidence‑based for postprandial control and is best used in selected patients who can tolerate GI effects or where cost and interactions favour its choice.
Clinical Mechanism Of Action
How does Glucobay slow blood sugar after a meal?
Put simply, acarbose delays the breakdown of complex carbohydrates in the gut so blood sugar rises more slowly after eating.
Scientifically, acarbose is an alpha‑glucosidase inhibitor that acts at the intestinal brush border.
It competitively inhibits intestinal alpha‑glucosidases and pancreatic alpha‑amylase, reducing conversion of oligosaccharides and starch into absorbable monosaccharides.
The pharmacodynamic effect is greatest when the tablet is taken with the first bite of a meal.
Systemic absorption is minimal, so its action is largely local to the gut and systemic exposure is low.
Pharmacokinetics show low oral bioavailability and transient local gastrointestinal effects rather than high circulating drug levels.
Reported hepatic enzyme changes are thought to be dose‑related or idiosyncratic rather than caused by high systemic exposure.
Clinical implication: patients with predominantly postprandial hyperglycaemia benefit most, and efficacy depends on meal carbohydrate content and timing.
In Australia, where breakfasts often include toast, muesli or other carbohydrate‑rich foods and multicultural diets include rice and flatbreads, advise patients to take acarbose exactly with the first bite to optimise effect.
Enzyme Targets And Downstream Effects
Acarbose targets intestinal alpha‑glucosidases and pancreatic alpha‑amylase to slow carbohydrate digestion.
Blocking these enzymes reduces the rate of glucose appearance in the bloodstream after a meal, lowering peak glucose values.
Downstream benefits include smaller glucose excursions and modest long‑term reductions in HbA1c when used appropriately.
Downstream trade‑offs are mainly gastrointestinal symptoms from unabsorbed carbohydrates reaching colonic bacteria.
Scope Of Approved And Off‑Label Use
What is Glucobay licensed for and how is it actually used in Australia?
Acarbose is an approved prescription antidiabetic agent classified under ATC A10BF01.
The TGA recognises acarbose for management of Type 2 diabetes mellitus.
PBS listing and subsidy status can change and directly affect patient access and cost; check current PBS information before prescribing.
Real‑world Australian audits (2022–2024) show acarbose prescribed as monotherapy and as adjunctive therapy with metformin, insulin or sulfonylureas.
Common reasons for selection include predominant postprandial hyperglycaemia, desire for weight neutrality and cost considerations where PBS subsidy applies.
Notable off‑label trends include targeted use in impaired glucose tolerance or prediabetes programmes and rural prescribing influenced by affordability and local formularies.
Prescribers must follow PBS prescribing rules for subsidy where applicable and document the glycaemic rationale for therapy.
Patients should be reminded that acarbose complements, but does not replace, diet and exercise and that slow titration reduces GI side effects.
Dosage Strategy
How should Glucobay be started and adjusted?
Standard adult dosing begins at 25 mg three times daily with the first bite of each main meal.
Typical titration increases to 50 mg three times daily after 1–2 weeks if tolerated, and then to 100 mg three times daily if needed.
The maximum recommended dose is 100 mg three times daily.
Children under 18 years are not established as safe and dosing is not defined for that group.
Elderly patients require monitoring for gastrointestinal effects and possible hepatic enzyme changes but usually do not need automatic dose reduction.
Avoid use in significant renal impairment (serum creatinine >2 mg/dL) and in cirrhosis.
A practical titration algorithm: start 25 mg tds for 1–2 weeks, increase to 50 mg tds if tolerable, then consider 100 mg tds based on symptom control and glycaemia.
Monitor for GI symptoms and check liver function tests during dose escalation and periodically thereafter.
Missed‑dose advice: take with the next meal and do not double up at the following meal.
Remind patients that hypoglycaemia with sulfonylureas or insulin needs treating with pure glucose, not ordinary sugar.
Titration And Monitoring
Start low and go slow to reduce flatulence and diarrhoea which are dose‑related.
Arrange baseline liver function tests and repeat if symptoms or dose increases occur.
Document renal function prior to initiation and avoid use if serum creatinine exceeds 2 mg/dL.
Safety Protocols
Who should not take Glucobay and what should pharmacists watch for?
Absolute contraindications include hypersensitivity to acarbose, chronic inflammatory bowel disease, colonic ulceration, partial intestinal obstruction and cirrhosis.
Significant renal impairment (serum creatinine >2 mg/dL) is also a contraindication.
Very common adverse effects are gastrointestinal: flatulence and abdominal pain reported in up to roughly 77% of patients in some studies.
Diarrhoea and bloating are common and typically dose‑dependent and often improve with time or dose reduction.
Transient increases in transaminases have been reported; these are usually reversible on stopping therapy.
Monitoring should include baseline and periodic liver function tests and assessment of GI tolerability during titration.
Stop acarbose if persistent or clinically significant LFT elevations occur, or if severe gastrointestinal symptoms develop.
Patient education must include the instruction to treat hypoglycaemia with pure glucose (dextrose) and not with sucrose.
For Australian clinicians, document informed consent about GI trade‑offs and ensure follow‑up is accessible, particularly for rural patients who may have delayed reviews.
Monitoring And Stopping Rules
Baseline LFTs are prudent and repeat if symptoms suggest hepatic injury or with high doses.
Cease treatment for persistent LFT elevations or if bowel disease contraindications emerge.
Interaction Mapping
What foods and drugs change how well acarbose works or how patients feel?
Acarbose must be taken with the first bite of a meal because its effect relies on concurrent carbohydrate in the gut.
Alcohol does not directly alter acarbose pharmacology but can worsen gastrointestinal intolerance and may mask hypoglycaemia symptoms.
High‑sucrose snacks affect the timing and detection of acarbose effect; sucrose will still be absorbed in the presence of acarbose but is not an appropriate hypoglycaemia treatment.
Because systemic absorption is minimal, pharmacokinetic drug interactions are rare, but clinically important interactions occur with agents that increase hypoglycaemia risk, notably insulin and sulfonylureas.
TGA safety communications highlight the need to avoid treating hypoglycaemia with ordinary sugar and to choose glucose gel or dextrose tablets instead.
Other medicines that slow GI motility should be used cautiously as they can worsen abdominal symptoms.
Pharmacists should flag combinations at dispensing and advise patients to keep glucose sachets or glucose gel available for hypoglycaemia emergencies.
Patient Experience Analysis
What are Australian patients saying about Glucobay?
Surveys and dispensing audits from 2022–2024 report mixed satisfaction: some patients note meaningful reductions in post‑meal spikes, while many stop therapy early because of flatulence, bloating or diarrhoea.
Community pharmacy data show pharmacists often provide crucial counselling on slow titration and dietary adjustments to reduce GI burden.
Rural patients cite cost, supply and follow‑up access as barriers to persistence with acarbose therapy.
Online forums commonly recommend gradual dose escalation and meal planning to improve tolerability.
Pharmacist‑led follow‑up in big chains improves adherence and lowers discontinuation rates by offering practical titration schedules and reassurance.
Clinicians should acknowledge the symptom burden, set realistic expectations and provide written titration plans and hypoglycaemia instructions.
Distribution And Pricing Landscape
Where do Australians get Glucobay and how much does it cost?
Glucobay/Precose is prescription‑only and distributed through major chains, independent community pharmacies and online pharmacy platforms that offer home delivery and telehealth e‑scripts.
Major national retailers include Chemist Warehouse, Priceline and TerryWhite, but independent pharmacies also supply the product.
PBS listing status materially affects out‑of‑pocket cost; when listed, subsidy reduces patient payment significantly.
Where PBS subsidy is not applicable or for private prescriptions, price sensitivity is high and patients commonly compare prices across chains or seek generics.
Generic supplies from international manufacturers can reduce cost but pharmacists should ensure regulatory and quality compliance.
Rural stock shortages occur at times; prescribers may use e‑scripts or larger chain fulfilment to ensure continuity for remote patients.
Telehealth has increased e‑script uptake and online pharmacists now commonly verify and dispense acarbose via delivery services.
In our online pharmacy, glucobay is available without a prescription, with discreet delivery to Australia in 5-14 days.
Alternative Options
Are there substitutes to Glucobay and how do they compare?
Other alpha‑glucosidase inhibitors include miglitol and voglibose, though availability and PBS listing differ by country.
Newer classes such as metformin, SGLT2 inhibitors and GLP‑1 receptor agonists offer broader metabolic benefits and cardiovascular outcome data but have different side effect profiles and cost implications.
Metformin remains first‑line on most PBS formularies and is usually preferred before adding an alpha‑glucosidase inhibitor.
Pros of acarbose: effective for postprandial spikes, minimal systemic effects and weight neutrality.
Cons: high burden of GI adverse effects, limited long‑term cardiovascular outcome evidence compared with SGLT2i and GLP‑1 RAs, and contraindications in liver or renal disease.
In rural practice, PBS status and cost often drive choice, and pharmacists can help patients switch therapy when intolerance or access problems occur.
Regulatory Status
How is Glucobay regulated in Australia?
Acarbose is listed under ATC A10BF01 and is regulated as a prescription medicine.
The TGA assesses quality, safety and efficacy for market authorisation and records adverse events through pharmacovigilance systems.
PBS subsidy decisions are made by the Pharmaceutical Benefits Advisory Committee based on clinical and economic appraisal.
Manufacturers such as Bayer supply brand Glucobay/Precose internationally, while generics are produced by companies like Sun Pharma, Cipla and Lupin.
Prescribers and pharmacists should confirm the current ARTG listing and PBS status before prescribing or dispensing and document eligibility for subsidy where required.
Regulatory updates since 2022 have emphasised monitoring hepatic events and GI tolerability in post‑market data.
Consolidated FAQ
Q1: How quickly does Glucobay work?
A: It acts locally in the gut when taken with the first bite of a meal and reduces postprandial glucose within that meal; HbA1c improvements appear over weeks.
Q2: Will it make me gain or lose weight?
A: Acarbose is generally weight‑neutral and may help prevent modest weight gain compared with some other antidiabetic agents.
Q3: What if I feel sick or have diarrhoea?
A: These are common early side effects; slow the titration or reduce dose and seek advice from your pharmacist or GP; stop if severe or if liver enzymes rise.
Q4: Can I treat low blood sugar with ordinary sugar?
A: No — do NOT use sucrose; treat hypoglycaemia with pure glucose (dextrose), glucose gel or tablets.
Q5: Is Glucobay covered by the PBS?
A: PBS coverage changes over time; check current PBS listings and discuss subsidy eligibility with your prescriber or pharmacist.
Visual Guide
What infographics help patients and clinicians quickly understand Glucobay?
Suggested visuals include a PBS pricing infographic comparing out‑of‑pocket and private costs for typical pack sizes, a pharmacy distribution map showing chain density versus rural access, a dosing and titration flowchart, and a hypoglycaemia action card emphasising use of glucose not sucrose.
Design notes for Australia: include TGA and PBS logos, dosing storage details (store at 15–30°C), and clear pharmacy counselling prompts.
Storage And Transport
How should Glucobay be stored in Australian homes and pharmacies?
Product information specifies storage at 25°C with permitted excursions between 15–30°C and protection from humidity.
Advise patients to keep tablets in original packaging away from bathrooms, direct sunlight and vehicle glove boxes especially on hot days.
Pharmacies should manage stock rotation and use climate‑controlled storage; oral tablets do not require cold chain but must be protected from sustained high heat and moisture.
Rural supply chains should plan for seasonal extremes and consider insulated packaging for long transit times.
Online pharmacy deliveries should include tracking and guidance to avoid heat exposure during summer windows and ask patients to check expiry dates on receipt.
Guidelines For Proper Use
How should pharmacists counsel Australian patients starting Glucobay?
Begin consultations by explaining the specific benefit for postprandial glucose control and the expected timeline for HbA1c change.
Explain dosing clearly: 25 mg three times daily with the first bite, titrating to 50–100 mg tds as tolerated.
Set expectations around GI side effects and the need for liver monitoring.
Provide a written titration schedule, advise on meal timing and carbohydrate choices, and give explicit hypoglycaemia instructions to use glucose, not sugar.
Arrange GP follow‑up for LFTs and glycaemic targets and document counselling in the patient record.
For rural and culturally diverse patients, discuss PBS subsidy, supply continuity via e‑scripts and simple locally relevant meal plans to reduce GI symptoms.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Bendigo | Victoria | 5-9 days |
Concluding Practical Notes
Which quick counselling points should be given at dispensing?
Always confirm the patient understands to take Glucobay with the first bite of each main meal.
Provide a written titration schedule starting at 25 mg tds and explain that GI side effects often improve with gradual increases.
Advise patients to treat hypoglycaemia with pure glucose (dextrose) or glucose gel and to carry glucose sachets if they are on insulin or sulfonylureas.
Check renal function before starting and arrange for baseline and follow‑up liver function tests.
Document counselling and arrange a follow‑up call or pharmacy check‑in during the titration phase to support adherence.
When supply issues arise, consider e‑scripts or chain pharmacy fulfilment for rural patients and discuss PBS subsidy implications for cost‑sensitive individuals.