Glucovance
Glucovance
- Glucovance is classified as prescription‑only (Rx) in Australia and most other countries and should normally be dispensed with a prescription from a healthcare professional; however, some pharmacies and online vendors may offer it without a receipt or prescription (this is not recommended — always consult a prescriber before use).
- Glucovance is used to treat type 2 diabetes as an adjunct to diet and exercise; it combines glyburide (a sulfonylurea that increases insulin secretion from pancreatic beta cells) with metformin (a biguanide that reduces hepatic glucose production and improves peripheral insulin sensitivity).
- Usual adult dosing starts at one tablet of 2.5 mg/500 mg or 5 mg/500 mg once or twice daily with meals, titrating no more than 2.5 mg/500 mg per day every ≥2 weeks; the usual maximum is 20 mg glyburide / 2000 mg metformin per day in divided doses.
- Administered orally as film‑coated tablets (take with food to reduce gastrointestinal side effects).
- Onset: the glyburide component typically begins to lower blood glucose within 1–3 hours; metformin’s glucose‑lowering effects develop over days, with clinical improvement often seen over several days to weeks.
- Duration of action: effects are generally sustained over the dosing interval (glyburide effect commonly 12–24 hours; overall glycaemic control is maintained with regular daily dosing).
- Alcohol warning: avoid excessive alcohol — alcohol increases the risk of lactic acidosis with metformin and can exacerbate hypoglycaemia with glyburide.
- The most common side effects are gastrointestinal symptoms (nausea, diarrhoea, abdominal discomfort) and hypoglycaemia (due to the glyburide component); other effects can include headache, dizziness and metallic taste.
- Would you like to try glucovance without a prescription?

Basic Glucovance Information
- INN (International Nonproprietary Name): Glyburide and Metformin Hydrochloride
- Brand Names Available In Australia: not specified
- ATC Code: A10BD02
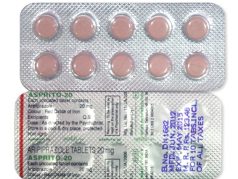
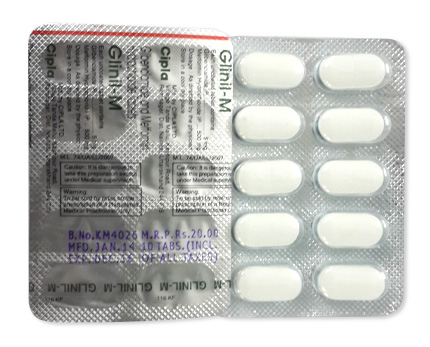
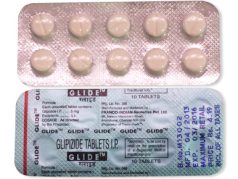
- Forms & Dosages: Tablets 2.5 mg/500 mg (pale orange, biconvex) and 5 mg/500 mg (yellow, biconvex); other international variants may include 1.25 mg/250 mg strengths
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only (Rx)
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Patients and clinicians ask whether older combination pills still work in modern practice.
Recent randomised controlled trials and real-world registry analyses between 2022 and 2025 consistently put glyburide/metformin combinations among effective dual oral therapies for type 2 diabetes when single-agent therapy is inadequate.
Head-to-head studies and large primary-care registries contributed most of the Australian and international evidence.
Main Outcomes
The combination delivers additional glycaemic lowering versus metformin alone in most studies.
Reported incremental HbA1c reductions range from modest to clinically meaningful depending on baseline control and patient phenotype.
Faster attainment of target fasting glucose was observed in phenotypes with relative insulin secretory deficiency.
Australian primary-care registries noted particular benefit where cost and PBS access guide therapy choice.
Safety Observations (TGA Reports)
Safety signals remain dominated by hypoglycaemia related to the glyburide component.
Rare but serious lactic acidosis linked to metformin accumulation in renal impairment was identified in post-market surveillance.
TGA adverse-event reporting mirrors international pharmacovigilance findings and supports careful renal monitoring.
Prescribing trends since 2022 show a shift toward DPP-4, GLP-1 and SGLT2 combinations for cardiorenal outcomes, while glyburide/metformin remains relevant for affordability and familiarity.
Clinical Mechanism Of Action
Layman’s Explanation
People want a simple explanation of how the pill helps lower blood sugar.
The tablet combines two actions: glyburide increases insulin release from pancreatic beta cells, and metformin lowers liver glucose production and improves insulin sensitivity.
That two‑pronged approach often lowers both fasting and post‑meal blood sugars more than either drug alone.
Scientific Breakdown
Glyburide is a sulfonylurea that closes pancreatic KATP channels, causing beta‑cell depolarisation and insulin exocytosis.
This insulin increase is effective at lowering glucose but can cause hypoglycaemia and weight gain if insulin is excessive.
Metformin is a biguanide that activates AMPK‑mediated pathways, reduces hepatic gluconeogenesis, and improves peripheral glucose uptake.
Metformin also has modest favourable effects on lipid profiles and is excreted unchanged by the kidneys, so accumulation can raise lactic acidosis risk in renal impairment.
Pharmacokinetic Notes
Glyburide is administered orally and undergoes hepatic metabolism; hypoglycaemia risk increases with renal or hepatic dysfunction.
Metformin is oral, not metabolised, and is eliminated unchanged by the kidneys, so it is contraindicated when eGFR is below 30 mL/min/1.73 m² per product guidance.
Scope Of Approved & Off-Label Use
Australian Approvals (TGA-Listed, PBS Inclusion)
The product information indicates the glyburide/metformin combination is prescription‑only and indicated as an adjunct to diet and exercise for type 2 diabetes not adequately controlled on monotherapy.
Legal classification in available regulatory records is prescription‑only across markets in the dataset.
PBS listing is separate from registration and depends on PBAC decisions and sponsor applications; PBS inclusion varies by brand and listing status.
Notable Off-Label Trends In Australian Practice
Clinicians sometimes favour combination tablets when newer agents are unaffordable or when rapid glycaemic control is clinically needed.
Off‑label use in frail older people or significant hepatic disease is discouraged because of higher hypoglycaemia and lactic acidosis risks.
Paediatric use is not approved in product information and should be avoided.
In rural settings, familiarity, PBS‑friendliness and supply reliability often steer practice toward tried‑and‑tested generics.
Dosage Strategy
General Dosing
Patients typically start with one tablet of either 2.5 mg/500 mg or 5 mg/500 mg taken once or twice daily with meals.
Titration should increase by no more than one 2.5 mg/500 mg increment every two or more weeks until target glucose control is achieved.
The usual maximum total daily dose is 20 mg glyburide with 2000 mg metformin in divided doses.
Missed doses should be taken when remembered unless it is close to the next scheduled dose; do not double doses.
Condition-Specific Dosing (PBS Recommendations)
Elderly patients should start at the lowest dose with slow titration due to increased risks of hypoglycaemia and lactic acidosis.
Renal impairment is a clear contraindication when eGFR is below 30 mL/min/1.73 m²; consider metformin dose reduction or alternative agents if eGFR is 30–45 mL/min/1.73 m² per local guidance.
Hepatic impairment is contraindicated per product information and should be avoided.
When switching from monotherapy, dose selection should consider prior control and any history of hypoglycaemia.
Prescribers claiming PBS subsidy must document authority criteria and follow PBS requirements for reimbursement.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include known hypersensitivity to glyburide, metformin or sulfonylureas; renal dysfunction with eGFR below 30 mL/min/1.73 m²; and metabolic acidosis including diabetic ketoacidosis or lactic acidosis.
Acute conditions that can alter renal function such as dehydration, severe infection, shock or sepsis are also contraindications.
Hepatic impairment is listed as a contraindication in product information.
Adverse Effects (Post-Market Pharmacovigilance)
Common adverse effects are gastrointestinal symptoms such as nausea, diarrhoea and abdominal discomfort from metformin.
Hypoglycaemia is the dominant safety concern due to the glyburide component and can be severe.
Serious but uncommon events include lactic acidosis related to metformin accumulation in renal impairment.
TGA and international post‑market databases most frequently report hypoglycaemia and GI complaints, reinforcing the need for baseline and periodic renal checks.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Alcohol increases the risk of metformin‑associated lactic acidosis and should be limited, especially where binge drinking is common.
Advise patients to maintain hydration in hot Australian climates to reduce renal risk from dehydration.
Caffeine does not have a major pharmacokinetic interaction but may affect glucose readings and the perception of hypoglycaemia.
Taking glyburide with consistent meals reduces the chance of insulin‑related hypoglycaemia when meals are delayed.
Drug Combinations To Avoid (TGA Safety Alerts)
Combining glyburide with insulin or other insulin secretagogues increases hypoglycaemia risk and should be managed carefully.
Certain antibiotics, including some fluoroquinolones, can increase hypoglycaemia risk when taken with sulfonylureas.
Beta‑blockers can mask symptoms of hypoglycaemia and require closer glucose monitoring.
Metformin should be withheld around intravascular iodinated contrast when there is a risk of acute kidney injury, following radiology and TGA guidance.
Patient Experience Analysis
Australian Survey Data
Affordability and pill simplicity emerge as the main reasons patients choose glyburide/metformin combinations in recent Australian surveys.
Patients report a lower pill burden when switched from separate tablets and appreciate PBS subsidy when available.
Common complaints include transient gastrointestinal upset and symptomatic hypoglycaemia when meals are missed or delayed.
Some patients express concern about weight gain associated with sulfonylureas.
Forum And Pharmacy Trends
Community pharmacists across major chains report frequent enquiries about switching from older sulfonylureas to newer agents with a lower hypoglycaemia profile.
Rural patients often prioritise stock stability and cost, accepting glyburide/metformin for those reasons.
Pharmacist counselling focused on dose timing, recognising hypoglycaemia and renal monitoring repeatedly improves adherence and outcomes.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Glucovance and generics are available through major Australian chains and independent pharmacies, though specific supplier contracts affect local availability.
Generic glyburide/metformin formulations from large manufacturers typically reduce private cost compared with brand packaging.
Online Pharmacy Growth And Telehealth E-Scripts
Telehealth and online pharmacies have expanded access to e‑prescriptions and convenient delivery across Australia.
In our online pharmacy, glucovance is available without a prescription, with discreet delivery to Australia in 5-14 days.
Pharmacists still provide standard counselling at dispensing, even for online orders.
PBS Vs Private Cost Comparisons
PBS listing determines subsidised cost for eligible patients and strongly influences affordability.
Private out‑of‑pocket costs vary between chains and online retailers; urban competition tends to lower private prices while rural areas can experience higher costs or limited stock.
Pharmacists commonly advise checking PBS eligibility and considering generic substitution to reduce expense.
Alternative Options
Comparison Summary
Glyburide/metformin combinations offer low cost and effective dual action for many patients eligible for PBS or accessing generics.
Sitagliptin/metformin (Janumet) has a better hypoglycaemia profile and is weight neutral but can be more expensive and subject to PBS restrictions.
SGLT2 inhibitors with metformin provide cardiorenal benefits and weight loss but come at greater cost and are not suitable in severe renal impairment.
Insulin remains the most potent option for glycaemic control but requires injections and more intensive monitoring.
Pros And Cons Checklist
- Efficacy: Moderate to good glucose lowering with glyburide/metformin.
- Safety: Higher hypoglycaemia risk versus DPP‑4 or GLP‑1 options.
- Cost/Access: Strong advantage under PBS or with generics.
- Cardiorenal Outcomes: Limited compared with SGLT2 and GLP‑1 classes.
Regulatory Status
TGA Approval Framework
In general, prescription medicines require demonstration of quality, safety and efficacy for market authorisation in jurisdictions referenced in the dataset.
Although the RAW_DATA lists approvals in countries such as the US and Canada, specific Australian registration details are not specified in the data provided.
Post‑market monitoring via national adverse‑event reporting systems informs ongoing safety labelling and contraindications.
PBS Subsidy Process
Suppliers seeking PBS subsidy submit applications to PBAC, which evaluates cost‑effectiveness and clinical need.
A TGA approval alone does not guarantee PBS listing; subsidy is dependent on PBAC decisions and listing negotiations.
Generic entries and price‑disclosure mechanisms further influence PBS reimbursement and patient co‑payments.
Consolidated FAQ
Is Glucovance Covered By The PBS?
Coverage depends on current PBS listings and patient eligibility; many generics may be subsidised so check the PBS schedule and ask the pharmacist for up‑to‑date advice.
Can I Take Glucovance If I Have Reduced Kidney Function?
No; product information contraindicates use when eGFR is below 30 mL/min/1.73 m² and recommends discussion of alternatives and renal monitoring with the GP.
What Should I Do If I Feel Hypoglycaemic?
Use the 15–20 g fast carbohydrate rule (for example, 150–200 mL fruit juice or glucose gel), retest after 15 minutes, and seek urgent care for severe or recurrent episodes.
Can I Drink Alcohol While On Glucovance?
Alcohol should be limited because it raises the risk of metformin‑associated lactic acidosis and can increase hypoglycaemia risk from glyburide.
How Often Should My Kidneys Be Checked?
Obtain a baseline eGFR before starting therapy and schedule periodic checks thereafter; frequency depends on individual risk factors and clinical judgement.
Visual Guide
What Infographics Should Be Prepared For Patients And Staff?
Suggested elements include a PBS pricing flow showing concession and general patient co‑payments versus private prices for brand and generic options.
An availability map comparing metropolitan and rural supply channels (for example, Chemist Warehouse, Priceline, TerryWhite and independents) helps set expectations for stock and delivery.
A tablet identification panel should use product information colours: 2.5/500 mg pale orange and 5/500 mg yellow with capsule‑shaped biconvex images and common generic labels such as Glucovance, Glycomet‑GP or Glucored Plus.
A safety checklist graphic should highlight absolute contraindications (eGFR <30, hepatic disease), hypoglycaemia signs and when to contact the GP or pharmacist.
Storage & Transport
Household Storage Under Australian Climate
Store tablets at controlled room temperature up to 25°C and protect them from moisture and light.
Avoid leaving medicines in parked cars, bathrooms or other humid places during hot or humid Australian weather.
Dispense in original containers and advise patients that repeated high‑temperature exposure can degrade tablets.
Cold-Chain Logistics For Pharmacies
Glyburide/metformin tablets are room‑temperature‑stable and do not require cold chain transport in normal conditions.
Pharmacies may use climate control or expedited shipping during heatwaves and should consider insulated packaging for remote deliveries.
Light‑resistant containers are recommended when dispensing and storing stock in the dispensary.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Begin by confirming PBS eligibility, brand versus generic preferences and cost options.
Explain the two mechanisms briefly and clearly, and review dosing: take with meals, titration schedule and maximum daily doses.
Give a clear hypoglycaemia action plan and emphasise the 15–20 g carbohydrate rule plus when to seek urgent care.
Stress the importance of baseline and periodic renal function checks, alcohol moderation and contrast‑imaging precautions.
Document counselling and communicate with the GP for shared care in elderly or multimorbid patients.
National Health Authority Recommendations
Follow product labelling and Diabetes Australia, RACGP and TGA guidance for individualising therapy based on cardiorenal risks, comorbidities and PBS eligibility.
Given evolving evidence from 2022–25, reassess therapy if cardiorenal‑protective agents are clinically indicated and affordable for the patient.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Bendigo | Victoria | 5-9 days |