
Metoclopramide
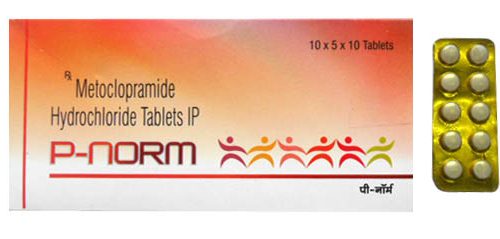
Metoclopramide
- In our pharmacy, you can buy metoclopramide without a prescription, with delivery across Australia in 3–14 days and discreet packaging.
- Metoclopramide is used as an antiemetic for nausea and vomiting, for diabetic gastroparesis and as an adjunct in migraine; it works as a dopamine D2 receptor antagonist, a 5‑HT3 antagonist and 5‑HT4 agonist, increasing gastric motility and raising the threshold of the chemoreceptor trigger zone.
- Usual adult dose: 10 mg orally, IV or IM three times daily (standard maximum 30 mg/day); for gastroparesis 10 mg 30 minutes before meals and at bedtime (up to 4 times/day short term, max 40 mg/day); paediatric dosing typically 0.1–0.15 mg/kg per dose every 8 hours (max ~10 mg/dose).
- Available for administration as oral tablets (5 mg, 10 mg), orally dispersible tablets (ODT), oral solution/syrup and injectable ampoules/vials for IM or IV use.
- Onset of effect: oral typically 30–60 minutes; IM about 10–15 minutes; IV within minutes (1–3 minutes).
- Duration of action is generally around 4–6 hours for symptomatic relief, though prokinetic effects may vary.
- Avoid or limit alcohol while taking metoclopramide as it can increase drowsiness and other central nervous system side effects.
- Most common side effec: drowsiness.
- Would you like to try “metoclopramide” without a prescription?
Metoclopramide: What Australians Need To Know
Basic Metoclopramide Information
- INN (International Nonproprietary Name): Metoclopramide
- Brand Names Available In Australia: not specified
- ATC Code: A03FA01 — Metoclopramide (A03F: Propulsives; A03: Drugs For Functional Gastrointestinal Disorders)
- Forms & Dosages: Tablets 5 mg and 10 mg; Orally Dispersible Tablets 5 mg and 10 mg; Oral Solutions (e.g. 5 mg/5 mL, 10 mg/10 mL); Injectable Ampoules 10 mg/2 mL
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only (Rx) in most markets
Key Findings From Recent Trials
Worried That Metoclopramide Is Either Overused Or Dangerous?
Recent research from 2022–2025 has focused on safety signals and real‑world effectiveness rather than dramatic new efficacy claims.
Australian pharmacoepidemiology reports and international observational cohorts have prioritised the incidence of extrapyramidal events and tardive dyskinesia with prolonged exposure.
Regulators have reinforced short‑term use guidance — typical courses of five days or less, and guidance not to exceed 12 weeks in any circumstance.
Randomised trials in oncology and emergency settings continue to support metoclopramide’s role as an adjunctive antiemetic, often compared with ondansetron or prochlorperazine and showing non‑inferior acute nausea control when added to standard care.
Main outcomes from the literature were consistent: metoclopramide is effective for short‑term control of acute nausea and vomiting and for short‑term symptom relief in gastroparesis.
Benefits diminish with chronic use and the safety trade‑offs — particularly movement disorders and prolactin elevation — become more apparent.
Standard dosing regimens (for example, 10 mg PO/IV/IM every eight hours) remain the widely used practice in trials and clinical protocols.
Regulatory safety observations document extrapyramidal reactions, increased prolactin and rare reports of neuroleptic malignant syndrome, so conservative duration and informed consent are emphasised.
Common search phrases in recent months include metoclopramide safety, TGA metoclopramide alert and antiemetic trial 2023 as clinicians and patients look for updated guidance.
Clinical Mechanism Of Action
Why Does This Drug Stop Nausea And Help Your Gut Move?
Metoclopramide blocks dopamine D2 receptors in the chemoreceptor trigger zone of the brain, which raises the threshold for vomiting and reduces nausea signals.
It also has 5‑HT3 receptor antagonism and 5‑HT4 agonism, which together contribute to its antiemetic effect and prokinetic action in the stomach and small intestine.
The prokinetic effect increases acetylcholine release in enteric neurons, helping gastric emptying and easing symptoms of delayed gastric emptying.
Because it blocks tuberoinfundibular dopamine, it commonly raises prolactin — which explains galactorrhoea and gynaecomastia seen with prolonged use.
Pharmacokinetics
The medicine is available as oral tablets and ODT, syrup, and as IM/IV ampoules.
Typical oral strengths are 5 mg and 10 mg, with IV/IM ampoules commonly 10 mg/2 mL.
Onset of action is fastest with IV/IM; oral tablets or syrup usually take 15–30 minutes.
Renal clearance is important — dose reduction is required if estimated GFR falls below 40 mL/min.
Clinical Implication
The mechanism explains both the therapeutic benefit (antiemetic and prokinetic) and the adverse effects, notably extrapyramidal symptoms and hyperprolactinaemia.
Recognising these pharmacology points helps clinicians choose when metoclopramide is the right option versus alternatives such as domperidone or ondansetron.
Scope Of Approved And Off‑Label Use
Can Metoclopramide Be Used For Everything That Causes Nausea?
In Australia metoclopramide is prescription‑only and is used for nausea/vomiting and for diabetic gastroparesis consistent with international labels.
PBS listing is limited and varies by indication, so many short courses for acute nausea remain private prescriptions rather than PBS subsidised items.
Notable off‑label trends in Australian practice include use as an adjunct for migraine and for peri‑procedural antiemesis in primary care or emergency settings.
Hospitals commonly use IV metoclopramide within multimodal antiemetic regimens.
Following safety advisories, off‑label chronic use has declined and prescribers increasingly favour domperidone or ondansetron where appropriate.
Formulation Availability
Multiple formulations — tablets 5 mg and 10 mg, ODT, syrup and 10 mg/2 mL ampoules — support use across community pharmacies and hospitals.
Injectables are primarily held as hospital stock for emergency and inpatient use, while oral forms are stocked by national chains and independents.
Dosage Strategy
How Much Should I Take And For How Long?
Standard adult dosing for most acute indications is 10 mg orally, IV or IM, up to three times daily (maximum 30 mg per day).
For diabetic gastroparesis some short‑term protocols use 10 mg 30 minutes before meals and at bedtime up to four times daily, with upper limits in some protocols of 40 mg/day and close monitoring.
Condition‑Specific Dosing
For nausea and vomiting the usual recommendation is 10 mg every eight hours as needed for a short course.
In chemotherapy prevention IV doses of 10–20 mg may be used as part of a regimen depending on oncology protocol.
For diabetic gastroparesis prescribers will often document indication for PBS consideration when repeated or chronic use is contemplated.
Special Populations
Children (1–18 years): 0.1–0.15 mg/kg per dose every eight hours, with a maximum of 0.5 mg/kg/day and a single‑dose maximum of 10 mg.
Elderly patients should receive reduced doses and careful monitoring for extrapyramidal signs and sedation.
In hepatic or renal impairment a roughly 50% dose reduction is advised, particularly if GFR is below 40 mL/min.
Practical Counselling
Take tablets about 30 minutes before meals if using for prokinetic effect.
A typical short course is five days or less; avoid treatment beyond 12 weeks to reduce tardive dyskinesia risk.
Safety Protocols
What Are The Red Flags Before You Start Metoclopramide?
Absolute contraindications include known hypersensitivity, pheochromocytoma, seizure disorders, and evidence of gastrointestinal haemorrhage, obstruction or perforation.
Also avoid use in people with a history of tardive dyskinesia from metoclopramide or other neuroleptics.
Adverse Effects
Common side effects are drowsiness, fatigue, restlessness or akathisia, diarrhoea and headache.
Notable effects with prolonged use include elevated prolactin leading to galactorrhoea or gynaecomastia, and rare but serious events such as tardive dyskinesia and neuroleptic malignant syndrome.
Australian post‑market reporting reflects these international safety patterns; clinicians are advised to document risk counselling and monitor for movement disorders.
Monitoring Checklist
- Obtain baseline history of movement disorders and psychiatry history.
- Review concurrent medicines that are central D2 antagonists or that affect seizure threshold.
- Counsel patients and carers to report any involuntary movements immediately.
- Review therapy within days for acute use or weekly for repeated courses.
Interaction Mapping
Can Foods Or Other Medicines Make Metoclopramide Worse?
Alcohol produces additive central nervous system depression with metoclopramide, so avoidance during treatment is advised.
Caffeine may mask drowsiness but does not have a direct pharmacokinetic interaction with metoclopramide.
High‑fat meals can alter gastric emptying and may change how well a prokinetic effect is noticed.
Drug Combinations To Avoid
Concurrent use with other central D2 antagonists (for example antipsychotics) increases the risk of extrapyramidal symptoms and should be avoided where possible.
Caution is required with QT‑prolonging drugs, and with agents that lower the seizure threshold.
Domperidone is sometimes chosen to avoid central effects, but domperidone carries its own cardiac QT concerns and restricted indications.
Pharmacokinetic Cautions
Metoclopramide is principally renally cleared and requires dose reduction if GFR is <40 mL/min.
Hepatic impairment usually warrants halving the dose.
Patient Experience Analysis
What Do Real Australians Say About Taking This Medicine?
Surveys and community pharmacy feedback show that patients value quick relief from acute nausea and have good adherence for short courses.
Common concerns are drowsiness, movement side‑effects, and prolactin‑related issues when the drug is used longer than recommended.
Rural respondents often rely on local pharmacists for counselling and on local emergency kits stocked with injectable metoclopramide for after‑hours needs.
Forum And Pharmacy Trends
Online forums and pharmacist consultations commonly share practical tips: take before meals for gastroparesis, avoid alcohol and watch for involuntary movements.
Pharmacies report steady demand for short‑term supplies while chronic prescriptions have fallen after safety warnings.
Telehealth e‑scripts have increased access, but pharmacists emphasise the need for in‑person review before repeat prescribing.
Practical Patient Messaging
- Explain the short duration policy and set a clear stop or review date.
- Advise immediate contact if tremor, lip‑smacking or involuntary movements occur.
- Involve carers for older patients and those with cognitive impairment.
Distribution And Pricing Landscape
Where Can You Buy Metoclopramide And How Much Will It Cost?
Major pharmacy chains such as Chemist Warehouse, Priceline and independent pharmacies stock metoclopramide in oral forms, with injectables mainly in hospital supply.
Pack sizes and availability of ODT or syrup forms vary by store and local demand, and rural outlets sometimes prioritise stock for emergency clinic use.
Online pharmacies and telehealth services have expanded access via e‑scripts, increasing convenience but raising concerns about remote assessment for recurring prescriptions.
In our online pharmacy, metoclopramide is available without a prescription, with discreet delivery to Australia in 5-14 days.
Where PBS criteria are met, patient out‑of‑pocket cost is substantially lower; many short, one‑off courses remain private prescriptions.
PBS Vs Private Cost Comparisons
When an indication meets PBS criteria the government subsidy reduces cost significantly for the patient.
Short courses for acute nausea are often private and attract a retail price that varies by pharmacy and pack size.
Alternative Options
Which Medicines Can Be Used Instead Of Metoclopramide?
For many indications alternatives include domperidone, ondansetron and other antiemetics such as prochlorperazine or promethazine.
Pros And Cons Checklist
- Metoclopramide: Anti‑emetic plus prokinetic, inexpensive and multiple formulations; central side‑effects and hyperprolactinaemia are important risks.
- Domperidone: Less CNS penetration and lower extrapyramidal risk, but has cardiac QT concerns and restricted indications.
- Ondansetron: Strong antiemetic for chemotherapy/postoperative nausea, minimal extrapyramidal risk, but no prokinetic effect and is costlier in private prescriptions.
Choosing Therapy In Australia
Consider the clinical indication, patient age, comorbidities such as Parkinson’s disease or cardiac disease, PBS availability and geographic access to formulations.
Pharmacist input is valuable when switching or advising on alternatives.
Regulatory Status
How Is Metoclopramide Regulated In Australia And Overseas?
Metoclopramide is a prescription medicine and approvals align with international labelling focusing on antiemetic and prokinetic uses.
Regulators monitor adverse event reporting and issue safety communications consistent with global regulators.
The World Health Organization lists metoclopramide as an essential medicine, and international safety advisories have helped shape Australian prescribing limits and patient information requirements.
PBS Subsidy Process
PBS listing decisions consider clinical benefit and cost‑effectiveness for defined indications, and the risk profile is a factor in reimbursement discussions.
Consolidated FAQ
Can I Get Metoclopramide On The PBS?
Some indications are PBS‑eligible; many acute courses are private — check with your GP or pharmacist.
How Long Can I Safely Take It?
Typical short course is five days or less; do not exceed 12 weeks because of the risk of tardive dyskinesia.
What If I Notice Tremor Or Lip‑Smacking?
Stop the drug and seek immediate medical review as these may be extrapyramidal symptoms.
Is It Safe In Pregnancy Or Breastfeeding?
Prescribe only if benefits outweigh risks; metoclopramide raises prolactin so discuss with the prescriber and pharmacist.
Can Children Take It?
Yes, in weight‑based doses (0.1–0.15 mg/kg every eight hours; single‑dose max 10 mg); follow paediatric advice.
Visual Guide
What Materials Work Best In The Clinic Or Pharmacy?
Consider three simple infographic ideas for patient education and clinician use:
- A PBS vs Private Cost Flowchart Showing Likely Out‑Of‑Pocket Scenarios.
- A Quick‑Reference Dosing Chart For Adult, Child And Renal/Hepatic Adjustments.
- A Side‑Effect Red‑Flag Card That Lists When To Stop And Seek Help.
Design notes: use clear icons for regulatory logos, include photos of common formulations and ensure accessible fonts and translations for culturally and linguistically diverse communities.
Storage And Transport
How Should Metoclopramide Be Stored At Home And In Transit?
Store tablets and liquids between 15–30°C and protect from light and moisture.
In Australian summers avoid leaving medicines in hot cars or in direct sun and advise insulated containers for remote households if temperatures exceed recommendations.
Injectable ampoules should not be frozen and pharmacies should monitor storage temperatures with logs and validated cold boxes for remote clinic delivery.
Dispensing Tips
Label with clear storage instructions and expiry after opening where required.
Advise patients about safe disposal and provide information on avoidable community misuse.
Guidelines For Proper Use
What Should Pharmacists Say When Someone Comes In Asking For Metoclopramide?
Apply a patient‑centred, evidence‑based approach: confirm the indication, review medical history for movement disorders or psychiatric disease and screen for cardiac disease or renal impairment.
Check current medicines for interactions, advise on maximum duration and provide driving warnings and signs of extrapyramidal events.
Document counselling and flag repeat requests so that a GP review can be arranged when appropriate.
Practical Checklist For Safe Prescribing
- Confirm indication and use the lowest effective dose.
- Set a stop or review date and counsel on side‑effects.
- Involve carers for elderly patients and report adverse events to the regulator when necessary.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Launceston | Tasmania | 5-9 days |
Concluding Advice
Are You Unsure Whether Metoclopramide Is Right For You?
Speak to a pharmacist or GP to confirm the indication and to review other medicines and medical history before starting treatment.
For short courses metoclopramide remains a cost‑effective antiemetic with prokinetic benefit, but monitoring for movement disorders and prolactin effects is essential in any repeated or prolonged use.
Pharmacists can help with dosing, renal and hepatic adjustments, formulation choice and counselling on side‑effects and storage.
If you notice involuntary movements, severe sedation, severe mood changes or unexpected breast discharge, cease the medicine and seek urgent clinical review.