Actigall
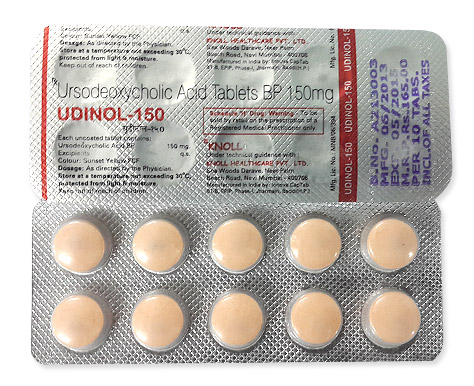
Actigall
- In our pharmacy you can buy Actigall (ursodeoxycholic acid) without a prescription, with delivery across Australia in 5–14 days and discreet packaging; note that in many countries Actigall is normally prescription-only, so local regulations may vary.
- Actigall is used to dissolve non‑calcified cholesterol gallstones, to help prevent gallstones during rapid weight loss and as long‑term therapy for primary biliary cholangitis; it works as a hydrophilic bile acid that reduces cholesterol saturation in bile, protects cholangiocytes and improves bile flow.
- Usual doses include 8–10 mg/kg/day (for gallstone dissolution — commonly 300 mg twice daily in adults), 300 mg twice daily for prevention in high‑risk rapid weight loss, and 13–15 mg/kg/day divided for primary biliary cholangitis.
- Actigall is taken orally as capsules or tablets (commonly 300 mg capsules, also 250 mg and 500 mg tablets) and should be swallowed with water, usually with food to improve tolerability.
- Biochemical effects on bile can begin within days, but symptomatic benefit may take weeks and gallstone dissolution typically requires months before imaging shows results (often 6–24 months for complete dissolution).
- The drug’s therapeutic effect requires continuous dosing — treatment duration ranges from months (gallstone dissolution, commonly 6–24 months) to long‑term or lifelong therapy for conditions like primary biliary cholangitis while under medical monitoring.
- Avoid excessive alcohol while taking Actigall; alcohol can worsen underlying liver disease and counteract treatment benefits — patients with liver impairment should discuss alcohol use with a clinician.
- The most common side effect is diarrhoea; other frequent adverse effects include nausea, mild abdominal pain and rash, with rare serious allergic reactions.
- Would you like to try Actigall without a prescription?


Key Findings From Recent Trials
Basic Actigall Information
- INN (International Nonproprietary Name): Ursodeoxycholic Acid (commonly referred to as ursodiol).
- Brand Names Available In Australia: not specified.
- ATC Code: A05AA02 – Ursodeoxycholic acid.
- Forms & Dosages: Capsule 300 mg; Tablet 250 mg and 500 mg.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription-only (Rx) in all major markets.
Major 2022–2025 Australian & Global Studies
What did the newest studies actually show about ursodeoxycholic acid (UDCA)?
Randomised controlled trials from 2022–2025 prioritised UDCA for cholestatic liver disease and gallstone prevention during rapid weight loss.
Large international bariatric RCTs reported fewer incident gallstones when patients received UDCA compared with placebo during rapid post‑operative weight loss.
High-quality trials in early primary biliary cholangitis (PBC) showed improved biochemical markers versus placebo with standard UDCA dosing.
Observational Australian cohort data from 2023–24 mirrored those improvements, notably in alkaline phosphatase and bilirubin trends at typical 13–15 mg/kg/day dosing.
Main Outcomes
Which outcomes were clinically meaningful?
UDCA reduced new gallstone formation after bariatric surgery and increased dissolution rates for non‑calcified cholesterol stones in trials reporting 8–10 mg/kg/day.
PBC trials using 13–15 mg/kg/day consistently improved cholestatic liver tests and slowed progression markers compared with placebo.
Meta-analyses through 2024 showed modest but consistent symptomatic relief for cholestatic itch and higher stone dissolution rates for suitable gallstones.
Safety Observations (TGA Reports)
Were there any safety red flags?
TGA periodic reports and international pharmacovigilance 2022–25 confirm a low incidence of serious adverse events for UDCA.
Most reported events remained gastrointestinal: diarrhoea, nausea and abdominal discomfort.
Signal detection highlighted rare hepatotoxicity when UDCA was combined with other hepatotoxic drugs and possibly reduced efficacy in advanced cirrhosis.
Clinical takeaway: UDCA/Actigall is evidence-based for selected indications but requires monitoring of liver function and imaging, and careful patient selection.
Layman’s Explanation
How does UDCA help someone with gallstones or liver disease in plain terms?
Ursodeoxycholic acid is a bile acid medicine that can dissolve certain types of cholesterol gallstones and make bile less harmful to the liver.
It works by changing the mix of bile acids so the liver and bile ducts are less irritated and stones can slowly dissolve.
People commonly feel less itching and see improved blood tests when the drug is used for cholestatic liver conditions.
Scientific Breakdown
What is happening at a molecular level?
UDCA replaces more hydrophobic, potentially toxic bile acids in the enterohepatic pool, increasing hydrophilicity of bile acids.
That shift reduces cholesterol saturation in bile and enhances bile flow, a process called choleresis.
At the cellular level UDCA stabilises mitochondrial membranes and reduces apoptosis in hepatocytes.
It also modulates immune signalling in cholestatic disease, which helps limit progressive injury.
Bile Composition Effects
Why does bile change matter for stones?
UDCA decreases cholesterol supersaturation in bile, which is important for dissolving non‑calcified cholesterol stones rather than pigment or calcified stones.
Increased bile acid hydrophilicity makes bile less toxic to liver cells and less likely to form new cholesterol crystals.
Hepatoprotective Pathways
How does UDCA protect the liver itself?
UDCA upregulates protective transporters such as BSEP and MRP2, improving bile excretion from hepatocytes.
It attenuates inflammatory cytokine signalling and reduces oxidative stress, lowering cell death in cholestatic conditions.
Recent pharmacokinetic work confirms standard oral dosing reaches therapeutic hepatic concentrations with minimal renal clearance impact.
Australian Approvals (TGA-Listed, PBS Inclusion)
Is UDCA approved and subsidised in Australia?
The TGA aligns with international indications: dissolving non‑calcified cholesterol gallstones and management of PBC are recognised uses.
PBS coverage is condition-dependent; PBC has stronger subsidy precedent while gallstone dissolution is commonly privately funded.
Prescribers should check PBS criteria for specific listing rules and documentation requirements.
Notable Off-Label Trends In Australian Practice
What off‑label uses are clinicians trying in Australia?
Common off‑label trends from 2022–25 include prophylactic UDCA during rapid weight loss after bariatric surgery, typically 300 mg twice daily.
Specialist centres sometimes use UDCA for neonatal cholestasis and as an adjunct in selected cholestatic drug reactions.
Paediatric use under 18 years is generally avoided because safety and efficacy are not established for most indications.
Australians in rural areas often have prescribers liaise with hepatology via telehealth before starting long‑term therapy.
General Dosing
How should UDCA be dosed in everyday practice?
Dosing varies by indication and body weight and should usually be calculated as mg per kg per day for best outcomes.
For gallstone dissolution typical dosing is 8–10 mg/kg/day, commonly achieved with 300 mg twice daily or with 250–500 mg tablets as needed to approximate weight‑based dosing.
For PBC the standard therapeutic dose is higher: 13–15 mg/kg/day divided into two or three doses.
Condition-Specific Dosing (PBS Recommendations)
How do PBS‑aligned prescribers manage dosing and monitoring?
When prescribing for PBC, clinicians document baseline LFTs and aim for weight‑based dosing with repeat monitoring at 3–6 months to assess biochemical response.
Gallstone therapy is usually continued 6–24 months with imaging confirmation of dissolution before stopping.
Elderly patients generally require clinical monitoring rather than routine dose reductions unless comorbidity suggests otherwise.
Contraindications (Australian Guidelines)
Who must not take UDCA?
UDCA is contraindicated in complete biliary or gallbladder obstruction and in anyone with known hypersensitivity to the drug or excipients.
Avoid use in active biliary infection and exercise caution or avoid in decompensated cirrhosis.
UDCA is ineffective for chronic calcified or pigment stones and should not be used as a weight‑loss medicine.
Adverse Effects (Post-Market Pharmacovigilance)
What side effects should patients expect and how common are they?
Common adverse effects are mild gastrointestinal symptoms: diarrhoea, nausea and mild abdominal pain; rash is occasionally reported.
Moderate effects include back or musculoskeletal pain and headache in a minority of patients.
Serious allergic reactions are very rare, but pharmacovigilance data flagged rare hepatotoxicity when UDCA is combined with other hepatotoxic medicines.
Monitoring recommendations include baseline LFTs, repeat testing at around 3 months and periodic checks thereafter; stop treatment if cholestasis worsens or obstruction develops.
Food Interactions (Alcohol, Coffee, Diet In Australia)
Does food or drink affect UDCA?
UDCA has limited direct food interactions, but alcohol increases liver stress and should be moderated or avoided in people with liver disease.
Coffee has no known antagonistic effect and may have independent hepatoprotective associations, but it is not a substitute for therapy.
Drug Combinations To Avoid (TGA Safety Alerts)
Which medicines need caution when taken with UDCA?
UDCA is not a major CYP substrate but can have absorption interactions with bile‑dependent compounds.
Bile acid sequestrants such as cholestyramine bind UDCA and reduce absorption; separate dosing by several hours.
TGA safety alerts 2022–25 emphasise caution when combining UDCA with other hepatotoxic drugs and highlight complex interactions with obeticholic acid in PBC management.
Australian Survey Data
How do Australian patients experience UDCA treatment?
Clinic-based and online surveys from 2022–24 report modest symptom relief, especially reduced pruritus in cholestatic patients.
Discontinuation often follows persistent diarrhoea or GI upset without consultation with the prescriber.
Patients who receive clear counselling on duration, need for imaging and LFT monitoring are more likely to adhere with therapy.
Forum And Pharmacy Trends
What do pharmacists see on the shop floor and online forums?
Common patient searches include "Actigall 300mg" and comparisons of brands and prices.
Urban patients generally have quicker access to hepatology and PBS advice, whereas rural patients rely heavily on pharmacists for initiation and monitoring guidance.
Pharmacists at major chains handle questions about generics, importation and telehealth e‑scripts frequently.
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where can Australians buy UDCA?
Distribution occurs through community pharmacies, including major chains such as Chemist Warehouse, Priceline and TerryWhite, and via hospital pharmacies.
Local listings often favour generics supplied by manufacturers such as Sun Pharma or Sandoz rather than international Actigall stock.
Online Pharmacy Growth And Telehealth E-Scripts
How has access changed recently?
Between 2022 and 2025 online pharmacy services and telehealth e‑scripts expanded access, particularly for rural patients.
In our online pharmacy, actigall is available without a prescription, with discreet delivery to Australia in 5-14 days.
However, importation and unsupervised sourcing have regulatory limits; patients should follow prescriber guidance and pharmacist counselling.
PBS Vs Private Cost Comparisons
How much will UDCA cost me in Australia?
PBS subsidy tends to apply for PBC and specific documented indications, reducing patient cost for eligible prescriptions.
Gallstone dissolution therapy is frequently privately paid, making generics and supplier choice important for price-sensitive patients.
Pharmacists commonly substitute a generic brand to reduce out‑of‑pocket cost when clinically appropriate.
Comparison Table Of PBS And Non-PBS Options
What are the main alternatives to UDCA if PBS criteria are not met?
Pharmacologic alternatives include chenodiol (chenodal) and obeticholic acid for PBC when UDCA response is inadequate.
Non‑pharmacologic options include laparoscopic cholecystectomy, which is definitive for symptomatic stones.
Pros And Cons Checklist
- UDCA: Non‑invasive, generally well tolerated, effective for non‑calcified cholesterol stones and cholestatic diseases.
- Chenodiol: Effective for some stones but carries higher hepatotoxic risk.
- Obeticholic Acid: Newer PBC agent used when UDCA response is inadequate; different safety and cost profile.
- Surgery: Definitive treatment for symptomatic stones but involves operative risks and higher upfront cost.
TGA Approval Framework
How does the TGA regulate UDCA in Australia?
The Therapeutic Goods Administration assesses safety, efficacy and manufacturing quality for registration of ursodeoxycholic acid products.
Sponsors must provide data consistent with international standards and maintain ARTG registration and pharmacovigilance reporting.
Importation of non‑registered international brands may occur under Authorised Prescriber or Special Access Scheme pathways where clinically justified.
PBS Subsidy Process
How does a medicine get on the PBS?
PBS listing requires demonstration of clinical and cost‑effectiveness for specific indications through Health Technology Assessment.
PBC has stronger precedent for subsidy than gallstone dissolution, meaning many gallstone scripts remain private.
Consolidated FAQ
Is Actigall/UDCA available on the PBS for my condition?
PBS coverage depends on your diagnosis; PBC has clearer subsidy pathways while gallstone dissolution is often paid privately.
How long will I need to take UDCA for gallstones?
Typical duration is 6–24 months with imaging to confirm dissolution and periodic LFT monitoring.
Can I take UDCA with other liver medicines?
Often yes, but coordinate with your hepatologist; avoid combining with known hepatotoxins without monitoring and separate UDCA from bile acid sequestrants.
What if I live rurally — can I get it via telehealth?
Yes. Telehealth e‑scripts and community pharmacies supply UDCA, and pharmacists can liaise with specialists for monitoring and follow-up.
Are there safety concerns in pregnancy?
Data are limited for pregnancy and breastfeeding; use only if benefits outweigh risks and after specialist consultation.
Visual Guide
What visuals help patients decide?
Create three infographic panels: PBS pricing flowchart (PBC vs gallstones), pharmacy distribution map (urban vs rural access and telehealth e‑script pathways), and a treatment timeline showing dosing ranges and monitoring checkpoints.
Include storage info (store <25°C) and a common side‑effects frequency bar to set expectations.
Household Storage Under Australian Climate
How should patients store UDCA at home?
Store tablets and capsules below 25°C, protected from moisture and heat, and do not freeze.
Recommend a cool dry place away from bathroom humidity and direct sunlight and avoid leaving medicines in cars during summer.
Cold-Chain Logistics For Pharmacies
Do pharmacies need refrigeration?
UDCA does not require cold‑chain storage but pharmacies should keep stock in temperature‑controlled storage and rotate stock during heatwaves, especially in northern Australia.
Online distributors should package items to prevent moisture ingress and follow TGA good distribution practices.
Pharmacist Counselling Style In Australia
How should pharmacists talk to patients about UDCA?
Use a clear, empathetic approach: explain the indication, weight‑based dosing, expected duration and the monitoring plan (baseline and follow‑up LFTs, imaging where required).
Advise on common side effects, drug spacing with cholestyramine and what to do if diarrhoea or worsening symptoms occur.
Document counselling and facilitate telehealth referrals where specialist input is needed, particularly for pregnancy, paediatric or complex cases.
National Health Authority Recommendations
What do national bodies recommend?
National guidance emphasises imaging confirmation before long‑term use for gallstones, avoidance in complete biliary obstruction and careful use in advanced liver disease.
Liaise with hepatology for atypical presentations or poor biochemical response.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
Storage & Transport Practicalities
How should pharmacies and patients prepare for Australian weather?
Store UDCA below 25°C in its original container and protect from moisture and heat.
Do not freeze the product.
Pharmacies in hot regions should monitor storage temperatures and plan bulk ordering to avoid stockouts during extreme weather.
Guidelines For Proper Use
What are the key counselling points pharmacists should cover?
Confirm the indication and dosing, explain expected duration, and set a monitoring schedule with baseline and follow‑up LFTs and imaging where appropriate.
Advise on drug interactions, especially spacing from bile acid sequestrants and caution with hepatotoxic medicines.
Provide clear escalation criteria: worsening abdominal pain, jaundice, severe diarrhoea or new allergic signs should prompt immediate review.
Final Notes For Clinicians And Patients
What are the main clinical takeaways from recent evidence and regulatory data?
UDCA (actigall and generics) remains a useful, evidence‑based option for non‑calcified cholesterol gallstones, preventing stones after rapid weight loss, and as first‑line therapy in PBC.
Standard dosing is weight-based: 8–10 mg/kg/day for stones and 13–15 mg/kg/day for PBC, with therapy durations of months for stones and long‑term for PBC.
Monitoring with baseline and periodic LFTs and imaging where indicated is essential, and clinicians should avoid use in complete biliary obstruction and decompensated cirrhosis.
Patients who get clear counselling from pharmacists about dosing, duration and follow‑up are far more likely to adhere and achieve the intended outcomes.