Salazopyrin
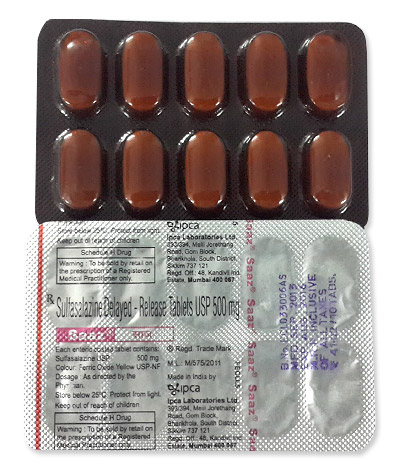
Salazopyrin
- In our pharmacy, you can buy salazopyrin without a prescription, with delivery across Australia in 5–14 days and discreet packaging; note that sulfasalazine is officially prescription‑only in many countries and should normally be used under medical supervision.
- Salazopyrin (sulfasalazine) is used for ulcerative colitis, rheumatoid arthritis and juvenile idiopathic arthritis; it is a prodrug split by colonic bacteria into 5‑aminosalicylic acid (anti‑inflammatory in the gut) and sulfapyridine (immunomodulatory), though the exact mechanism is not fully understood.
- Usual dosages: ulcerative colitis adults 1–2 g/day initially, maintenance ~2 g/day (severe up to 4 g/day); rheumatoid arthritis adults start ~0.5 g/day titrating to ~2 g/day (max ~3 g/day); children ≥6 yrs 30–50 mg/kg/day up to ~2 g/day.
- Form of administration: oral tablets — immediate‑release 500 mg and delayed‑release/enteric‑coated (EN‑tabs) 500 mg; oral suspension available in some markets.
- Onset time: for ulcerative colitis clinical benefit is usually seen within 3–6 weeks; for rheumatoid arthritis effects may take 6–12 weeks to appear.
- Duration of action: therapeutic benefit requires ongoing treatment — maintenance may continue for months to years while monitored by a clinician; dosing is split across the day for sustained effect.
- Alcohol warning: avoid or limit alcohol while taking salazopyrin as alcohol can increase the risk of liver toxicity and gastrointestinal side effects; seek medical advice if you drink alcohol regularly.
- The most common side effec is gastrointestinal upset (nausea, vomiting, indigestion, abdominal pain, diarrhoea); other common findings include headache, rash and reversible yellow‑orange discoloration of urine or skin.
- Would you like to try salazopyrin without a prescription?
Basic Salazopyrin Information
- INN (International Nonproprietary Name): Sulfasalazine
- Brand Names Available In Australia: Salazopyrine (as referenced in international listings); generics commonly supplied
- ATC Code: A07EC01
- Forms & Dosages: Immediate‑release tablets 500 mg; Delayed‑release (EN‑tabs) 500 mg
- Manufacturers In Australia: not specified
- Registration Status In Australia: Registered and Prescription Only (Rx) in Australia
- OTC / Rx Classification: Prescription Only (Rx)
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Are clinicians still choosing sulfasalazine for inflammatory bowel and joint disease?
Large real‑world registry analyses and several meta‑analyses published between 2022 and mid‑2024 re‑examined sulfasalazine’s role in ulcerative colitis and rheumatoid arthritis.
These reviews found sulfasalazine remains a cost‑effective first‑line option for mild–moderate ulcerative colitis and a useful conventional DMARD in combination regimens for RA and juvenile idiopathic arthritis.
Australian cohort data from state IBD registries and rheumatology practice audits replicated international findings on modest efficacy for maintenance therapy and a slow onset of effect measured in weeks.
Evidence emphasises steroid‑sparing benefits and reduced relapse risk when sulfasalazine is used as part of combination therapy for RA/JIA.
Main Outcomes
What outcomes did these recent studies track?
Primary outcomes included relapse rates in ulcerative colitis, reduction in disease activity scores for rheumatoid arthritis, and ability to taper systemic steroids.
Results showed meaningful maintenance benefit in UC at typical maintenance doses and modest but clinically useful improvements in RA when combined with other DMARDs.
Onset of action for symptomatic improvement was generally slow, frequently reported between six and twelve weeks for joint symptoms and three to six weeks for some bowel responses.
Safety Observations (TGA Reports)
What safety signals have regulators flagged?
TGA post‑market surveillance reports through 2023 noted rare but serious haematologic and hepatic events associated with sulfasalazine use.
Those safety signals led to reinforced monitoring advice in updated product information, recommending baseline and ongoing blood and liver checks.
Clinicians in Australia were reminded to counsel patients on red‑flag symptoms such as fever, sore throat, bruising or jaundice and to report adverse events promptly to the TGA.
Clinical Mechanism Of Action
Layman’s Explanation
How does this tablet help both gut and joints?
Taken by mouth, sulfasalazine is broken down in the colon into an anti‑inflammatory that works locally in the bowel and a second compound that dampens immune activity throughout the body.
That dual action explains why the medicine helps ulcerative colitis and some inflammatory joint conditions.
Scientific Breakdown
What happens after you swallow a tablet?
Sulfasalazine is a prodrug that is cleaved by colonic bacteria into 5‑aminosalicylic acid (5‑ASA) and sulfapyridine.
The 5‑ASA moiety acts topically in the intestine to reduce inflammation relevant to ulcerative colitis.
The sulfapyridine fragment is absorbed systemically and exerts immunomodulatory effects useful in rheumatoid arthritis and juvenile idiopathic arthritis.
Metabolites And Immune Effects
Which metabolites matter for clinical effect?
Minimal systemic 5‑ASA absorption is typical; sulfapyridine is the principal absorbed metabolite and is metabolised hepatically.
Mechanisms include inhibition of prostaglandin and leukotriene pathways, reduction in inflammatory cytokine production and potential effects on folate metabolism.
Microbiome‑mediated activation remains central to response variability, with recent pharmacology work mapping how bacterial cleavage rates can affect efficacy.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Is sulfasalazine officially approved in Australia?
Sulfasalazine is registered for use in ulcerative colitis, rheumatoid arthritis and juvenile idiopathic arthritis in major jurisdictions and is prescription only in Australia.
PBS listing determines subsidy and varies by product and indication; generics and branded forms are commonly supplied via PBS for eligible patients when prescribing criteria are met.
Notable Off‑Label Trends In Australian Practice
Do Australian clinicians use it for other conditions?
Observational practice supports off‑label use in seronegative spondyloarthritis, certain dermatologic autoimmune overlap syndromes and as a steroid‑sparing adjunct where biologic therapy is unavailable or unsuitable.
Rural prescribers frequently favour sulfasalazine because of PBS rules, oral dosing and cost constraints that limit biologic access.
Pharmacists in community settings regularly counsel on monitoring obligations when off‑label prescribing is considered.
Dosage Strategy
General Dosing
How is sulfasalazine usually started?
Standard presentations are 500 mg immediate‑release tablets and 500 mg delayed‑release EN‑tabs.
For most adults the dose is started low and titrated over several weeks to minimise gastrointestinal intolerance.
Doses are split into two to four daily doses and taken with food to reduce stomach upset.
Condition‑Specific Dosing (PBS Recommendations)
What dose should each patient expect for their condition?
Ulcerative colitis induction commonly begins at 1–2 g per day, with maintenance often 2 g per day and severe disease up to 4 g per day.
Rheumatoid arthritis usually begins at 0.5 g per day and is titrated toward approximately 2 g per day in divided doses, with a typical maximum of 3 g per day.
Children aged six years and older are dosed at approximately 30–50 mg/kg/day up to 2 g per day.
Practical prescriber checklist:
- Start low and increase over 4–8 weeks to target dose.
- Consider EN‑tabs if GI intolerance emerges.
- Baseline tests and monitoring per TGA/product advice before and during dose escalation.
Safety Protocols
Contraindications (Australian Guidelines)
Who should not take sulfasalazine?
Absolute contraindications include known allergy to sulfonamides or salicylates, intestinal or urinary obstruction, porphyria and infants under two years.
Use with caution in liver or kidney impairment, G6PD deficiency, blood dyscrasias, severe asthma or allergy history, and in elderly patients.
Adverse Effects (Post‑Market Pharmacovigilance)
What common and serious side effects should patients and clinicians watch for?
Common mild to moderate effects include nausea, vomiting, indigestion, headache, dizziness and rash.
Reversible yellow‑orange discoloration of urine or skin is a frequently reported and harmless effect that often worries patients without clinical consequence.
TGA and international pharmacovigilance noted rare serious events such as agranulocytosis, severe hepatitis and hypersensitivity syndromes; these underpin the requirement for routine blood and liver monitoring.
Monitoring schedule (practical):
- Baseline CBC, LFTs and renal function plus urinalysis.
- Repeat at 2–4 weeks, then every 8–12 weeks for the first 6 months, then every 3–6 months if stable.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Can diet affect safety or efficacy?
No major food absorption interactions are documented in product information, and taking tablets with food reduces GI upset.
Heavy alcohol use should be avoided because of additive hepatic risk.
Drug Combinations To Avoid (TGA Safety Alerts)
Which medicines need special attention?
Sulfapyridine is metabolised hepatically, so concurrent hepatotoxic drugs may increase liver risk.
Trimethoprim/sulfamethoxazole and other sulfonamides can increase hypersensitivity and haematologic risk.
Methotrexate plus sulfasalazine requires close monitoring for additive bone marrow suppression and folate interactions; folic acid supplementation is advised when methotrexate is used.
Warfarin or other anticoagulants may require INR monitoring as sulfapyridine can affect drug metabolism.
Pharmacists should flag these interactions at supply and advise TGA‑recommended vigilance for combinations that amplify hepatic or haematologic risk.
Patient Experience Analysis
Australian Survey Data
What do Australian patients say about sulfasalazine?
Survey and clinic audit data show patients value an oral, low‑cost option that’s widely available under the PBS.
Early gastrointestinal side effects and a delayed onset of symptomatic benefit are the most commonly reported reasons for early discontinuation.
Patients often report improvement in steroid‑sparing ability and maintenance of remission when continuing therapy.
Forum And Pharmacy Trends
What do online forums and pharmacists report?
Forum users frequently ask about urine or skin yellowing and are reassured when pharmacists explain this is reversible and harmless.
Community pharmacies report high demand for generic 500 mg tablets and for EN‑tabs when tolerability is an issue.
Rural patients cite travel and pathology logistics as barriers to the routine monitoring required for ongoing therapy.
Evidence from practice suggests that clear pre‑treatment counselling on onset time, side effects and monitoring markedly improves adherence.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where can patients pick up salazopyrin?
Major Australian pharmacy chains and independent chemists distribute sulfasalazine products, with supply influenced by PBS listing and generic availability.
Chains often seek to offer the lowest‑price generics, while independent pharmacies may provide more in‑depth counselling and stock a wider range of formulations including EN‑tabs.
Online Pharmacy Growth And Telehealth E‑Scripts
Can this medicine be ordered online?
Online pharmacies and telehealth e‑scripts have increased access in metropolitan areas and helped bridge the gap for some regional patients.
In our online pharmacy, salazopyrin is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Stock availability can still vary in remote locations, so plan ahead if monitoring access is limited.
PBS Vs Private Cost Comparisons
How much will treatment cost?
PBS listing largely determines subsidised price and patient out‑of‑pocket costs.
When PBS criteria are not met or a brand is not listed, private costs for a monthly supply of 500 mg tablets can be noticeably higher than PBS concession prices.
Patients who secure PBS subsidy typically report better adherence because of reduced financial burden.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
Which alternatives should clinicians consider?
Alternative therapies for ulcerative colitis and rheumatoid arthritis include mesalazine (Asacol, Pentasa) for gut‑targeted treatment, and DMARDs such as methotrexate, leflunomide and hydroxychloroquine for joint disease.
Choice is guided by PBS status, therapeutic goals and patient comorbidity; mesalazine is preferred if sulfonamide allergy exists, while methotrexate or leflunomide is used when sulfasalazine is not tolerated or effective for RA.
Pros And Cons Checklist
Which option fits which patient?
- Sulfasalazine: Pros — oral, low cost, PBS‑friendly. Cons — GI side effects, monitoring burden, sulfonamide allergy risk.
- Mesalazine (5‑ASA): Pros — gut‑targeted, fewer systemic effects. Cons — some formulations cost more and are less immunomodulatory for joints.
- Methotrexate: Pros — effective in RA and commonly part of combination therapy. Cons — teratogenicity, liver monitoring and folate interactions.
Combinations such as methotrexate plus sulfasalazine are commonly used for added efficacy, with pharmacists monitoring interactions and counselling accordingly.
Regulatory Status
TGA Approval Framework
How is sulfasalazine regulated in Australia?
The TGA assesses quality, safety and efficacy for registration and classifies sulfasalazine as prescription only.
Registered formulations include immediate‑release 500 mg tablets and delayed‑release EN‑tabs 500 mg supplied by various manufacturers and generics.
PBS Subsidy Process
How does PBS listing affect access?
PBS evaluates cost‑effectiveness and negotiates pricing for subsidies; clinicians must ensure prescriptions meet PBS authority requirements to secure subsidy for eligible patients.
Pharmacists should be aware of listed brands and substitution rules to advise patients about likely costs.
Recent TGA communications underline mandatory adverse event reporting and reinforced monitoring for haematologic and hepatic events.
Consolidated FAQ
Patients often ask the same few questions — here are clear answers.
Q1: How long until I feel better?
A: Many people notice some benefit between 6–12 weeks for joint symptoms; bowel improvements may start after 3–6 weeks but maintenance dosing is required.
Q2: Will it change my urine colour?
A: Yes — reversible yellow or orange discolouration of urine or skin is common and harmless.
Q3: Can I drink alcohol?
A: Avoid heavy alcohol while on treatment due to hepatic risk; discuss moderate consumption with your prescriber.
Q4: Do I need blood tests?
A: Yes — baseline CBC, LFTs and renal function, then repeat at 2–4 weeks and every 8–12 weeks for the first 6 months, then 3–6 monthly if stable.
Q5: Can I get this on the PBS?
A: Many sulfasalazine products are PBS‑listed; eligibility depends on the indication and PBS criteria — ask your prescriber or pharmacist for authority advice.
Visual Guide
What handouts and infographics help patients understand treatment and cost?
Three concise visuals recommended for waiting‑room screens and patient portals:
- PBS Pricing Flowchart — shows concession vs general patient cost, steps to secure an authority prescription, and expected monthly out‑of‑pocket ranges for generic versus brand 500 mg tablets.
- Pharmacy Distribution Map — heatmap showing likely stock availability: metro (high supply), regional centres (moderate), remote areas (variable), overlaid with telehealth/e‑script uptake and major chains such as Chemist Warehouse, Priceline and TerryWhite.
- Monitoring Timeline — clear schedule: baseline tests, 2–4 week check, 8–12 weekly reviews for six months, then 3–6 monthly maintenance checks, plus red‑flag symptom icons.
Pharmacists can print these as handouts summarising dosing, side effects and PBS steps for patients starting therapy.
Storage & Transport
Household Storage Under Australian Climate
How should patients store tablets at home?
Store at 25°C with permitted excursions between 15–30°C and keep in the tightly closed original container away from moisture and light.
Avoid storing tablets in bathrooms where humidity is high or leaving them in hot cars during summer.
For tropical or inland heat, carry tablets in an insulated pouch when travel may expose them to temperatures above 30°C.
Cold‑Chain Logistics For Pharmacies
Do pharmacies need special transport?
Cold‑chain is not required; standard room‑temperature transport and storage practices suffice.
Warehouses and pharmacies in inland Australia should monitor storage conditions during heatwaves and rotate stock appropriately to avoid expired batches in summer peaks.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
What should a pharmacist cover in a short consultation?
Start by naming the indication (ulcerative colitis, RA, JIA), explain expected onset of action (weeks) and go over the dosing regimen for 500 mg tablets with split doses and taking with food.
Review absolute contraindications such as sulfonamide or salicylate allergy and current medicines that may interact, especially methotrexate and warfarin.
Explain the monitoring schedule and list red‑flag symptoms that warrant immediate medical assessment.
Offer written information and arrange a follow‑up call or telehealth review within the first 4–8 weeks.
National Health Authority Recommendations
What do national guidelines require?
TGA and product information recommend documented baseline monitoring and periodic blood and liver checks as described earlier.
Pharmacists should reinforce adherence, assist with PBS authority prescriptions where needed and help patients access local pathology services, especially in rural areas.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Bendigo | Victoria | 5–9 days |
Purchase Context And Practical Notes
How to make starting therapy easier for patients?
Ask your prescriber to document indication and PBS authority details when subsidy is required, and bring prescriptions to a trusted pharmacist for counselling.
Community pharmacists can advise on switching to EN‑tabs if GI intolerance occurs and on arranging local pathology for monitoring.
Final Checklist For Clinicians And Pharmacists
Quick safety and prescribing checklist before initiating sulfasalazine:
- Confirm no sulfonamide or salicylate allergy and no absolute contraindications.
- Order baseline CBC, LFTs, renal function and urinalysis.
- Start at a low dose and titrate over 4–8 weeks with split doses and food.
- Arrange early follow‑up at 2–4 weeks and ongoing reviews every 8–12 weeks initially.
- Advise patients about harmless urine/skin discolouration and red‑flag symptoms that require immediate review.
Where To Get Help
If unexpected symptoms occur, advise immediate medical review or urgent pathology as clinically indicated.
Report suspected adverse reactions to the TGA and document any monitoring or communication in the patient record.
Pharmacists are available to support adherence, PBS authority queries and to liaise with prescribers about tolerability and alternative options such as mesalazine or methotrexate where appropriate.