
Monodur
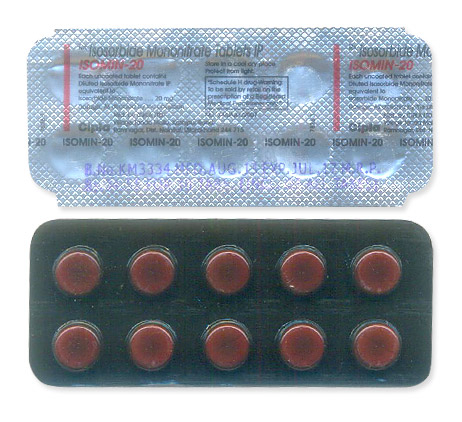
Monodur
- In our pharmacy you can buy monodur without a prescription, with discreet delivery across Australia; note that monodur (isosorbide mononitrate) is prescription‑only in many countries and is usually intended to be used under medical supervision.
- Monodur is used to prevent angina pectoris; it is an organic nitrate that releases nitric oxide, causing venous and coronary vasodilation, reducing cardiac preload and myocardial oxygen demand.
- Usual dosage for angina prevention is 20 mg once or twice daily for immediate‑release formulations; maintenance dosing commonly ranges 20–40 mg twice daily (IR) or 40–60 mg once daily for extended‑release tablets—start at the lowest effective dose and allow a nitrate‑free interval (usually 10–12 hours) to avoid tolerance.
- Form of administration: oral tablets — immediate‑release (commonly 10 mg, 20 mg) and extended‑release/retard tablets (commonly 40 mg, 50 mg, 60 mg), supplied in blisters or bottles.
- Onset time: immediate‑release tablets usually begin to work within about 30–60 minutes; extended‑release formulations may take around 1–2 hours to reach full effect.
- Duration of action: immediate‑release effects typically last about 4–6 hours; extended‑release preparations provide longer coverage, often up to 12–24 hours; a daily nitrate‑free period of at least 10–12 hours is recommended to prevent tolerance.
- Alcohol warning: avoid or limit alcohol while taking monodur — alcohol can exaggerate blood‑pressure lowering, causing marked dizziness, fainting or severe hypotension.
- The most common side effec is headache (so‑called “nitrate headache”); other common effects include dizziness, lightheadedness and flushing; hypotension and nausea are less common.
- Would you like to try monodur without a prescription?

Basic Monodur Information
- INN (International Nonproprietary Name): Monoket is the brand name; its INN is isosorbide mononitrate.
- Brand Names Available In Australia: not specified.
- ATC Code: C01DA14.
- Forms & Dosages: Oral tablets immediate‑release 10 mg and 20 mg; extended‑release tablets/capsules 40 mg, 50 mg and 60 mg; common packs in blisters or bottles (20, 28, 30, 60, 100 tablets).
- Manufacturers In Australia: not specified; global suppliers include Bayer AG, Atno Pharmaceuticals LLC, Krewel‑Meuselbach GmbH and Zentiva.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription Only (Rx) in all major markets.
Key Findings From Recent Trials
Patients and prescribers often ask whether there are any new big trials for monodur and similar drugs between 2022 and 2025.
There have been few novel large randomised controlled trials solely on isosorbide mononitrate in that period.
Most recent work is at class level, with meta‑analyses and observational registries confirming the role of long‑acting nitrates for chronic angina prophylaxis.
Australian cardiology audits show ongoing community use of isosorbide mononitrate as an add‑on when beta‑blockers or calcium‑channel blockers are insufficient.
International cohort studies focused on long‑acting nitrates in multimodal regimens and on health‑service outcomes such as adherence and keeping a nitrate‑free interval.
Main outcomes consistently show symptom reduction with extended‑release formulations at typical doses such as 40–60 mg once daily when a nitrate‑free interval is observed.
Exercise tolerance shows modest improvements versus placebo, while there is limited evidence of mortality benefit.
Post‑market safety reports continue to show class‑typical adverse events such as headache, dizziness and episodic hypotension.
The TGA highlights counselling on falls risk for older patients and routine checks for concurrent PDE‑5 inhibitor use.
Common names discussed in these studies include Monoket, Monodur, Duride and generic APO‑ISMN preparations.
Clinical Mechanism Of Action
People commonly want a plain answer: how does monodur prevent chest pain?
Isosorbide mononitrate acts as a nitrate vasodilator by releasing nitric oxide metabolites in blood vessels.
Those metabolites relax vascular smooth muscle, which reduces venous return (preload) and lowers myocardial oxygen demand.
The net effect is that the heart needs less oxygen during exertion, which reduces angina frequency.
Pharmacologically, isosorbide mononitrate is absorbed after oral dosing in either immediate‑release or extended‑release forms.
Because it is a mononitrate it largely bypasses first‑pass hepatic conversion and achieves predictable plasma levels compared with isosorbide dinitrate.
Extended‑release tablets such as Monodur or some Monoket retard formulations provide steady vasodilation and support once‑daily dosing.
The cellular cascade is: NO activates guanylate cyclase, which raises cGMP and causes smooth muscle relaxation.
Immediate‑release tablets give a faster onset useful for titration, while ER forms give stable control but require a nitrate‑free interval to prevent tolerance.
Compared with isosorbide dinitrate and nitroglycerin, isosorbide mononitrate has more stable pharmacokinetics and does not require hepatic activation.
Cellular Cascade
NO stimulates guanylate cyclase in vascular smooth muscle cells.
This increases cyclic GMP concentrations and leads to relaxation of smooth muscle.
The clinical implications are straightforward: rapid onset with IR, sustained effect with ER, and the need for a 10–12 hour nitrate‑free interval daily to avoid tolerance.
Drug Class Features
Isosorbide mononitrate provides steadier plasma levels than some other nitrates and is available as ER and IR formulations such as Monoket, Monodur and APO‑ISMN.
Scope Of Approved & Off‑Label Use
Patients ask whether monodur is approved in Australia and what else it is used for.
Internationally, isosorbide mononitrate is approved for stable angina prophylaxis by agencies such as the EMA and FDA.
In Australia, prescribers refer to TGA ARTG listings and PBS schedules for subsidy and availability, and these can vary by brand and formulation.
Clinicians should confirm current ARTG entries and any PBS Authority rules that affect chronic angina management.
Notable off‑label uses in specialist settings include preload reduction in selected heart‑failure patients and palliative vasodilation for refractory ischaemic chest pain under specialist supervision.
Use in paediatrics is not recommended due to a lack of safety and efficacy data.
Globally, Monoket and similar products remain prescription‑only, and the same applies within Australia.
Off‑label prescribing should be documented and, where possible, carried out with specialist input and monitoring for hypotension and tolerance.
Brand names encountered at pharmacies include Monoket, Monodur, Duride and generic APO‑ISMN options.
Dosage Strategy
One common worry is getting the dose and timing right to balance benefit and side effects.
Typical regimens from product information include immediate‑release 10–20 mg once or twice daily.
Extended‑release formulations are commonly 40–60 mg once daily and often improve adherence by reducing dosing frequency.
For angina prophylaxis ER dosing tends to give steadier control and fewer large peaks and troughs compared with IR dosing.
PBS and standard therapeutic guidance recommend starting low and titrating as needed.
Example: IR may start at 20 mg once or twice daily and be increased within a range up to 40 mg twice daily if required.
ER regimens commonly use 40–60 mg once daily with a planned nitrate‑free interval of at least 10–12 hours, typically overnight.
Elderly patients should have dosing started low and have blood pressure monitored for orthostatic symptoms.
Renal or hepatic impairment calls for caution and closer monitoring rather than prespecified dose reductions.
Missed doses should be taken if less than four hours late; otherwise skip and never double up.
Special Populations
Children: not recommended due to insufficient data.
Elderly: initiate at the lowest effective dose and monitor blood pressure and falls risk.
Renal/hepatic impairment: increase clinical monitoring rather than automatic dose cuts.
Safety Protocols
People often ask what absolutely rules out taking monodur.
Absolute contraindications include hypersensitivity to nitrates, severe hypotension or shock, acute circulatory failure and concomitant use with PDE‑5 inhibitors such as sildenafil, tadalafil or vardenafil.
Other contraindications are acute myocardial infarction with low filling pressures, constrictive pericarditis, cardiac tamponade and known severe anaemia.
Precautions include glaucoma, hypertrophic obstructive cardiomyopathy and marked renal or hepatic impairment.
Very common adverse effects are headache, often called a “nitrate headache”.
Common effects include dizziness, lightheadedness and flushing; less common effects include nausea and symptomatic hypotension.
Rare events reported are tachycardia, syncope and allergic skin reactions.
TGA and post‑market surveillance flag falls and orthostatic hypotension in elderly community users, so counselling is essential.
Baseline blood pressure checks and periodic monitoring after dose changes are recommended, and serious events should be reported to the TGA Adverse Event Program.
Monitoring
Measure baseline BP and repeat after initiation or dose changes.
Counsel patients to rise slowly from sitting or lying positions and to avoid driving if dizzy.
Interaction Mapping
Patients frequently ask which foods or medications to avoid while taking monodur.
Alcohol increases vasodilation and can raise the risk of symptomatic hypotension, so reduce intake when starting or increasing the dose.
There is no clinically significant interaction with coffee, but caffeine can cause tachycardia which may worsen palpitations or chest discomfort.
High‑salt diets affect overall blood pressure management and should be addressed as part of cardiac risk reduction.
The most critical drug interaction is with PDE‑5 inhibitors; co‑administration is absolutely contraindicated due to the risk of severe hypotension.
Exercise caution when combining isosorbide mononitrate with other antihypertensives such as beta‑blockers, ACE inhibitors or diuretics because of additive blood‑pressure lowering.
Combining multiple nitrates is generally unnecessary and can be additive in effect.
Pharmacists should routinely ask about erectile‑dysfunction medications, recreational drugs and use dispensing software alerts to flag contraindicated combinations.
Report clinically significant suspected interactions to the TGA to support pharmacovigilance.
Pharmacy Workflow
- Ask: current medicines including ED drugs and recreational nitrates.
- Flag: use software alerts and counsel on alcohol and orthostatic risk.
Patient Experience Analysis
Patients often say they prefer once‑daily tablets to reduce the chance of missed doses.
Australian surveys and pharmacy audits show that extended‑release options such as Monodur are valued for convenience and steady symptom control.
Common initial complaints include headache and lightheadedness during the first days of therapy.
Adherence drops when the nitrate‑free interval is not clearly explained, because tolerance reduces perceived benefit.
Rural patients report more difficulty accessing specialist review for dose titration and rely on community pharmacists for practical advice.
Online forums and pharmacy counselling refer interchangeably to brand names such as Monoket, Monodur and Duride, and many patients ask about lower‑cost APO‑ISMN generics.
Chain pharmacies including Chemist Warehouse, Priceline and TerryWhite commonly handle price queries and provide counselling on dosing schedules and interactions with erectile‑dysfunction medications.
Cost sensitivity is real; some patients split doses or stop therapy when out‑of‑pocket costs are high, which risks uncontrolled angina.
Pharmacists should proactively explain PBS subsidy options and generic alternatives to support adherence.
Distribution & Pricing Landscape
Availability and price vary across national pharmacy chains and between brand and generic options.
Major chains such as Chemist Warehouse, Priceline and TerryWhite stock both brand ER/IR formulations and generics, and negotiated supplier deals influence consumer prices.
Monoket and other brands come in blister packs of 20, 30 or 60 tablets, which affects per‑tablet cost.
Online pharmacies and telehealth e‑prescriptions have grown and increase convenience for metropolitan and regional patients.
Online suppliers must comply with ARTG and TGA import rules and pharmacists will validate e‑scripts and provide counselling by phone or video.
PBS listing determines subsidy levels; where PBS‑listed, co‑payments are lower and adherence is better.
Private purchase costs vary by brand and pack size and often drive uptake of APO‑ISMN generics for those paying out of pocket.
Rural patients may face postage fees or stock delays that increase total cost and complicate continuity of therapy.
In our online pharmacy, monodur is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Alternative Options
Patients and clinicians often want practical comparisons when monodur is unsuitable or unaffordable.
Key therapeutic alternatives include isosorbide dinitrate for shorter‑acting needs, nitroglycerin for acute attacks, nicorandil, ranolazine and conventional agents such as beta‑blockers and calcium‑channel blockers.
Nitroglycerin sublingual is fast acting for acute chest pain but has a short duration and is not for prophylaxis.
Isosorbide dinitrate has different pharmacokinetics and may be useful when IR dosing or intravenous options are indicated.
Ranolazine offers an alternative non‑nitrate mechanism for chronic angina, but cost and side‑effect profiles differ from nitrates.
Pros and cons checklist: ER isosorbide mononitrate offers once‑daily steady control but needs a nitrate‑free interval to avoid tolerance.
IR forms provide flexible dosing but require multiple daily doses and can produce peaks that increase headaches.
Choosing therapy in Australia should factor in PBS subsidy, comorbidity such as hypotension risk, interactions with PDE‑5 inhibitors, and rural access to follow‑up.
Pharmacists should present clinical alternatives and the likely co‑pay implications to help patients decide.
Regulatory Status
The TGA evaluates safety, quality and efficacy data before a product is entered on the ARTG for Australian supply.
Manufacturers supply clinical and manufacturing dossiers to support ARTG listing for isosorbide mononitrate products.
International approvals by EMA and FDA are common for Monoket and related brands, but Australian prescribers must confirm ARTG entries locally.
PBS subsidy requires a submission to PBAC showing cost‑effectiveness versus comparators, so ARTG listing does not guarantee PBS listing.
Decisions on PBS coverage depend on brand, formulation and approved indications and may include Authority prescription rules for chronic angina.
Post‑market safety signals reported to the TGA lead to updates in Product Information and Consumer Medicines Information as needed.
Clinicians and pharmacists are encouraged to report serious adverse events to the TGA to support ongoing pharmacovigilance.
Common regulatory terms encountered by pharmacists include ARTG, PBAC and PBS authority forms.
Consolidated FAQ
Q1: Can I take isosorbide mononitrate with my sildenafil?
A: No. Concomitant use is contraindicated due to the risk of severe hypotension.
Q2: What is a nitrate‑free interval and why does it matter?
A: A daily nitrate‑free period of at least 10–12 hours prevents pharmacologic tolerance and preserves efficacy.
Q3: Is Monoket or Monodur on the PBS?
A: PBS status can vary by brand and formulation; check the current PBS schedule or ask your pharmacist for up‑to‑date information.
Q4: What if I get a severe headache?
A: Nitrate headaches are common initially and often settle over days; persistent severe headache should prompt review with a GP or pharmacist.
Q5: Can rural pharmacies supply refills without GP visits?
A: Some emergency supply provisions exist in Australian jurisdictions, and telehealth e‑scripts are commonly used to bridge rural care, but limits apply.
Visual Guide
Clinics and pharmacies need simple visuals to explain dose timing, costs and safety.
Suggested infographic concepts include a PBS pricing visual showing typical co‑pay versus private pay for 20, 30 and 60 tablet packs and a clear ER versus IR cost comparison.
A dosing timeline graphic should show ER once‑daily dosing with a highlighted nitrate‑free interval of 10–12 hours, and an IR option with spacing that reduces tolerance risk.
A pharmacy distribution map can highlight same‑day availability in metropolitan areas and postal/next‑day options for regional patients.
Implementation notes for Australian clinics: use pictograms for “no erectile‑dysfunction drugs” and “avoid alcohol at initiation”.
Create a one‑page quick sheet for pharmacists at Chemist Warehouse, Priceline and TerryWhite to standardise counselling points.
Design considerations: pick a colour‑blind‑friendly palette, large fonts for older patients and translated Consumer Medicines Information templates for culturally and linguistically diverse communities.
Storage & Transport
Proper storage advice is a frequent pharmacy counselling point, especially in Australia’s varied climate.
Store below 25°C and protect tablets from moisture and direct sunlight.
Avoid storing medicines in bathrooms or cars where heat and humidity are common.
Extended‑release tablets such as Monodur Durules may be sensitive to excessive heat, which can alter release properties.
Isosorbide mononitrate does not require refrigeration, simplifying pharmacy logistics and remote deliveries.
Pharmacies should avoid prolonged exposure to high warehouse temperatures and rotate stock to prevent degradation, particularly for remote supply runs.
For mail order, use insulated packaging or timed deliveries during hot months and advise patients to check expiry dates on receipt.
Document batch numbers when dispensing for pharmacovigilance purposes if required.
Guidelines For Proper Use
Patients want concise counselling that they can follow at home.
Use a practical, patient‑centred approach: explain that monodur is for prevention of angina, not for acute relief.
Emphasise the nitrate‑free interval of at least 10–12 hours and give examples such as taking ER tablets after breakfast with the free interval overnight.
Screen every patient for PDE‑5 inhibitor use and review fall risk and orthostatic precautions before supply.
Discuss PBS and generic options such as APO‑ISMN where cost is a barrier and offer reminder aids like dosette boxes for IR dosing or phone reminders for ER tablets.
Escalation pathways should be clear: persistent headaches, symptomatic hypotension or inadequate control warrant GP or cardiology referral.
Document counselling and any off‑label rationale and encourage reporting of side effects to the TGA.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |